Abstract
Background: Timely and reliable remuneration of frontline health workers is critical for vaccination campaign performance, yet in many low- and middle-income countries cash-based disbursement remains vulnerable to delays, leakage, and inefficiencies. These weaknesses undermine accountability and create recurrent financial burdens, particularly in large-scale operations such as polio immunization campaigns. Objective: This study aimed to evaluate the cost implications of shifting from traditional cash payments to digital disbursement through mobile money during Cote d’Ivoire’s October 2023 national polio immunization campaign. Method: A partial economic evaluation was conducted using a top-down costing approach from the payer’s perspective. Data from all 113 districts and 33 regions were analyzed to compare cash-based and mobile money systems. The analysis focused on direct financial costs, including transaction fees (digital) and transport allowances or ghost worker disbursements (cash). A cost-minimization framework was applied under the assumption of equivalent immunization outputs, and deterministic sensitivity analysis was performed to test robustness. Result: Both systems disbursed the same total amount to vaccinators (397,582,460 FCFA). However, cash payments incurred additional costs of 7,820,967 FCFA in transport and 3,938,930 FCFA in ghost payments, while digital payments generated a 1% transaction fee (3,975,825 FCFA). The digital modality produced a net saving of 7,784,073 FCFA (12,435 USD), or 257 FCFA (0.41 USD) per vaccinator. Sensitivity analysis confirmed the stability of these savings across plausible parameter variations. Conclusion: Digital disbursement via mobile money offers a cost-saving and governance-enhancing alternative to cash payments in vaccination campaigns. Although the absolute savings represent less than 2% of total outlays, the benefits in efficiency, fraud reduction, and transparency are significant for health systems facing budget constraints. Cote d’Ivoire’s experience provides evidence for policymakers to consider institutionalizing digital payments to strengthen financial sustainability and support universal health coverage.
Keywords
Health Care Costs, Digital Financial Services, Health Personnel, Immunization Programs, Sub-Saharan Africa, Cote d’Ivoire
1. Introduction
Financial inefficiencies in health service delivery continue to hinder progress toward Universal Health Coverage (UHC) in low- and middle-income countries (LMICs), particularly across sub-Saharan Africa. Among the most persistent challenges is the delayed or insecure remuneration of frontline health workers during mass immunization campaigns. When payments are late, incomplete, or poorly managed, they undermine staff motivation, fuel absenteeism, and create opportunities for mismanagement and fraud, ultimately weakening campaign effectiveness and population health outcomes
| [1] | Meagher P. Cadre réglementaire pour les services financiers numériques en Côte d’Ivoire 2017. |
[1]
. In response, digital payment systems have emerged as promising solutions, offering the potential to lower transaction costs, increase transparency, and accelerate fund disbursement
| [2] | Agur I, Peria SM, Rochon C. Digital financial services and the pandemic: Opportunities and risks for emerging and developing economies. International Monetary Fund Special Series on COVID-19, Transactions 2020; 1: 2-1. |
| [3] | Labrique A, Vasudevan L, Weiss W, Wilson K. Establishing standards to evaluate the impact of integrating digital health into health systems. Global Health: Science and Practice 2018; 6: S5-17. |
| [4] | Bangura JA. Saving money, saving lives: A case study on the benefits of digitizing payments to ebola response workers in sierra leone. Better Than Cash Alliance, New York 2016. |
[2-4]
.
Digital financial services (DFS) can streamline government-to-person (G2P) transfers and generate efficiency gains within health financing systems
| [5] | Drummond M. Methods for the economic evaluation of health care programmes. Fourth edition. Oxford, United Kingdom; New York, NY, USA: Oxford University Press; 2015. |
[5]
. Evidence from early adopters suggests that DFS enable faster payments, reduce reliance on intermediaries, and limit the prevalence of “ghost workers” or double disbursements
| [6] | Yehualashet YG, Wadda A, Agblewonu KB, Zhema T, Ibrahim AA, Corr A, et al. World Health Organization’s Innovative Direct Disbursement Mechanism for Payment of Grassroots Immunization Personnel and Operations in Nigeria: 2004-2015. The Journal of Infectious Diseases 2016; 213: S108-15. https://doi.org/10.1093/infdis/jiv485. |
[6]
. These attributes align with global strategies promoted by the World Health Organization (WHO), Gavi, and UNICEF, which increasingly advocate for digitized health financing to enhance accountability and effectiveness in immunization campaigns
| [7] | Klapper L, Singer D. The opportunities and challenges of digitizing government-to-person payments. The World Bank Research Observer 2017; 32: 211-26. |
| [8] | World Health Organization. Seventy-first world health assembly, agenda item 12.4, digital health 2021. |
| [9] | WHO. Mobile cash in polio response: three things to know | WHO | Regional Office for Africa. World Health Organization 2025. https://www.afro.who.int/news/mobile-cash-polio-response-three-things-know (accessed April 16, 2025). |
[7-9]
.
In Cote d’Ivoire, the Ministry of Health began piloting mobile money payments for vaccination personnel in 2018, reflecting strong policy interest in digital financing. However, despite subsequent scale-up efforts, there has been little formal evaluation of the economic performance of these systems. This gap is particularly concerning given the recurrent nature of immunization campaigns, their high operational costs, and the scale of the workforce involved—over 30,000 individuals in a single national round. Without costed evidence, decision-makers face uncertainty regarding the financial sustainability of digital payments in routine public health delivery.
More broadly, while the literature on digital health in LMICs has expanded, economic evaluations of digital payment systems for health worker remuneration remain limited. Existing studies tend to emphasize feasibility, acceptability, or technological functionality, with relatively few examining cost-effectiveness
| [10] | Gentili A, Failla G, Melnyk A, Puleo V, Tanna GLD, Ricciardi W, et al. The cost-effectiveness of digital health interventions: a systematic review of the literature. Frontiers in Public Health 2022; 10: 787135. |
[10]
. In the immunization field, most digital innovations have focused on logistics, registries, or patient tracking, while the economic implications of workforce payment systems are comparatively underexplored
| [11] | Hamani A, Hussein Jama I, Roland MAY, Wanjeri L, Oppon-Kusi AA, Karimi D, et al. Mobile Money and the importance of timely, complete payments to frontline health campaign workers in the fight to eradicate polio: pilot experience from a World Health Organization digital payment platform in Africa. BMC Health Services Research 2023; 23: 16. https://doi.org/10.1186/s12913-022-08990-4 |
| [12] | Wang Y, Fekadu G, You JH. Cost-Effectiveness Analyses of Digital Health Technology for Improving the Uptake of Vaccination Programs: Systematic Review. J Med Internet Res 2023; 25: e45493. https://doi.org/10.2196/45493 |
| [13] | Wagaba MT, Musoke D, Opio C, Bagonza A, Aweko J, Nakitende H, et al. Do cash or digital payment modalities affect community health worker performance? - a case study of a remote refugee settlement in Western Uganda. Global Health Action 2024; 17: 2375867. https://doi.org/10.1080/16549716.2024.2375867. |
[11-13]
.
This study addresses that evidence gap by evaluating the cost implications of digital versus cash-based disbursement during Cote d’Ivoire’s October 2023 national polio immunization campaign. Using a cost-minimization framework, it quantifies potential financial savings and identifies operational efficiencies associated with digital payments. The findings provide actionable insights for policymakers seeking to enhance the financial sustainability, accountability, and efficiency of immunization financing strategies in Cote d’Ivoire and similar LMIC contexts.
2. Materials and Methods
2.1. Study Design and Perspective
This study was designed as a partial economic evaluation embedded within a broader mixed-methods assessment of digital payment systems implemented during Cote d’Ivoire’s October 2023 national polio immunization campaign (Round 2). The analysis followed a cost-minimization framework, justified by campaign monitoring data that confirmed equivalent immunization coverage and outputs under both cash-based and digital (mobile money) payment modalities. This assumption allowed the comparison of financial costs without adjusting for differences in effectiveness.
The evaluation was conducted from the payer’s perspective, including only direct costs incurred by the Ministry of Health and its technical and financial partners. The analytic horizon was restricted to a single campaign round (< 12 months); therefore, no discounting was applied, consistent with CHEERS guidelines for short-term interventions.
The intervention under study was a mobile money-based disbursement mechanism for campaign personnel, including vaccinators. This was compared to the pre-existing cash-based payment system by examining aggregate financial costs and disaggregated components: transaction fees (digital), transport allowances (cash), and erroneous or fraudulent disbursements to ghost or duplicate workers (cash).
2.2. Setting and Scope
The economic evaluation was conducted alongside an implementation study covering 14 health districts purposively selected for mixed-methods data collection. At the same time, macro-level costing incorporated administrative and financial records from all 113 health districts and 33 regions, ensuring that the analysis reflected the full national rollout of the intervention.
Over 30,000 vaccinators were mobilized during the campaign, the majority of whom were paid through mobile money platforms. The scope of this study therefore included both district-level implementation costs and aggregated national disbursement data, providing a comprehensive view of financial flows.
2.3. Costing Approach
For this first national evaluation, a top-down costing approach was applied to estimate and compare the financial costs of digital and cash-based systems, following a three-phase framework adapted from Bangura
| [4] | Bangura JA. Saving money, saving lives: A case study on the benefits of digitizing payments to ebola response workers in sierra leone. Better Than Cash Alliance, New York 2016. |
[4]
:
Phase 1 - Cash-based payments (pre-transition): This phase aimed to capture direct and indirect costs associated with manual disbursement, including transport allowances to district health directors (DDS), remuneration of cash-disbursing personnel, and administrative overhead. However, due to data limitations, only transport costs and vaccinator remuneration were available for analysis. Additional costs, such as administrative time for reconciliation in the cash system, or initial coordination and platform maintenance costs for the digital system, were not included. Their inclusion would likely have strengthened the financial advantage of the digital system. Our savings estimate should therefore be considered a lower-bound figure, reflecting direct financial savings for the payer, rather than a full economic cost assessment.
Phase 2 - Digital payment operations (post-transition): This phase was intended to include platform transaction fees (1%), coordination costs, and IT support. In practice, only transaction fees were available and included. Coordination and IT-related expenditures were excluded, producing a conservative estimate of digital payment costs.
Phase 3 - Cost-saving estimation: Financial savings attributable to digital payments were simulated, capturing the elimination of transport allowances, ghost payments, and duplicate disbursements.
All expenditures were recorded in CFA francs (FCFA) and converted into U.S. dollars using the March 2024 exchange rate published by the BCEAO (1 USD = 626 FCFA). No inflation adjustments were applied, given the <12-month horizon.
2.4. Indicator Construction and Calculation Procedures
Economic indicators were derived using a structured Microsoft Excel tool that consolidated financial and administrative data from the Expanded Program on Immunization (EPI). The tool applied standardized formulas consistent with best practices in economic evaluation to estimate costs across modalities.
Key indicators included:
1) Average cost per vaccinator (FCFA): total amount paid to vaccinators ÷ number of vaccinators paid.
2) Ghost/duplicate payments (FCFA): number of ghost/duplicate workers × average payment per vaccinator.
3) Transport allowances (FCFA): average round-trip distances × fuel price (92 FCFA/km), aggregated nationally and by district.
4) Transaction fees (digital, FCFA): 1% of total digital payments.
5) Cost savings per district (FCFA): cash-based cost - digital cost.
This framework permitted calculation of per-vaccinator costs, district-level differentials, and national cost savings.
2.5. Data Sources
Primary data sources were:
1) financial records and payment databases from EPI, which detailed disbursements under both cash and digital modalities.
2) manual verification logs identifying ghost or duplicate workers.
3) qualitative expert interviews with district health directors, EPI managers, which validated assumptions about transport allowances, disbursement practices, and the identification of ghost workers.
2.6. Economic Indicators and Outcomes
The following metrics were produced for comparative evaluation:
1) Transaction fees incurred under the digital system.
2) Average cost per district and per vaccinator.
3) Costs of transport allowances for cash payments.
4) Estimated costs associated with ghost or duplicate workers.
5) Aggregate payment system cost under each modality.
6) Net cost difference nationwide, expressed per district and per vaccinator.
The primary outcome of interest was the net financial savings of digital versus cash-based payments, estimated nationally.
2.7. Sensitivity Analysis
To assess the robustness of the cost-minimization analysis, a deterministic (one-way) sensitivity analysis was planned. Key cost parameters were selected based on their magnitude, variability, and operational relevance to payment systems. For each parameter, a base assumption and plausible ranges were established from program records or international benchmarks.
Payments to ghost/duplicate workers: costs were estimated using the average vaccinator payment, with ghost worker counts varied between 200 and 500 to reflect uncertainty in duplicate detection.
Transaction fees for digital payments: the base assumption was 1% of total disbursed value, consistent with mobile money contract terms. The parameter was varied between 0.5% and 2%, informed by WHO and GSMA benchmarks for transaction fee variability.
Transport allowances under cash payments: allowances were based on typical round-trip distances and fuel prices, with a ±25% variation applied to account for geographic and price fluctuations.
Ghost payment uncertainty: costs associated with unverified or duplicate workers were allowed to vary by ±25% to reflect programmatic uncertainty around manual verification logs.
For each parameter, low and high values were tested while holding other inputs constant. The primary outcome metric was the net cost difference between digital and cash modalities. Outputs included a tornado diagram to visually illustrate the relative influence of each parameter.
2.8. Data Analysis
Financial and administrative data were first compiled and cross-checked in Excel (Microsoft, 2021), which was also used for preliminary indicator construction, verification of payment records, and conversion of costs into CFA francs (FCFA) and U.S. dollars. Standardized formulas were applied to derive core metrics such as total disbursements, average cost per vaccinator, and transport allowances, ensuring internal consistency across districts and regions.
Subsequent analysis and visualization were conducted in RStudio (Posit, 2024) using open-source packages including tidyverse, scales, knitr, and ggplot2.
The analytical workflow included:
1) descriptive summaries of operational and financial indicators under cash-based and digital modalities;
2) estimation of cost differentials at national, district, and per-vaccinator levels;
3) deterministic one-way sensitivity analysis of four key parameters (ghost worker prevalence, ghost payment uncertainty, transaction fees, and transport allowances);
4) visualization of sensitivity outputs through tornado diagrams and line plots.
The integration of Excel (Version 16.100.3) and RStudio (2025.05.1 Build 513) ensured both operational practicality for data validation and reproducibility of statistical analysis.
2.9. Ethical Considerations
Ethical approval was granted by the National Committee on Ethics in Life Sciences and Health (CNESVS) of Cote d’Ivoire. Oral informed consent was obtained from all qualitative interview participants. Financial and administrative data were anonymized before analysis and managed according to ethical research standards.
3. Results
3.1. General Campaign Overview
The October 2023 national polio immunization campaign covered all 33 regions and 113 health districts in Cote d’Ivoire, with a total operational cost of 645,570,790 FCFA (1,031,263 USD). A workforce of 30,267 vaccination agents was mobilized, of whom 29,973 (99%) were remunerated via mobile money. The digital payment system enabled the identification of 300 duplicate or phantom records—approximately three per district—highlighting inefficiencies in the prior cash-based modality (
Table 1).
Table 1. Operational and payment statistics - October 2023 campaign.
Indicator | National value |
Number of regions | 33 |
Number of health districts | 113 |
Vaccinators mobilized | 30,321 |
Vaccinators paid via digital payment | 30,281 |
Number of duplicates (ghost/duplicate workers) | 300 |
Total cost of vaccinators paid (FCFA) | 397,582,460 |
3.2. Cost of the Cash-based Payment System
Under the traditional cash modality, 397,582,460 FCFA (635,265 USD) was disbursed directly to vaccinators. In addition, 7,820,967 FCFA (12,495 USD) was spent on transport allowances for district-level fund distribution, and 3,938,930 FCFA (6,291 USD) was lost to payments made to ghost or duplicate workers. The total cost of the cash system amounted to 409,342,357 FCFA (653,168 USD), with an average cost per vaccinator of 13,518 FCFA (21.60 USD) (
Table 2).
Table 2. Cost summary - cash-based system- October 2023 polio campaign.
Cost component | Value (FCFA) |
Vaccinator payments | 397,582,460 |
Transport costs | 7,820,967 |
Ghost/duplicate payments | 3,938,929.96 |
Total cost of the intervention | 409,342,357 |
Average cost per vaccinator (FCFA) | 13,518 |
3.3. Cost of the Digital Payment System
Through mobile money, 397,582,460 FCFA (635,265 USD) was transferred to vaccinators. Transaction fees represented 1% of disbursed value, totaling 3,975,825 FCFA (6,353 USD). No transport allowances or ghost payments were incurred. The overall cost of the digital payment system was 401,558,285 FCFA (641,618 USD), corresponding to 13,261 FCFA (21.19 USD) per vaccinator (
Table 3).
Table 3. Cost summary of digital payments - October 2023 polio campaign.
Cost component | Value (FCFA) |
Total amount paid to vaccinators | 397,582,460 |
Transaction costs (1%) | 3,975,825 |
Total cost of the intervention | 401,558,285 |
Average cost per vaccinator (FCFA) | 13,261 |
3.4. Comparative Cost Analysis
Both modalities disbursed identical total payments to vaccinators (397,582,460 FCFA). However, additional costs differed: the digital system incurred only transaction fees, while the cash-based system absorbed both transport allowances and ghost payments. Consequently, the digital modality was less costly overall, producing a net saving of 7,784,073 FCFA (12,435 USD), equivalent to 257 FCFA (0.41 USD) per vaccinator (
Table 4).
Table 4. comparative cost analysis: digital payment vs. cash-based modalities.
Cost component | Digital payment (FCFA) | Cash-based payment (FCFA) |
Total amount paid to vaccinators | 397,582,460 | 397,582,460 |
Transaction costs (1%) | 3,975,825 | - |
Transport cost (to DDS) | - | 7,820,967 |
Payment to ghost/duplicate workers | - | 3,938,929.96 |
Total cost of the intervention | 401,558,285 | 409,342,357 |
Average cost per vaccinator (FCFA) | 13,261 | 13,518 |
Net cost saving | (7,784,073) |
Net cost per vaccinator | (257) |
3.5. Sensitivity Analysis
Deterministic sensitivity analysis confirmed the robustness of the cost-saving result. Across all parameter variations, digital payments remained less costly than cash disbursement.
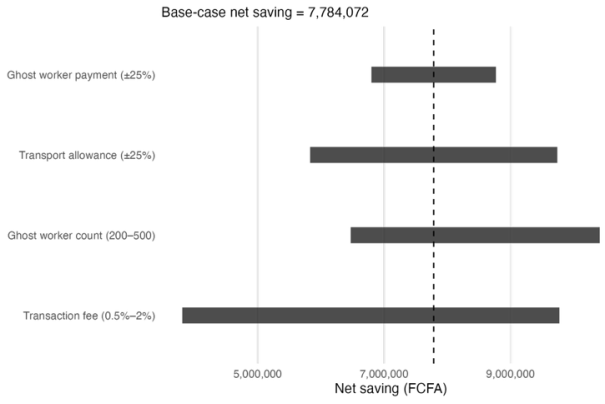
Ghost worker prevalence: varying the number of ghost workers between 200 and 500 shifted savings from 6.5 million to 10.4 million FCFA.
Ghost payment uncertainty: allowing ghost payment costs to vary ±25% produced savings between 6.8 million and 8.8 million FCFA.
Transaction fees: changing the assumed rate between 0.5% and 2% altered savings from 3.8 million to 9.8 million FCFA.
Transport allowances: applying a ±25% variation changed savings from 5.8 million to 9.7 million FCFA.
In all scenarios (
Figure 1), the digital modality generated net savings, with ghost worker prevalence exerting the largest influence on results.
Figure 1. Tornado diagram of one-way sensitivity analysis.
4. Discussion
The purpose of this study was to evaluate the cost implications of digital payments compared to traditional cash-based disbursements during Cote d’Ivoire’s October 2023 national polio immunization campaign. Using a cost-minimization framework, the analysis revealed a financial advantage for digital payments, with a net saving of approximately 7.8 million FCFA ($12,435 USD), equivalent to 257 FCFA ($0.41 USD) per vaccinator. Although this saving represents less than 2% of total disbursements, it is meaningful in the context of recurrent campaigns, constrained health budgets, and systemic benefits.
At the operational level, digital payments reduced ancillary costs linked to campaign financing. In the cash-based system, additional expenses arose from transport allowances for district health staff and disbursements to ghost or duplicate workers, both of which were avoided with digital disbursement. The only added expense was the 1% transaction fee charged for mobile transfers. Even with this fee, the digital system generated net savings at national scale. These findings are consistent with evidence from other LMICs, where government-to-person digital transfers streamlined fund flows, reduced leakage, and improved accountability. In Sierra Leone, digitizing payments to Ebola response workers reduced fraud and accelerated disbursement
| [4] | Bangura JA. Saving money, saving lives: A case study on the benefits of digitizing payments to ebola response workers in sierra leone. Better Than Cash Alliance, New York 2016. |
[4]
. In Nigeria, the WHO’s Direct Disbursement Mechanism securely paid over 200,000 vaccinators, lowering inefficiencies
| [6] | Yehualashet YG, Wadda A, Agblewonu KB, Zhema T, Ibrahim AA, Corr A, et al. World Health Organization’s Innovative Direct Disbursement Mechanism for Payment of Grassroots Immunization Personnel and Operations in Nigeria: 2004-2015. The Journal of Infectious Diseases 2016; 213: S108-15. https://doi.org/10.1093/infdis/jiv485. |
[6]
. Similar results have been documented in social protection programs, where digital transfers reduced transaction costs and improved transparency
| [2] | Agur I, Peria SM, Rochon C. Digital financial services and the pandemic: Opportunities and risks for emerging and developing economies. International Monetary Fund Special Series on COVID-19, Transactions 2020; 1: 2-1. |
| [7] | Klapper L, Singer D. The opportunities and challenges of digitizing government-to-person payments. The World Bank Research Observer 2017; 32: 211-26. |
[2, 7]
. Cote d’Ivoire’s results therefore reinforce a broader pattern: digital systems, even with modest transaction fees, tend to yield efficiency gains.
Still, the absolute magnitude of savings should not be overstated. The 7.8 million FCFA saved represents less than 2% of vaccinator payments. Yet, in health systems where budgets fall short of Abuja targets, even small reallocations can be meaningful. Such resources could fund vaccine procurement, expand outreach, or support community mobilization. Moreover, the analysis likely underestimates the true cost differential, since overhead costs of cash handling—such as reconciliation time and staff salaries—were not included. Evidence from Nigeria and Sierra Leone indicates that including these costs increases the cost advantage of digital modalities
| [4] | Bangura JA. Saving money, saving lives: A case study on the benefits of digitizing payments to ebola response workers in sierra leone. Better Than Cash Alliance, New York 2016. |
| [6] | Yehualashet YG, Wadda A, Agblewonu KB, Zhema T, Ibrahim AA, Corr A, et al. World Health Organization’s Innovative Direct Disbursement Mechanism for Payment of Grassroots Immunization Personnel and Operations in Nigeria: 2004-2015. The Journal of Infectious Diseases 2016; 213: S108-15. https://doi.org/10.1093/infdis/jiv485. |
[4, 6]
.
Beyond financial savings, digital transfers offer structural advantages. By linking payments to verifiable mobile accounts, they reduce opportunities for fraud, ghost workers, and duplicate disbursements. Digital platforms also generate transaction records that allow real-time monitoring, simplify audits, and enhance program credibility. Labrique et al.
| [3] | Labrique A, Vasudevan L, Weiss W, Wilson K. Establishing standards to evaluate the impact of integrating digital health into health systems. Global Health: Science and Practice 2018; 6: S5-17. |
[3]
emphasized the governance benefits of digital health interventions when integrated into financing systems, noting their potential to provide audit trails and accountability. In humanitarian cash transfers, digital platforms similarly lowered administrative overhead and improved trust
| [14] | World Bank. Strategic Note: Cash Transfers in Humanitarian Contexts. Washington, DC: World Bank Group; 2016. |
[14]
. Cote d’Ivoire’s findings thus reflect both financial efficiency and governance gains, both of which are critical for sustaining immunization programs.
Beyond efficiency gains, the adoption of digital payments raises critical considerations for equity and workforce performance. While digital systems improve timeliness and accountability, their sustainability relies on equitable access and positive effects on staff motivation. Persistent gaps—such as poor network connectivity and low digital literacy among older or rural workers—risk marginalizing vulnerable personnel. Evidence from African immunization programs shows that targeted digital training and hybrid (mobile-manual) approaches enhance inclusion and performance
| [11] | Hamani A, Hussein Jama I, Roland MAY, Wanjeri L, Oppon-Kusi AA, Karimi D, et al. Mobile Money and the importance of timely, complete payments to frontline health campaign workers in the fight to eradicate polio: pilot experience from a World Health Organization digital payment platform in Africa. BMC Health Services Research 2023; 23: 16. https://doi.org/10.1186/s12913-022-08990-4 |
| [15] | Kiberu VM, Scott RE, Mars M. Assessing core, e-learning, clinical and technology readiness to integrate telemedicine at public health facilities in Uganda: a health facility–based survey. BMC Health Services Research 2019; 19: 266. |
| [16] | Okereke M, Babatunde AO, Samuel ST, Ogunkola IO, Mogessie YG, Lucero-Prisno III DE. Applications of telemedicine in the supply and distribution of COVID-19 vaccines in Africa. Journal of Global Health 2021; 11: 03039. |
[11, 15, 16]
. Ensuring equitable implementation of digital payments can therefore strengthen both workforce resilience and health system fairness, aligning with universal health coverage goals.
Furthermore, although not directly measured in this study, the impact of digital payments on worker satisfaction and motivation is a crucial lever for performance. Timely and reliable remuneration is a key determinant of health worker motivation and retention, whereas delays—common in cash-based systems—undermine morale and service delivery. Evidence confirms that digital disbursements enhance timeliness and reinforce trust in program management
| [11] | Hamani A, Hussein Jama I, Roland MAY, Wanjeri L, Oppon-Kusi AA, Karimi D, et al. Mobile Money and the importance of timely, complete payments to frontline health campaign workers in the fight to eradicate polio: pilot experience from a World Health Organization digital payment platform in Africa. BMC Health Services Research 2023; 23: 16. https://doi.org/10.1186/s12913-022-08990-4 |
| [17] | Demirgüç-Kunt A, Klapper L, Singer D, Ansar S. The Global Findex Database 2021: Financial inclusion, digital payments, and resilience in the age of COVID-19. World Bank Publications; 2022. |
| [18] | Ford E. The potential of digital cash transfers to strengthen the link between humanitarian assistance and social protection 2017. |
[11, 17, 18]
. Although our study did not directly measure worker satisfaction, consistent external findings suggest that the predictability of mobile money payments can reduce absenteeism and strengthen campaign reliability. Thus, the documented cost savings represent only a fraction of the total benefit; a more motivated and stable workforce constitutes a crucial performance dividend. Future research should systematically quantify this link between payment modality and operational outcomes.
Cote d’Ivoire’s experience fits within a wider African trend of leveraging mobile money for health and social programs. i and Kenya, digital transfers to community health workers were both cost-saving and associated with improved productivity
| [13] | Wagaba MT, Musoke D, Opio C, Bagonza A, Aweko J, Nakitende H, et al. Do cash or digital payment modalities affect community health worker performance? - a case study of a remote refugee settlement in Western Uganda. Global Health Action 2024; 17: 2375867. https://doi.org/10.1080/16549716.2024.2375867. |
[13]
. In Nigeria and Sierra Leone, digital disbursement mechanisms improved timeliness, reduced leakage, and supported epidemic response
| [4] | Bangura JA. Saving money, saving lives: A case study on the benefits of digitizing payments to ebola response workers in sierra leone. Better Than Cash Alliance, New York 2016. |
| [6] | Yehualashet YG, Wadda A, Agblewonu KB, Zhema T, Ibrahim AA, Corr A, et al. World Health Organization’s Innovative Direct Disbursement Mechanism for Payment of Grassroots Immunization Personnel and Operations in Nigeria: 2004-2015. The Journal of Infectious Diseases 2016; 213: S108-15. https://doi.org/10.1093/infdis/jiv485. |
[4, 6]
. Globally, digital payments in humanitarian programs have yielded comparable results, improving transparency and beneficiary satisfaction
| [14] | World Bank. Strategic Note: Cash Transfers in Humanitarian Contexts. Washington, DC: World Bank Group; 2016. |
| [18] | Ford E. The potential of digital cash transfers to strengthen the link between humanitarian assistance and social protection 2017. |
[14, 18]
. This convergence across diverse contexts—from emergency response to routine health campaigns—underscores the robustness of digital systems as a scalable financing tool. Cote d’Ivoire’s findings therefore add to a consistent narrative: digital payments are not isolated innovations but proven approaches with broad applicability.
Limitations
This evaluation has several limitations. First, some cost components were not captured, including administrative overhead, reconciliation time, and staff salaries in the cash system, as well as coordination and IT support under the digital system. These omissions likely produced conservative estimates, understating the true savings from digital disbursement. Future evaluations should therefore incorporate administrative and coordination costs into standardized costing frameworks to support more comprehensive fiscal planning and inform government budgeting for digital health interventions.
Second, the use of a cost-minimization framework requires the assumption of equivalent outputs across payment modalities. While campaign data indicated similar immunization coverage, digital systems may generate additional effects, such as greater timeliness, improved worker satisfaction, or reduced absenteeism. If such outcomes differ, then digital payments could produce benefits beyond financial efficiency, and alternative approaches such as cost-effectiveness or cost-utility analyses would be warranted.
Third, the analysis was confined to a single campaign round. Multi-round or multi-year evaluations would provide stronger evidence on sustainability and recurring savings. While our findings suggest clear short-term efficiency gains, the long-term sustainability of digital payment systems—particularly their institutionalization within public financial management frameworks—cannot be inferred from one campaign alone. Sustainability depends on continued political commitment, technical interoperability, and recurrent funding to maintain digital infrastructure and training. Future longitudinal studies should therefore examine whether these systems remain functional, equitable, and cost-saving over multiple immunization cycles.
Policy Implications
For policymakers, the relevance of these results extends beyond a single campaign. Institutionalizing digital payments in Cote d’Ivoire could reduce recurrent inefficiencies in health financing, support financial inclusion, and align with global commitments to digital public infrastructure. Priorities include ensuring interoperability across mobile money providers, protecting user rights through regulatory safeguards, and embedding digital transfers into national financial management systems. These recommendations echo calls from the World Bank, WHO, and Gavi to integrate digital financial services into health systems as a pathway to greater transparency and efficiency
| [7] | Klapper L, Singer D. The opportunities and challenges of digitizing government-to-person payments. The World Bank Research Observer 2017; 32: 211-26. |
[7]
. Moreover, by linking health financing to mobile money platforms, governments can contribute to broader financial inclusion, enabling unbanked frontline workers to participate in the digital economy
| [17] | Demirgüç-Kunt A, Klapper L, Singer D, Ansar S. The Global Findex Database 2021: Financial inclusion, digital payments, and resilience in the age of COVID-19. World Bank Publications; 2022. |
[17]
.
5. Conclusion
This study provides empirical evidence that digital payment systems can reduce the financial costs of large-scale immunization campaigns by eliminating transport allowances and ghost payments, despite modest transaction fees. During Cote d’Ivoire’s October 2023 polio campaign, mobile money disbursements generated net savings of 7.8 million FCFA ($12,435 USD), or 257 FCFA ($0.41 USD) per vaccinator. Although modest in relative terms, these savings gain significance when considered across recurrent campaigns and within constrained health budgets. Beyond cost, digital payments strengthen transparency, accountability, and workforce trust, aligning with broader health system objectives. Institutionalizing digital disbursement mechanisms could therefore enhance financial sustainability, promote inclusion of frontline workers in the digital economy, and contribute to progress toward Universal Health Coverage. Further evaluations incorporating effectiveness outcomes are warranted to capture their full value.
Abbreviations
BCEAO | Central Bank of West African States |
CNESVS | National Committee on Ethics in Life Sciences and Health |
DDS | District Health Director |
DFS | Digital Financial Services |
EPI | Expanded Program on Immunization |
FCFA | African Financial Community Franc |
G2P | Government-to-Person (Payments) |
Gavi | Gavi, the Vaccine Alliance |
GSMA | GSM Association |
IT | Information Technology |
LMICs | Low- and Middle-Income Countries |
UHC | Universal Health Coverage |
UNICEF | United Nations Children’s Fund |
USD | United States Dollar |
WHO | World Health Organization |
Acknowledgments
The authors acknowledge the invaluable contributions of all national institutions involved in the organization and delivery of the October 2023 polio immunization campaign in Cote d’Ivoire. Special recognition is extended to the Ministry of Health and its partners, including the World Health Organization, UNICEF, and Gavi, whose financial and technical support made the campaign possible. Their collective efforts demonstrate a sustained commitment to strengthening health systems and improving population health in Cote d’Ivoire.
Author Contributions
Bangaman Christian Akani: Conceptualization, Formal Analysis, Methodology, Software, Visualization, Writing – original draft
Ama Kounangui Marie Noelle Ano: Validation, Writing – review & editing
Loukou Gilbert Konan: Validation, Writing – review & editing
Roméo Kouassi: Methodology, Writing – review & editing
Awa Madaho Sokodogo: Methodology, Writing - review & editing
Ekissi Orsot Tetchi: Writing - review & editing
Eugène Konan: Writing - review & editing
Petronille Acray-Zengbé: Supervision, Writing – review & editing
Funding
This research received no specific grant from any funding agency, commercial, or not-for-profit sectors.
Data Availability Statement
The data is available from the corresponding author upon reasonable request.
Conflicts of Interest
The authors declare no conflicts of interest.
References
| [1] |
Meagher P. Cadre réglementaire pour les services financiers numériques en Côte d’Ivoire 2017.
|
| [2] |
Agur I, Peria SM, Rochon C. Digital financial services and the pandemic: Opportunities and risks for emerging and developing economies. International Monetary Fund Special Series on COVID-19, Transactions 2020; 1: 2-1.
|
| [3] |
Labrique A, Vasudevan L, Weiss W, Wilson K. Establishing standards to evaluate the impact of integrating digital health into health systems. Global Health: Science and Practice 2018; 6: S5-17.
|
| [4] |
Bangura JA. Saving money, saving lives: A case study on the benefits of digitizing payments to ebola response workers in sierra leone. Better Than Cash Alliance, New York 2016.
|
| [5] |
Drummond M. Methods for the economic evaluation of health care programmes. Fourth edition. Oxford, United Kingdom; New York, NY, USA: Oxford University Press; 2015.
|
| [6] |
Yehualashet YG, Wadda A, Agblewonu KB, Zhema T, Ibrahim AA, Corr A, et al. World Health Organization’s Innovative Direct Disbursement Mechanism for Payment of Grassroots Immunization Personnel and Operations in Nigeria: 2004-2015. The Journal of Infectious Diseases 2016; 213: S108-15.
https://doi.org/10.1093/infdis/jiv485.
|
| [7] |
Klapper L, Singer D. The opportunities and challenges of digitizing government-to-person payments. The World Bank Research Observer 2017; 32: 211-26.
|
| [8] |
World Health Organization. Seventy-first world health assembly, agenda item 12.4, digital health 2021.
|
| [9] |
WHO. Mobile cash in polio response: three things to know | WHO | Regional Office for Africa. World Health Organization 2025.
https://www.afro.who.int/news/mobile-cash-polio-response-three-things-know
(accessed April 16, 2025).
|
| [10] |
Gentili A, Failla G, Melnyk A, Puleo V, Tanna GLD, Ricciardi W, et al. The cost-effectiveness of digital health interventions: a systematic review of the literature. Frontiers in Public Health 2022; 10: 787135.
|
| [11] |
Hamani A, Hussein Jama I, Roland MAY, Wanjeri L, Oppon-Kusi AA, Karimi D, et al. Mobile Money and the importance of timely, complete payments to frontline health campaign workers in the fight to eradicate polio: pilot experience from a World Health Organization digital payment platform in Africa. BMC Health Services Research 2023; 23: 16.
https://doi.org/10.1186/s12913-022-08990-4
|
| [12] |
Wang Y, Fekadu G, You JH. Cost-Effectiveness Analyses of Digital Health Technology for Improving the Uptake of Vaccination Programs: Systematic Review. J Med Internet Res 2023; 25: e45493.
https://doi.org/10.2196/45493
|
| [13] |
Wagaba MT, Musoke D, Opio C, Bagonza A, Aweko J, Nakitende H, et al. Do cash or digital payment modalities affect community health worker performance? - a case study of a remote refugee settlement in Western Uganda. Global Health Action 2024; 17: 2375867.
https://doi.org/10.1080/16549716.2024.2375867.
|
| [14] |
World Bank. Strategic Note: Cash Transfers in Humanitarian Contexts. Washington, DC: World Bank Group; 2016.
|
| [15] |
Kiberu VM, Scott RE, Mars M. Assessing core, e-learning, clinical and technology readiness to integrate telemedicine at public health facilities in Uganda: a health facility–based survey. BMC Health Services Research 2019; 19: 266.
|
| [16] |
Okereke M, Babatunde AO, Samuel ST, Ogunkola IO, Mogessie YG, Lucero-Prisno III DE. Applications of telemedicine in the supply and distribution of COVID-19 vaccines in Africa. Journal of Global Health 2021; 11: 03039.
|
| [17] |
Demirgüç-Kunt A, Klapper L, Singer D, Ansar S. The Global Findex Database 2021: Financial inclusion, digital payments, and resilience in the age of COVID-19. World Bank Publications; 2022.
|
| [18] |
Ford E. The potential of digital cash transfers to strengthen the link between humanitarian assistance and social protection 2017.
|
Cite This Article
-
APA Style
Akani, B. C., Ano, A. K. M. N., Konan, L. G., Kouassi, R., Sokodogo, A. M., et al. (2025). Economic Evaluation of Mobile Payments for Health Workers in Vaccination Programs: A Case Study from Cote d’Ivoire. Central African Journal of Public Health, 11(6), 335-342. https://doi.org/10.11648/j.cajph.20251106.11
 Copy
|
 Download
ACS Style
Akani, B. C.; Ano, A. K. M. N.; Konan, L. G.; Kouassi, R.; Sokodogo, A. M., et al. Economic Evaluation of Mobile Payments for Health Workers in Vaccination Programs: A Case Study from Cote d’Ivoire. Cent. Afr. J. Public Health 2025, 11(6), 335-342. doi: 10.11648/j.cajph.20251106.11
Copy
|
Download
AMA Style
Akani BC, Ano AKMN, Konan LG, Kouassi R, Sokodogo AM, et al. Economic Evaluation of Mobile Payments for Health Workers in Vaccination Programs: A Case Study from Cote d’Ivoire. Cent Afr J Public Health. 2025;11(6):335-342. doi: 10.11648/j.cajph.20251106.11
Copy
|
Download
-
@article{10.11648/j.cajph.20251106.11,
  author = {Bangaman Christian Akani and Ama Kounangui Marie Noelle Ano and Loukou Gilbert Konan and Roméo Kouassi and Awa Madaho Sokodogo and Ekissi Orsot Tetchi and Eugène Konan and Petronille Acray-Zengbé},
  title = {Economic Evaluation of Mobile Payments for Health Workers in Vaccination Programs: A Case Study from Cote d’Ivoire
},
  journal = {Central African Journal of Public Health},
  volume = {11},
  number = {6},
  pages = {335-342},
  doi = {10.11648/j.cajph.20251106.11},
  url = {https://doi.org/10.11648/j.cajph.20251106.11},
  eprint = {https://article.sciencepublishinggroup.com/pdf/10.11648.j.cajph.20251106.11},
  abstract = {Background: Timely and reliable remuneration of frontline health workers is critical for vaccination campaign performance, yet in many low- and middle-income countries cash-based disbursement remains vulnerable to delays, leakage, and inefficiencies. These weaknesses undermine accountability and create recurrent financial burdens, particularly in large-scale operations such as polio immunization campaigns. Objective: This study aimed to evaluate the cost implications of shifting from traditional cash payments to digital disbursement through mobile money during Cote d’Ivoire’s October 2023 national polio immunization campaign. Method: A partial economic evaluation was conducted using a top-down costing approach from the payer’s perspective. Data from all 113 districts and 33 regions were analyzed to compare cash-based and mobile money systems. The analysis focused on direct financial costs, including transaction fees (digital) and transport allowances or ghost worker disbursements (cash). A cost-minimization framework was applied under the assumption of equivalent immunization outputs, and deterministic sensitivity analysis was performed to test robustness. Result: Both systems disbursed the same total amount to vaccinators (397,582,460 FCFA). However, cash payments incurred additional costs of 7,820,967 FCFA in transport and 3,938,930 FCFA in ghost payments, while digital payments generated a 1% transaction fee (3,975,825 FCFA). The digital modality produced a net saving of 7,784,073 FCFA (12,435 USD), or 257 FCFA (0.41 USD) per vaccinator. Sensitivity analysis confirmed the stability of these savings across plausible parameter variations. Conclusion: Digital disbursement via mobile money offers a cost-saving and governance-enhancing alternative to cash payments in vaccination campaigns. Although the absolute savings represent less than 2% of total outlays, the benefits in efficiency, fraud reduction, and transparency are significant for health systems facing budget constraints. Cote d’Ivoire’s experience provides evidence for policymakers to consider institutionalizing digital payments to strengthen financial sustainability and support universal health coverage.
},
 year = {2025}
}
Copy
|
Download
-
TY  - JOUR
T1  - Economic Evaluation of Mobile Payments for Health Workers in Vaccination Programs: A Case Study from Cote d’Ivoire

AU  - Bangaman Christian Akani
AU  - Ama Kounangui Marie Noelle Ano
AU  - Loukou Gilbert Konan
AU  - Roméo Kouassi
AU  - Awa Madaho Sokodogo
AU  - Ekissi Orsot Tetchi
AU  - Eugène Konan
AU  - Petronille Acray-Zengbé
Y1  - 2025/10/30
PY  - 2025
N1  - https://doi.org/10.11648/j.cajph.20251106.11
DO  - 10.11648/j.cajph.20251106.11
T2  - Central African Journal of Public Health
JF  - Central African Journal of Public Health
JO  - Central African Journal of Public Health
SP  - 335
EP  - 342
PB  - Science Publishing Group
SN  - 2575-5781
UR  - https://doi.org/10.11648/j.cajph.20251106.11
AB  - Background: Timely and reliable remuneration of frontline health workers is critical for vaccination campaign performance, yet in many low- and middle-income countries cash-based disbursement remains vulnerable to delays, leakage, and inefficiencies. These weaknesses undermine accountability and create recurrent financial burdens, particularly in large-scale operations such as polio immunization campaigns. Objective: This study aimed to evaluate the cost implications of shifting from traditional cash payments to digital disbursement through mobile money during Cote d’Ivoire’s October 2023 national polio immunization campaign. Method: A partial economic evaluation was conducted using a top-down costing approach from the payer’s perspective. Data from all 113 districts and 33 regions were analyzed to compare cash-based and mobile money systems. The analysis focused on direct financial costs, including transaction fees (digital) and transport allowances or ghost worker disbursements (cash). A cost-minimization framework was applied under the assumption of equivalent immunization outputs, and deterministic sensitivity analysis was performed to test robustness. Result: Both systems disbursed the same total amount to vaccinators (397,582,460 FCFA). However, cash payments incurred additional costs of 7,820,967 FCFA in transport and 3,938,930 FCFA in ghost payments, while digital payments generated a 1% transaction fee (3,975,825 FCFA). The digital modality produced a net saving of 7,784,073 FCFA (12,435 USD), or 257 FCFA (0.41 USD) per vaccinator. Sensitivity analysis confirmed the stability of these savings across plausible parameter variations. Conclusion: Digital disbursement via mobile money offers a cost-saving and governance-enhancing alternative to cash payments in vaccination campaigns. Although the absolute savings represent less than 2% of total outlays, the benefits in efficiency, fraud reduction, and transparency are significant for health systems facing budget constraints. Cote d’Ivoire’s experience provides evidence for policymakers to consider institutionalizing digital payments to strengthen financial sustainability and support universal health coverage.

VL  - 11
IS  - 6
ER  -
Copy
|
Download

 ,
Ama Kounangui Marie Noelle Ano



 Share This Article
 Twitter
 Linked In
 Facebook