Research Article | | Peer-Reviewed

Rethinking the Dynamics of Healthcare Funding, Maternal Health Status and Lifespan Inequality Among Women in the ECOWAS Region

Received: 20 April 2025     Accepted: 3 May 2025     Published: 12 June 2025
Views:       Downloads:
Abstract

Motivated by the widening gap in lifespan within and between countries and across age groups, this study quantifies the implications of public health expenditure, out-of-pocket healthcare payments and maternal health conditions such as the prevalence of obesity and anaemia on lifespan inequality among women in five anglophone countries (Ghana, Liberia, Nigeria, Sierra Leone, and The Gambia) and five francophone countries (Senegal, Niger, Mali, Guinea and Togo) in the ECOWAS region. Heterogeneous panel estimation involving mean group (MG) and pooled mean group (PMG) estimators alongside unit root tests and descriptive statistics formed the basis for the analysis. Findings indicate that public health expenditure does not significantly reduce the disparity in lifespan in both the short and long run. This highlights the need for more effective public healthcare financing that will increase healthcare access and prioritise healthcare in reinvestments of the savings from subsidy removal, while mitigating corruption. Further analysis showed that out-of-pocket healthcare payments significantly reduced inequality in the length of life of women in both the short and long run. This highlights the efficacy of out-of-pocket healthcare payments in promoting uniformity in the ages of death of women. However, the findings showed that the prevalence of obesity and anaemia among women worsened the lifespan inequality during the study period. This explains the need to address underlying health conditions in women through healthy diets and regular physical exercise. Given the findings, this study recommends boosting the purchasing power of women for more independent financial decisions to improve equality in their longevity. Again, targeted conditional cash transfers should be provided to vulnerable women to boost their out-of-pocket healthcare payments for a more equal lifespan.

Published in International Journal of Health Economics and Policy (Volume 10, Issue 2)
DOI 10.11648/j.hep.20251002.15
Page(s) 67-76
Creative Commons

This is an Open Access article, distributed under the terms of the Creative Commons Attribution 4.0 International License (http://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, distribution and reproduction in any medium or format, provided the original work is properly cited.

Copyright

Copyright © The Author(s), 2025. Published by Science Publishing Group

Keywords

Lifespan Inequality, Health Expenditure, Out-of-pocket Payments, Maternal Health, Women and ECOWAS

1. Introduction
Understanding the dynamics of lifespan inequality, which summarises the life expectancy gap within and between countries and across age groups, has become an important area of research for economists and healthcare practitioners. This has received wide recognition in the extant literature, as it provides an opportunity for improving global health standards by allowing countries to learn from one another and collaborate in areas of need. identify public healthcare expenditure as critical to achieving population-wide gains in longevity, which can reduce the inequality in ages of death. This follows assertion that public health expenditures tend to alter healthcare delivery systems and utilisation patterns. For instance, posit that expenditure on healthcare has the potential to enhance healthcare opportunities in terms of accessibility, quality, and distribution of healthcare services to boost human capital while increasing productivity. It is also believed that public healthcare expenditure can increase the extent of healthcare utilisation, especially among the poor, by making healthcare services more accessible and affordable. identifies demographic change, especially changes in the size and structure of the population, as a critical factor that drives changes in public healthcare funding.
While evidence on the changing dimensions of public health expenditure amidst the seemingly poor health outcomes in emerging and developing economies, some previous studies such as found evidence to debunk the efficacy of public health expenditure in these countries. As a share of private health expenditures, out-of-pocket expenditures account for a significant proportion of total health expenditures. This may undermine the well-being of households due to the unprecedented increase in health expenditure, which can exacerbate poverty . Thus, relying only on out-of-pocket spending to meet healthcare needs has been viewed as problematic, with the World Bank advocating for increased government health expenditure.
Besides, healthcare financing, maternal health status has been identified in extant literature to affect disparity in longevity among women across age groups. According to the World Health Organisation , the incidence of overweight and obesity among adult women worldwide increased from 6.4% in 1975 to 13% in 2016. The WHO report also showed that 44% of adult women globally were classified as obese in 2023 . This growing health challenge has continued to threaten longevity due to rising medical costs and poor quality of life . Although global attention has been drawn to the increasing health risk of overweight and obesity among women, recent studies have shown these health challenges are increasing in all African regions . Again, adult women globally are faced with the health risk of anaemia, which poses a threat to their life expectancies. About 39% of women of reproductive in sub-Saharan Africa (SSA) were anaemic in 2016 . This is largely attributed to blood losses associated with the women's development process, which undermines their health status.
Despite numerous policies and initiatives aimed at improving the overall lifespan of women through healthcare financing and improvement in maternal health, the discrepancies in the lifespan of women across West African countries have remained a source of worry to policymakers, academics and researchers, among others. The 2024 report of the Human Mortality Database showed that the Gini coefficients for lifespan inequality in women in 2023 are 0.17, 0.2807, 0.19 and 0.23 for Ghana, Nigeria, Liberia, and Guinea, respectively. This suggests that there are more uniform ages of death among women in Ghana and Liberia than in Nigeria and Guinea during the study period. Additionally, Gini coefficients of 0.14, 0.22, and 0.17 were reported for Senegal, Niger and the Gambia in 2023, indicating that Senegal tends to experience little or no variability in the ages of death of women. Against this backdrop, this study examined how health expenditure and maternal health status affected the variability in the length of life of women in the ECOWAS sub-region. Thus, this study sheds light on how the interplay of public health expenditure, out-of-pocket payments, prevalence of obesity and anaemia contributed to lifespan inequality in women in selected ECOWAS member countries. The rest of the study is structured as follows: Section II presents the related literature and stylised facts, methodology and data sources are presented in Section III; the results and discussion are presented in Section IV, and the conclusion is given in Section V.
2. Related Literature
Lifespan inequality is an indicator of health outcomes that represents the variability in a population's length of life or disparity in individuals’ age at death. In particular, it shows the level of inequality in lifespans within a country as captured by the Gini coefficient, with a higher coefficient indicating greater inequality in ages of death. In comparison, a lower coefficient indicates more uniform ages of death. Health expenditure is believed to improve health outcomes, including life expectancy at birth, thus creating opportunities for mitigating inequality in lifespans. The growth theory highlighted the need to increase public health expenditure, notwithstanding the demand. Although this proposition has generated controversies among economists and policymakers, it explains the importance of government in accounting for a large share of health expenditure to increase healthcare access and affordability, and lower mortality rates, particularly among vulnerable populations. endogenous growth theory also justified government expenditure to drive human capital for sustainable growth. Essentially, theory identifies human capital in terms of investment in education and health as an important enabler of optimal economic development, including improvement in longevity. More so, the health production function assumes that various inputs, including health spending, healthcare services, public health campaigns, and socioeconomic variables, affect health outcomes. This idea suggests that higher health spending could lead to improved health outcomes, such as longer life expectancy and reduced mortality rates. It follows from this theory that increasing health spending offers opportunities for better health outcomes, such as increased life expectancy and reduced lifespan inequality.
Furthermore, several studies have empirically analysed how health expenditures contribute to health outcomes, including life expectancy at birth, lifespan inequality, healthy life expectancy, and disability-adjusted life expectancy. The findings of these studies vary across jurisdictions, timeframes and methodologies. Some of these studies showed that public health expenditure significantly improves life expectancy and reduces variability in ages of death globally and across sexes . On the other hand, studies such as reported that obesity and anaemia widened the gap in lifespan among the population, including women in developing economies. The findings explain that poor health status in the form of obesity and anaemia poses great health risks as they are mostly linked to chronic health conditions, which lower life expectancy and overall quality of health.
In light of the literature reviewed, this study fills the existing gap by considering both health expenditure and health conditions (prevalence of obesity and anaemia) in analysing inequality in the lifespan of women. This expands the health production function in the extant literature as it incorporates various health inputs to understand how they shape the disparity in lifespan in women. By focusing on lifespan inequality, this study provides the basis for understanding the differences in lifespans or age at death among women, while most of the previous studies that restricted their attention to life expectancy. This study cuts across Anglophone and francophone countries in the ECOWAS, thus providing a wider scope for understanding how heterogeneity of the effectiveness of health expenditure, obesity and incidence of anaemia in driving health outcomes from a regional perspective.
Stylised Facts on the Dynamics of Lifespan Inequality and Health Expenditure
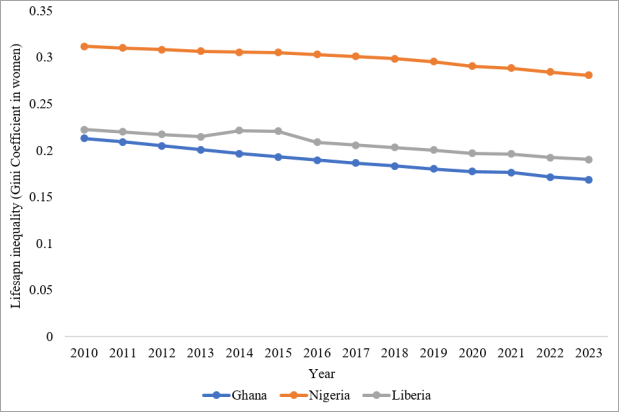
Over the past decade, disparities in lifespan among women have exhibited different patterns between and within countries in the ECOWAS region, as summarised in Figure 1 and Tables 1 and 2.
Source: Author’s compilation based on data from the Human Mortality Database (2024)

Download: Download full-size image

Figure 1. Trajectory of lifespan inequality among women in Ghana, Nigeria and Liberia, 2010-2023.
Figure 1 shows that among three sampled anglophone West African countries, Ghana has the lowest Gini coefficient in women compared to Nigeria and Liberia over the study period (2010-2023). This suggests evidence of more uniform ages of death among Ghanaian women as the Gini coefficient declined gradually from 0.213 in 2010 to an all-time low level of 0.1686 in 2023. This could be partly attributed to an increase in healthcare financing, as public healthcare expenditure in Ghana as a share of GDP increased from 1.8% in 2018 to 2.2% in 2021 (WHO, 2025). This is contrary to Nigeria’s experience, as the public healthcare expenditure in the country accounted for only 0.5% of the GDP in 2021. In addition, Figure 1 also shows that Liberia surpassed Nigeria in terms of the reduction in lifespan inequality in women as the country experienced a lower Gini coefficient than Nigeria between 2010 and 2023. This is a pointer that women in Liberia tend to experience lower inequality in the age of death compared to their Nigerian counterparts. Besides the anglophone West African countries, the experience of some selected francophone West African countries regarding lifespan inequality among women is summarized in Table 1.
Table 1. Summary of the average Gini coefficient for lifespan inequality for five francophone West African countries over the sampled periods.

Country

2010-2-2014

2015-2019

2020-2023

Senegal

0.1682

0.1513

0.1401

Niger

0.2553

0.2398

0.2295

Guinea

0.2608

0.2466

0.2326

Togo

0.2373

0.2186

0.2022

Mali

0.2577

0.2380

0.2219

Source: Author’s compilation based on data from the Human Mortality Database (2024)
The summary statistics in Table 1 showed that Senegal surpassed the other four selected countries (Niger, Guinea, Togo and Mali) in terms of reduction in lifespan inequality among women. The country’s achievements are evidenced in the decline in the average Gini coefficient from 0.1682 in the 2010-2014 period to 0.1513 and 0.1401 in the 2015-2019 and 2020-2023 periods respectively. This highlights uniformity in the ages of death of Senegalese women over the sampled periods. Togo is next to Senegal following the country’s performance in terms of reducing the gap in lifespan inequality among women given that the Gini coefficient declined from an average of 0.2373 in the 2010-2014 period to 0.2022 in the 2020-2023 period. Other countries in the sample including Niger, Guinea and Mali also made commendable progress in mitigating the disparity in the ages of death of women as their respective average Gini coefficients declined during the selected periods.
In addition, available statistics from documentary sources show that public health expenditures including public healthcare expenditure as a share of GDP and out-of-pocket payments as a percent of total current healthcare expenditures have varied in most of the countries in the ECOWAS region, as presented in Table 2.
Table 2. Summary of average public health expenditure and out-of-pocket payments in selected countries in the ECOWAS region.

Country

Public health expenditure (% of GDP)

Out-of-pocket payments (% of total health expenditure)

2015-2019

2020-2023

2015-2019

2020-2023

Nigeria

0.512%

0.517%

74.38%

75.02%

Ghana

1.69%

2.19%

34.33%

27.77%

The Gambia

1.14%

1.94%

24.61%

19.04%

Liberia

1.41%

1.04%

47.68%

28.68%

Sierra Leone

1.04%

1.604%

49.49%

44.92%

Senegal

1.07%

1.38%

49.59%

51.99%

Niger

1.58%

2.19%

50.71%

43.37%

Togo

0.99%

0.74%

62.62%

66.61%

Guinea

0.65%

0.75%

58.01%

55.75%

Mali

1.12%

1.33%

34.21%

38.49%

Source: Author’s compilation based on data from the World Health Organization (2025)
Table 2 shows that Nigeria's public health expenditure is the lowest among the sampled countries and it is less than the recommended 5% of GDP by the WHO. This could be attributed to poor budgetary allocation to the health sector and unstable oil revenue, among others. However, Nigeria surpassed all the countries in terms of out-of-pocket healthcare payments. This suggests that most Nigerians pay directly for health services when needed which could be linked to poor public health insurance coverage and limited private health insurance options. Ghana and Niger witnessed the highest public health expenditure in the 2020-2023 period. This could attributed to the countries’ Covid and post-Covid experience. Overall, out-of-pocket healthcare payments substantially exceeded public health expenditures in each of the countries over the 2015-2019 and 2020-2013 periods, indicating that individuals cater for a larger portion of their healthcare costs when seeking healthcare services.
3. Methodology
3.1. Model Specification
Following the health production function, the model for this study is patterned after the work of with an improvement due to the gendered approach to lifespan inequality and integration of both public health expenditure and out-of-pocket payments in measuring healthcare funding. The model set-up also captured the prevalence of obesity and anaemia among women which are theoretically and empirically linked to disparity in the ages of death of women in developing economies including Africa. The formal specification of the functional model is provided as:
LSI= f (PEX,OOP,IOB,IAN)(1)
Where: LSI = Lifespan inequality among women, PEX = public health expenditure, OOP = out-of-pocket payments, IOB = incidence of obesity among women and IAN = incidence of anaemia among women.
The pooled regression model for this study is specified as:
LSIit=θ+π1PEXit2OOPit3IOBt4IANit+it,i = 1,..., N. t = 1,..., T(2)
Where: Where: θ = homogenous intercept, π1 – π4 = common slope parameters, it = error term, i = cross-sectional units comprising the ten selected countries in the ECOWAS sub-region and t = time frame (2000 to 2023).
More importantly, the panel autoregressive distributed lag (ARDL) model for this study is specified as follows:
LSIit=θiLSIit-˄1iPEXit-1-˄2iOOPit-1-˄3iIOβit-1-˄4iIANit-1+j=1pβijLSJit-j+j=0qβijPEXit-j+j=0qβijOOPit-j+j=0qβijIOBit-j+j=0qβit-jIANit-j+μi+Vit (3)
Where: ˄i = long run parameters, βij and βij = short run parameters, p and q = optimal lag orders, θi = error correction coefficient, μi= individual effects and Vit = remainder disturbance term.
A priori, it is expected that the public health expenditure and out-of-pocket payments will negatively affect lifespan inequality, thus reducing the gap in the ages of death among women. However, the incidence of obesity and anaemia in women would have a positive effect on lifespan inequality by widening the gap in the length of life of women.
3.2. Estimation Strategy
To control for spurious results and identify the respective order of integration, the stationarity properties of each of the variables were evaluated using panel unit root tests. In particular, methods were applied to test the null hypothesis of unit root with a common process. This is complemented by unit root methods to test the null hypothesis of a unit root with the individual process. Panel cointegration test involving the method was equally conducted in this study to ascertain if the variables have a long-run relationship. The Mean Group (MG) estimator developed by and the Pooled Mean Group (PMG) estimator attributed to formed the basis for estimating the PARDL model specified for this research. The choice of these estimators was motivated by the fact that the MG estimator permits differences between groups in the intercept, all of the coefficients, and error variance, whereas the PMG estimator only permits differences between groups in the intercept and short-run coefficients but requires that the long-run coefficients be equal. test was relied upon to choose between the two competing estimators and PMG is the restricted model under the null, whereas the MG is the unrestricted under the alternative hypothesis.
3.3. Variable Description/Measurement and Data Sources
The summary of the variable description, data scope, frequency and source(s) is presented in Table 3.
Table 3. Summary of variable description/measurement, data scope and sources.

Variable

Description/measurement

Data scope

Source(s)

Lifespan Inequality (LSI)

This refers to the variability in the length of life of women. It is measured by the Gini coefficient of lifespan inequality in women which ranges between 0 and 1 with a higher coefficient suggesting inequality in ages of death, while a lower coefficient implies more uniform ages of death.

2010-2023

Human Mortality Database (2024)

Public health expenditure

This refers to the overall domestic government expenditure measured as a percentage of GDP.

2010-2023

World Health Organization (2025)

Out-of-pocket payments

This defines the household expenditure on healthcare services expressed as a share of total current healthcare expenditure.

2010-2023

World Health Organization (2025)

Incidence of obesity

This is measured by the share of women with body mass index (BMI) equal to or greater than 25.

2010-2023

World Health Organization - Global Health Observatory (2024)

Incidence of anaemia

This refers to the inadequacy of healthy red blood cells or haemoglobin in women. It is measured by the percentage of women of reproductive age (aged 15-49) with anaemia.

2010-2023

World Bank (2025)

Source: Author’s compilation (2025)
4. Results and Discussion
4.1. Descriptive Statistics
The descriptive statistics for each of the variables over the study period are presented in Table 4.
Table 4. Summary statistics for the variables.

Variable

Observation

Mean

Std. dev.

Minimum

Maximum

LSI

240

.2471

.0507

.1354

.3776

PEX

240

1.063

.4979

.2406

2.425

OOP

240

51.552

17.036

9.848

85.052

IOB

240

32.015

4.618

19.7

41

IAN

240

51.451

5.776

35.4

62.9

Source: STATA output (2025)
The descriptive statistics showed that the Gini coefficient of lifespan inequality averaged 0.247 and evolved from a minimum value of 0.1354 to a record maximum value of.3776. The standard deviation of.0507 for the lifespan inequality is less than the corresponding mean value (0.247), indicating that the selected countries in the study tend to experience a uniform age of death among women during the study period. Table 4 also shows that public health expenditure as a percentage of GDP averaged 1.063% during the study period. This is less than the 5% share of GDP that is recommended by the WHO to improve access to healthcare services. It further explains the poor prioritisation of health funding by successive governments in the study area. The results also showed that out-of-pocket payments averaged 51.552% with minimum and maximum values of 9.848% and 85.05%, respectively. This indicates that out-of-pocket payments for healthcare account for a large proportion of total health expenditure, thus placing a huge financial burden on households and worsening the issue of poverty in the ECOWAS region. In addition, the results showed that the share of women who are obese averaged 32.015% during the study period. This attests to the prevalence of obesity among women in the region. In a similar pattern, the share of women of reproductive age who are anaemic averaged 51.45% with minimum and maximum values of 35.4% and 62.9%, respectively. This could be attributed to the significant blood loss linked to menstruation, pregnancy and childbirth in women. This is not consistent with WHO's recommendation that health expenditure should account for a minimum of 5% of GDP to improve access to healthcare services. This finding highlights the poor healthcare financing in the study area.
4.2. Panel Unit Root Test
The unit root test results showed that lifespan inequality is not stationary at levels. Thus, the null hypothesis of the unit root cannot be rejected at the 5% level. However, the variable (lifespan inequality) was found to be stationary at the first difference, indicating that it is integrated of order one, I(1). On the other hand, public health expenditures and out-of-pocket healthcare payments are stationary at levels. This finding is supported by three out of the five test results, indicating that the variables are integrated of order zero, I(0). A similar pattern of stationarity was observed for the incidence of obesity and anaemia as the two variables are also integrated of order zero, I(0). In sum, evidence of mixed integration was established from the panel unit root test results.
Table 5. Summary of the panel unit root test results.

Test method

LSI

PEX

OOP

IOB

IAN

Levels

1st Diff.

Levels

1st Diff.

Levels

1st Diff.

Levels

1st Diff.

Levels

1st Diff.

Null Hypothesis: Unit root with common process

LLC (t*)

-3.42***

-

-1.28

-7.23***

-2.86***

-

-6.64***

-

-2.52***

-

Breitung t-stat.

10.67

-3.39***

-2.15**

-

-0.59

-9.22***

7.20

-5.88***

6.16

-1.07

Harris-Tzavalis (rho)

0.963

-11.96***

-3.25***

-

-3.12***

-

1.46

-8.59***

2.34

-6.70***

Null Hypothesis: Unit root with individual process

IPS (W-stat.)

-1.98**

-

-1.184

-8.71***

-1.59**

-

-5.49***

-

-2.24***

-

ADF Fisher (Chi-square)

-0.278

1.75***

2.19**

-

0.057

4.64***

2.89***

-

4.48***

-

Remark

I(1)

I(0)

I(0)

I(0)

I(0)

Source: STATA output (2025)
Note: *** and ** denote statistical significance at 1% and 5% respectively
4.3. Panel Cointegration Test
The Pedroni cointegration test results for the model are presented in Table 6.
Table 6. Summary of Pedroni panel cointegration test results.

Series: LSI PEX OOP IOB IAN

H0: No cointegration

Number of panels

=

10

Ha: All panels are cointegrated

Number of periods

=

23

Cointegrating vector: Panel specific

Panel means:

Included

Kernel:

Bartlett

Time trend:

Not included

Lags:

1.00 (Newey–West)

AR parameter:

Panel specific

Augmented lags:

1

Statistic

p-value

Modified Phillips–Perron t

4.365***

0.0000

Phillips–Perron t

5.665***

0.0000

Augmented Dickey-Fuller t

6.286***

0.0000

Source: STATA output (2025)
Note: *** denotes statistical significance at 1% level
With evidence of mixed integration [I(0) and I(1)] series from the unit root test results, the panel cointegration test was conducted using the Pedroni method. The test results showed that all the test statistics are highly significant at the 1% level. Thus, the null hypothesis of no cointegration is rejected. This implies that a long-run relationship exists among the variables. This finding is impressive as it indicates that long-term changes in lifespan inequality can be predicted based on changes in the regressors.
4.4. Model Estimation
For the heterogeneous panels proposed for this study, MG and PMD estimators were applied to estimate the empirical model following the evidence of cointegration among the mixed integrated series. The results of the MG and PMG estimators are presented in Table 7.
Table 7. Summary of MG and PMG results.

Dependent variable: FDI

(1)

(2)

Variables

MG

PMG

Ec

-0.714***

-0.647***

(0.219)

(0.215)

D.PEX

-12.98***

-17.69

(8.47)

(21.72)

D.OOP

-41.09***

-57.16**

(11.81)

(23.19)

D.IOB

57.02

49.16***

(44.74)

(11.97)

D.IAN

68.31

61.41**

(59.06)

(23.47)

PEX

-63.46*

-45.04

(37.19)

(25.92)

OOP

-59.24**

-52.94***

(21.37)

(11.40)

IOP

52.15

39.68***

(46.6)

(8.17)

IAN

37.75***

43.42***

(14.84)

(13.07)

Constant

-9.02

1.081

(5.17)

(3.047)

Hausman test results

Chi2(4) = 11.09

Prob>chi2 = 0.1406

Observations

241

241

Source: STATA output (2025)
Note: *** p<0.01, ** p<0.05, * p<0.1 denote significant at 1%, 5% and l0% level respectively
The Hausman test result is reported in Table 7, and it shows that the probability value (0.1406) of the Chi-square statistic (11.09) is greater than 0.05, indicating that the PMG is the most efficient and preferred estimator. Consequently, PMG results form the basis for discussion. As observed from the PMG results, the error correction coefficient (-0.647) is negative and less than 1, indicating that distortions from the long-run equilibrium position can be corrected at 44.7% per annum. The short and long-run results showed that an increase in public health expenditure reduced lifespan inequality in women during the study period. This finding is not significant at the 5% level, indicating that public health expenditure has not provided the required opportunity for reducing the gap in the age of death among women. It also suggests that women's access to healthcare has not improved, regardless of changes in public health spending in each of the selected countries.
It is also evident in the results that out-of-pocket healthcare payments significantly reduced inequality in the length of life of women in both the short and long run; the impact is more pronounced in the long run. This corroborates the findings of , thus highlighting the efficacy of out-of-pocket healthcare payments in promoting uniformity in the ages of death of women in the ECOWAS region. The robustness of out-of-pocket healthcare payments in reducing lifespan inequality could be attributed to poor public health insurance systems and low government spending on healthcare in Africa, where most of the population, including women, pay directly for healthcare services when they need them.
In addition, the results showed that the incidence of obesity and anaemia significantly increased the gap in length of life as they are positively linked to lifespan inequality in women. However, the magnitude of impact differs, with the prevalence of anaemia worsening the inequality in lifespan among women in the selected countries. This finding is consistent with the results of , who reported that anaemia has remained a health risk among women, which could be linked to menstruation, pregnancy and childbirth among women.
5. Conclusion and Policy Insights
Mitigating inequality in the length of life of women is critical for overall improvement in health outcomes, thus creating opportunities for more uniform ages of death among them. To achieve this goal, many countries tend to leverage public expenditure-based policies, including national health insurance schemes. However, the widening gap in the ages of death of women has raised concern among policymakers about the effectiveness of this initiative. Thus, this study quantifies the implications of public health expenditure, out-of-pocket healthcare payments and maternal health status, including the prevalence of obesity and anaemia, on lifespan inequality among women in ten countries in the ECOWAS region. Findings showed that out-of-pocket healthcare payments largely reduced inequality in women’s length of life in the long run. This finding implies that boosting the purchasing power of women for more independent financial decisions will improve equality in their longevity. Again, targeted conditional cash transfers should be provided to vulnerable women to boost their out-of-pocket healthcare payments. Further analysis revealed that public health expenditure does not significantly reduce the disparity in lifespan in both the short and long run. This highlights the need for more effective public healthcare financing that will increase healthcare access and prioritise healthcare in reinvestments of the savings from subsidy removal, while addressing the issue of corruption. However, the findings showed that the prevalence of obesity and anaemia among women worsened the lifespan inequality during the study period. This explains the need for addressing underlying health conditions in women through healthy diets and regular physical exercise. Given the findings, this study concludes that out-of-pocket healthcare payment is a more effective funding source than public health expenditure for achieving uniformity in the lifespan of women.
Abbreviations

ECOWAS

Economic Community of West African States

WHO

World Health Organisation

GDP

Gross Domestic Product

MG

Mean Group

PMG

Pooled Mean Group

Author Contributions
Johnbosco Chukwuma Ozigbu: Conceptualization, writing of original draft and data curation
Christopher Ifeanyi Ezekwe: Methodology, formal analysis and conclusion/policy insights
Conflicts of Interest
The authors declare no conflicts of interest.
References
[1] Agyemang, C., Kushitor, S. B., Afrifa-Anane, G. F., & de-Graft Aikins, A. (2024). Obesity in Africa: A Silent Public Health Crisis. In Metabolic Syndrome: A Comprehensive Textbook (pp. 47-64). Cham: Springer International Publishing.
[2] Anwar, A., Hyder, S., Mohamed Nor, N., & Younis, M. (2023). Government health expenditures and health outcome nexus: a study on OECD countries. Frontiers in Public Health, 11, 1123759.
[3] Ayoya, M. A., Bendech, M. A., Zagré, N. M., & Tchibindat, F. (2012). Maternal anaemia in West and Central Africa: time for urgent action. Public health nutrition, 15(5), 916-927.
[4] Azam, M., Uddin, I., & Saqib, N. (2023). The determinants of life expectancy and environmental degradation in Pakistan: evidence from ARDL bounds test approach. Environmental Science and Pollution Research, 30(1), 2233-2246.
[5] Bansal, S., & Jin, Y. (2023). Heterogeneous effects of obesity on life expectancy: a global perspective. Annual Review of Resource Economics, 15(1), 433-554.
[6] Berger, M. C., & Messer, J. (2002). Public financing of health expenditures, insurance, and health outcomes. Applied Economics, 34(17), 2105-2113.
[7] Breitung, J. (2001). The local power of some unit root tests for panel data. In Nonstationary panels, panel cointegration, and dynamic panels (pp. 161-177). Emerald Group Publishing Limited.
[8] Bunyaminu, A., Mohammed, I., Yakubu, I. N., Shani, B., & Abukari, A. L. (2022). The effect of health expenditure on average life expectancy: does government effectiveness play a moderating role?. International Journal of Health Governance, 27(4), 365-377.
[9] Goodarzi, E, Beiranvand, R, Naemi H, Darvishi, I, & Khazaei Z. (2020). Prevalence of iron deficiency anaemia in Asian female population and human development index (HDI): An ecological study. Obstetrics & Gynecology Science, 63(4): 497-505.
[10] Guzel, A. E., Arslan, U., & Acaravci, A. (2021). The impact of economic, social, and political globalization and democracy on life expectancy in low-income countries: are sustainable development goals contradictory?. Environment, Development and Sustainability, 23(9), 13508-13525.
[11] Harris, R. D., & Tzavalis, E. (1999). Inference for unit roots in dynamic panels where the time dimension is fixed. Journal of econometrics, 91(2), 201-226.
[12] Hausman, J. A. (1978). Specification tests in econometrics. Econometrica: Journal of the econometric society, 1251-1271.
[13] Im, K. S., Pesaran, M. H., & Shin, Y. (2003). Testing for unit roots in heterogeneous panels. Journal of econometrics, 115(1), 53-74.
[14] Mawani, M., Ali, S. A., Bano, G., & Ali, S. A. (2016). Iron deficiency anemia among women of reproductive age, an important public health problem: situation analysis. Reproductive System & Sexual Disorders: Current Research., 5(3), 1.
[15] Mayhew, L., & Smith, D. (2021). An investigation into inequalities in adult lifespan. North American Actuarial Journal, 25(sup1), S545-S565.
[16] Millman, N., Koethe, J. R., & Erlandson, K. M. (2024). Obesity among women with HIV. Current Opinion in HIV and AIDS, 19(1), 30-34.
[17] Mulaga, A. N., Kamndaya, M. S., & Masangwi, S. J. (2021). Examining the incidence of catastrophic health expenditures and its determinants using multilevel logistic regression in Malawi. Plos one, 16(3), e0248752.
[18] Obrizan, M., & Wehby, G. L. (2018). Health expenditures and global inequalities in longevity. World Development, 101, 28-36.
[19] Onya, O. R., Uzoigwe, M. C., Ovat, E. O., Abane, O. P., & Osa, I. P. (2024). Public health expenditure, government effectiveness and labour productivity in West Africa. Nurture, 18(1), 55-72.
[20] Owais, A., Merritt, C., Lee, C., & Bhutta, Z. A. (2021). Anemia among women of reproductive age: an overview of global burden, trends, determinants, and drivers of progress in low-and middle-income countries. Nutrients, 13(8), 2745.
[21] Pedroni, P. (2007). Social capital, barriers to production and capital shares: implications for the importance of parameter heterogeneity from a nonstationary panel approach. Journal of Applied Econometrics, 22(2), 429-451.
[22] Pesaran, M. H., & Smith, R. P. (1995). Estimating long-run relationships from dynamic heterogeneous panels. Journal of Econometrics, 68(1), 79-113.
[23] Pesaran, M. H., Shin, Y., & Smith, R. P. (1999). Pooled mean group estimation of dynamic heterogeneous panels. Journal of the American statistical Association, 94(446), 621-634.
[24] Raghupathi, V., & Raghupathi, W. (2020). Healthcare expenditure and economic performance: insights from the United States data. Frontiers in public health, 8, 156.
[25] Rahman, M. M., Rana, R., & Khanam, R. (2022). Determinants of life expectancy in most polluted countries: Exploring the effect of environmental degradation. PloS one, 17(1), e0262802.
[26] Romer, P. M. (1994). The origins of endogenous growth. Journal of Economic perspectives, 8(1), 3-22.
[27] Shockley, T., & Burrell, D. N. (2024). Economic, Cultural, Social Determinants of Black Women Obesity. Business Ethics and Leadership, 8(1), 234-245.
[28] Sultana, S., Hossain, M. E., Khan, M. A., Saha, S. M., Amin, M. R., & Prodhan, M. M. H. (2024). Effects of healthcare spending on public health status: An empirical investigation from Bangladesh. Heliyon, 10(1).
[29] Teasdale, A. (2025). Voting For More?: Ageing and Health Spending. Age, 20(29), 40-49.
[30] Vaupel, J. W., Villavicencio, F., & Bergeron-Boucher, M. P. (2021). Demographic perspectives on the rise of longevity. Proceedings of the National Academy of Sciences, 118(9), e2019536118.
[31] WHO (World Health Organ.). 2021b. Obesity and overweight. Fact Sheet, World Health Organ., Geneva.
[32] World Bank (2025). Share of women of reproductive age who have anaemia. Available on: https://ourworldindata.org/grapher/prevalence-of-anemia-in-women-of-reproductive-age-aged-15-29?
[33] World Health Organization - Global Health Observatory (2024). Share of women who are overweight or obese. Available on:
[34] World Health Organization (2025). Public healthcare expenditure as a share of GDP. Available on:
[35] World Health Organization (2025). Share of out-of-pocket expenditure on healthcare. Available on:
Cite This Article
  • APA Style

    Ozigbu, J. C., Ezekwe, C. I. (2025). Rethinking the Dynamics of Healthcare Funding, Maternal Health Status and Lifespan Inequality Among Women in the ECOWAS Region. International Journal of Health Economics and Policy, 10(2), 67-76. https://doi.org/10.11648/j.hep.20251002.15

    Copy | Download

    ACS Style

    Ozigbu, J. C.; Ezekwe, C. I. Rethinking the Dynamics of Healthcare Funding, Maternal Health Status and Lifespan Inequality Among Women in the ECOWAS Region. Int. J. Health Econ. Policy 2025, 10(2), 67-76. doi: 10.11648/j.hep.20251002.15

    Copy | Download

    AMA Style

    Ozigbu JC, Ezekwe CI. Rethinking the Dynamics of Healthcare Funding, Maternal Health Status and Lifespan Inequality Among Women in the ECOWAS Region. Int J Health Econ Policy. 2025;10(2):67-76. doi: 10.11648/j.hep.20251002.15

    Copy | Download

  • @article{10.11648/j.hep.20251002.15,
      author = {Johnbosco Chukwuma Ozigbu and Christopher Ifeanyi Ezekwe},
      title = {Rethinking the Dynamics of Healthcare Funding, Maternal Health Status and Lifespan Inequality Among Women in the ECOWAS Region
    },
      journal = {International Journal of Health Economics and Policy},
      volume = {10},
      number = {2},
      pages = {67-76},
      doi = {10.11648/j.hep.20251002.15},
      url = {https://doi.org/10.11648/j.hep.20251002.15},
      eprint = {https://article.sciencepublishinggroup.com/pdf/10.11648.j.hep.20251002.15},
      abstract = {Motivated by the widening gap in lifespan within and between countries and across age groups, this study quantifies the implications of public health expenditure, out-of-pocket healthcare payments and maternal health conditions such as the prevalence of obesity and anaemia on lifespan inequality among women in five anglophone countries (Ghana, Liberia, Nigeria, Sierra Leone, and The Gambia) and five francophone countries (Senegal, Niger, Mali, Guinea and Togo) in the ECOWAS region. Heterogeneous panel estimation involving mean group (MG) and pooled mean group (PMG) estimators alongside unit root tests and descriptive statistics formed the basis for the analysis. Findings indicate that public health expenditure does not significantly reduce the disparity in lifespan in both the short and long run. This highlights the need for more effective public healthcare financing that will increase healthcare access and prioritise healthcare in reinvestments of the savings from subsidy removal, while mitigating corruption. Further analysis showed that out-of-pocket healthcare payments significantly reduced inequality in the length of life of women in both the short and long run. This highlights the efficacy of out-of-pocket healthcare payments in promoting uniformity in the ages of death of women. However, the findings showed that the prevalence of obesity and anaemia among women worsened the lifespan inequality during the study period. This explains the need to address underlying health conditions in women through healthy diets and regular physical exercise. Given the findings, this study recommends boosting the purchasing power of women for more independent financial decisions to improve equality in their longevity. Again, targeted conditional cash transfers should be provided to vulnerable women to boost their out-of-pocket healthcare payments for a more equal lifespan.
    },
     year = {2025}
    }
    

    Copy | Download

  • TY  - JOUR
    T1  - Rethinking the Dynamics of Healthcare Funding, Maternal Health Status and Lifespan Inequality Among Women in the ECOWAS Region
    
    AU  - Johnbosco Chukwuma Ozigbu
    AU  - Christopher Ifeanyi Ezekwe
    Y1  - 2025/06/12
    PY  - 2025
    N1  - https://doi.org/10.11648/j.hep.20251002.15
    DO  - 10.11648/j.hep.20251002.15
    T2  - International Journal of Health Economics and Policy
    JF  - International Journal of Health Economics and Policy
    JO  - International Journal of Health Economics and Policy
    SP  - 67
    EP  - 76
    PB  - Science Publishing Group
    SN  - 2578-9309
    UR  - https://doi.org/10.11648/j.hep.20251002.15
    AB  - Motivated by the widening gap in lifespan within and between countries and across age groups, this study quantifies the implications of public health expenditure, out-of-pocket healthcare payments and maternal health conditions such as the prevalence of obesity and anaemia on lifespan inequality among women in five anglophone countries (Ghana, Liberia, Nigeria, Sierra Leone, and The Gambia) and five francophone countries (Senegal, Niger, Mali, Guinea and Togo) in the ECOWAS region. Heterogeneous panel estimation involving mean group (MG) and pooled mean group (PMG) estimators alongside unit root tests and descriptive statistics formed the basis for the analysis. Findings indicate that public health expenditure does not significantly reduce the disparity in lifespan in both the short and long run. This highlights the need for more effective public healthcare financing that will increase healthcare access and prioritise healthcare in reinvestments of the savings from subsidy removal, while mitigating corruption. Further analysis showed that out-of-pocket healthcare payments significantly reduced inequality in the length of life of women in both the short and long run. This highlights the efficacy of out-of-pocket healthcare payments in promoting uniformity in the ages of death of women. However, the findings showed that the prevalence of obesity and anaemia among women worsened the lifespan inequality during the study period. This explains the need to address underlying health conditions in women through healthy diets and regular physical exercise. Given the findings, this study recommends boosting the purchasing power of women for more independent financial decisions to improve equality in their longevity. Again, targeted conditional cash transfers should be provided to vulnerable women to boost their out-of-pocket healthcare payments for a more equal lifespan.
    
    VL  - 10
    IS  - 2
    ER  - 

    Copy | Download

Author Information