
Wells syndrome, a rare eosinophilic cutaneous disorder, also called eosinophilic cellulitis, exhibits significant clinical heterogenicity. It typically presents as erythematous infiltrated plaques, primarily on the extremities. Initially, these lesions often exhibit similarities to erysipelas or cellulitis but do not respond to antimicrobial therapy. Contribution of IL-5, abnormal Th2 cells, and activated eosinophilic granulocytes suggests a nonspecific hypersensitivity reaction to exogenous or endogenous stimuli. Wells syndrome is a diagnosis of exclusion that can be recognised by its clinical course, and histological findings. Corticosteroids are the mainstay treatment, helps alleviate the ongoing, relapsing pattern. We are reporting a case of 50 years old male presented to us with complaint of itchy red raised lesions that has recurrent course. On physical examination, multiple erythematous plaques were identified over bilateral lower limb. Skin biopsy specimen was sent for histopathological examination which showed eosinophilic infiltration around peri-appendageal structures confirming the diagnosis of Wells syndrome. It is a rare, relapsing skin disorder of unknown cause which is difficult to diagnose specially on first episode. For mild cases, topical corticosteroids are often sufficient. However, in most of the cases, oral steroids show rapid resolution. Gradual reducing dosage of corticosteroids across a month is usually easily tolerated by the patients whereas low maintenance dose with corticosteroids helps in preventing recurrences.
| Published in | International Journal of Clinical Dermatology (Volume 8, Issue 1) |
| DOI | 10.11648/j.ijcd.20250801.14 |
| Page(s) | 22-25 |
| Creative Commons |
This is an Open Access article, distributed under the terms of the Creative Commons Attribution 4.0 International License (http://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, distribution and reproduction in any medium or format, provided the original work is properly cited. |
| Copyright |
Copyright © The Author(s), 2025. Published by Science Publishing Group |
Wells Syndrome, Eosinophilic Cellulitis, Flame Figures
IL | Interleukin |
Th2 | T helper 2 |
EC | Eosinophilic Cellulitis |
| [1] | Wells GC. Recurrent granulomatous dermatitis with eosinophilia. Trans St Johns Hosp Dermatol Soc 1971; 57: 46-6. PMID: 5570262. |
| [2] | Sinno H, Lacroix JP, Lee J, et al. Diagnosis and management of eosinophilic cellulitis (Wells' syndrome): A case series and literature review. Can J Plast Surg 2012; 20: 91-7. |
| [3] | Chan JK, Hui PK, Ng CS, et al. Epithelioid haemangioma (angiolymphoid hyperplasia with eosinophilia) and Kimura's disease in Chinese. Histopathology 1989; 15: 557-74. |
| [4] | Hui PK, Chan JK, Ng CS, et al. Lymphadenopathy of Kimura's disease. Am J Surg Pathol 1989; 13: 177-86. |
| [5] | Reichel M, Isseroff RR, Vogt PJ, Gandour-Edwards R. Wells' syndrome in children: varicella infection as a precipitating event. Br J Dermatol 1991; 124: 187-90. |
| [6] | Koh KJ, Warren L, Moore L, et al. Wells' syndrome following thiomersal-containing vaccinations. Australas J Dermatol 2003; 44: 199-202. |
| [7] | Nacaroglu HT, Celegen M, Karkıner CS, et al. Eosinophilic cellulitis (Wells' syndrome) caused by a temporary henna tattoo. Postepy Dermatol Alergol 2014; 31: 322-4. |
| [8] | Rothenberg ME, Hogan SP. The eosinophil. Annu Rev Immunol 2006; 24: 147-74. |
| [9] | Slifman NR, Loegering DA, McKean DJ, Gleich GJ. Ribonuclease activity associated with human eosinophil-derived neurotoxin and eosinophil cationic protein. J Immunol 1986; 137: 2913-7. |
| [10] | Peters MS, Schroeter AL, Gleich GJ. Immunofluorescence identification of eosinophil granule major basic protein in the flame figures of Wells' syndrome. Br J Dermatol 1983; 109: 141-8. |
| [11] | Aberer W, Konrad K, Wolff K. Wells' syndrome is a distinctive disease entity and not a histologic diagnosis. J Am Acad Dermatol 1988; 18: 105-14. |
| [12] | Heelan K, Ryan JF, Shear NH, Egan CA. Wells syndrome (eosinophilic cellulitis): Proposed diagnostic criteria and a literature review of the drug-induced variant. J Dermatol Case Rep 2013; 7: 113-20. |
| [13] | Caputo R, Marzano AV, Vezzoli P, Lunardon L. Wells syndrome in adults and children: a report of 19 cases. Arch Dermatol 2006; 142: 1157-61. |
| [14] | Anderson CR, Jenkins D, Tron V, Prendiville JS. Wells' syndrome in childhood: case report and review of the literature. J Am Acad Dermatol 1995; 33: 857-64. |
| [15] | Räßler F, Lukács J, Elsner P. Treatment of eosinophilic cellulitis (Wells syndrome) - a systematic review. J Eur Acad Dermatol Venereol 2016; 30: 1465-79. |
| [16] | Gandhi RK, Coloe J, Peters S, et al. Wells syndrome (eosinophilic cellulitis): a clinical imitator of bacterial cellulitis. J Clin Aesthet Dermatol 2011; 4: 55-7. PMID: 21779422. |
| [17] | Aroni K, Aivaliotis M, Liossi A, Davaris P. Eosinophilic cellulitis in a child successfully treated with cetirizine. Acta Derm Venereol 1999; 79: 332. |
| [18] | Marks R. Eosinophilic cellulitis--a response to treatment with dapsone: case report. Australas J Dermatol 1980; 21: 10-2. |
| [19] | Moossavi M, Mehregan DR. Wells' syndrome: a clinical and histopathologic review of seven cases. Int J Dermatol 2003; 42: 62-7. |
| [20] | Herr H, Koh JK. Eosinophilic cellulitis (Wells' syndrome) successfully treated with low-dose cyclosporine. J Korean Med Sci 2001; 16: 664-8. |
| [21] | Paquet P, Laso-Dosal F, de la Brassinne M. Wells' syndrome: report of 2 cases. Dermatology 1992; 184: 139-41. |
| [22] | Stam-Westerveld EB, Daenen S, Van der Meer JB, Jonkman MF. Eosinophilic cellulitis (Wells' syndrome): treatment with minocycline. Acta Derm Venereol 1998; 78: 157. |
| [23] | Diridl E, Hönigsmann H, Tanew A. Wells' syndrome responsive to PUVA therapy. Br J Dermatol 1997; 137: 479-81. |
| [24] | Terhorst-Molawi D, Altrichter S, Röwert J, et al. Effective treatment with mepolizumab in a patient with refractory Wells syndrome. J Dtsch Dermatol Ges 2020; 18: 737-9. |
| [25] | Coattrenec Y, Ibrahim Yasmine L, Harr T, et al. Long-term Remission of Wells Syndrome with Omalizumab. J Investig Allergol Clin Immunol 2020; 30: 58-9. |
| [26] | Traidl S, Angela Y, Kapp A, et al. Dupilumab in eosinophilic cellulitis (Wells' syndrome) - case report of a potential new treatment option. J Dtsch Dermatol Ges 2021; 19: 1653-5. |
APA Style
Sharma, T., Vishwakarma, A. K. (2025). Wells Syndrome: A Rare Recurrent Eosinophilic Dermatosis in a Tertiary Care Hospital. International Journal of Clinical Dermatology, 8(1), 22-25. https://doi.org/10.11648/j.ijcd.20250801.14
ACS Style
Sharma, T.; Vishwakarma, A. K. Wells Syndrome: A Rare Recurrent Eosinophilic Dermatosis in a Tertiary Care Hospital. Int. J. Clin. Dermatol. 2025, 8(1), 22-25. doi: 10.11648/j.ijcd.20250801.14
AMA Style
Sharma T, Vishwakarma AK. Wells Syndrome: A Rare Recurrent Eosinophilic Dermatosis in a Tertiary Care Hospital. Int J Clin Dermatol. 2025;8(1):22-25. doi: 10.11648/j.ijcd.20250801.14
@article{10.11648/j.ijcd.20250801.14,
  author = {Tripti Sharma and Ajay Kumar Vishwakarma},
  title = {Wells Syndrome: A Rare Recurrent Eosinophilic Dermatosis in a Tertiary Care Hospital
},
  journal = {International Journal of Clinical Dermatology},
  volume = {8},
  number = {1},
  pages = {22-25},
  doi = {10.11648/j.ijcd.20250801.14},
  url = {https://doi.org/10.11648/j.ijcd.20250801.14},
  eprint = {https://article.sciencepublishinggroup.com/pdf/10.11648.j.ijcd.20250801.14},
  abstract = {Wells syndrome, a rare eosinophilic cutaneous disorder, also called eosinophilic cellulitis, exhibits significant clinical heterogenicity. It typically presents as erythematous infiltrated plaques, primarily on the extremities. Initially, these lesions often exhibit similarities to erysipelas or cellulitis but do not respond to antimicrobial therapy. Contribution of IL-5, abnormal Th2 cells, and activated eosinophilic granulocytes suggests a nonspecific hypersensitivity reaction to exogenous or endogenous stimuli. Wells syndrome is a diagnosis of exclusion that can be recognised by its clinical course, and histological findings. Corticosteroids are the mainstay treatment, helps alleviate the ongoing, relapsing pattern. We are reporting a case of 50 years old male presented to us with complaint of itchy red raised lesions that has recurrent course. On physical examination, multiple erythematous plaques were identified over bilateral lower limb. Skin biopsy specimen was sent for histopathological examination which showed eosinophilic infiltration around peri-appendageal structures confirming the diagnosis of Wells syndrome. It is a rare, relapsing skin disorder of unknown cause which is difficult to diagnose specially on first episode. For mild cases, topical corticosteroids are often sufficient. However, in most of the cases, oral steroids show rapid resolution. Gradual reducing dosage of corticosteroids across a month is usually easily tolerated by the patients whereas low maintenance dose with corticosteroids helps in preventing recurrences.
},
 year = {2025}
}
TY  - JOUR
T1  - Wells Syndrome: A Rare Recurrent Eosinophilic Dermatosis in a Tertiary Care Hospital

AU  - Tripti Sharma
AU  - Ajay Kumar Vishwakarma
Y1  - 2025/04/29
PY  - 2025
N1  - https://doi.org/10.11648/j.ijcd.20250801.14
DO  - 10.11648/j.ijcd.20250801.14
T2  - International Journal of Clinical Dermatology
JF  - International Journal of Clinical Dermatology
JO  - International Journal of Clinical Dermatology
SP  - 22
EP  - 25
PB  - Science Publishing Group
SN  - 2995-1305
UR  - https://doi.org/10.11648/j.ijcd.20250801.14
AB  - Wells syndrome, a rare eosinophilic cutaneous disorder, also called eosinophilic cellulitis, exhibits significant clinical heterogenicity. It typically presents as erythematous infiltrated plaques, primarily on the extremities. Initially, these lesions often exhibit similarities to erysipelas or cellulitis but do not respond to antimicrobial therapy. Contribution of IL-5, abnormal Th2 cells, and activated eosinophilic granulocytes suggests a nonspecific hypersensitivity reaction to exogenous or endogenous stimuli. Wells syndrome is a diagnosis of exclusion that can be recognised by its clinical course, and histological findings. Corticosteroids are the mainstay treatment, helps alleviate the ongoing, relapsing pattern. We are reporting a case of 50 years old male presented to us with complaint of itchy red raised lesions that has recurrent course. On physical examination, multiple erythematous plaques were identified over bilateral lower limb. Skin biopsy specimen was sent for histopathological examination which showed eosinophilic infiltration around peri-appendageal structures confirming the diagnosis of Wells syndrome. It is a rare, relapsing skin disorder of unknown cause which is difficult to diagnose specially on first episode. For mild cases, topical corticosteroids are often sufficient. However, in most of the cases, oral steroids show rapid resolution. Gradual reducing dosage of corticosteroids across a month is usually easily tolerated by the patients whereas low maintenance dose with corticosteroids helps in preventing recurrences.

VL  - 8
IS  - 1
ER  -
Department of Pathology, Military Hospital, Panagarh, India
Department of Dermatology, Venereology & Leprosy, Government Medical College, Haldwani, India

Figure 1. Multiple erythematous, oedematous plaques involving lower limb with hyperpigmentation on resolving area.
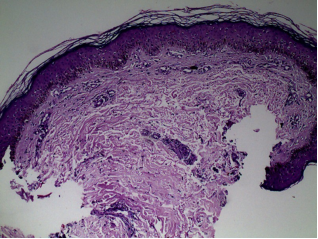
Figure 2. H&E, x40 Histopathological examination revealed a moderately dense superficial and deep perivascular, as well as peri-appendageal, infiltrate composed of eosinophils and lymphocytes. Additionally, several eosinophils were interspersed throughout the interstitium of reticular dermis and surrounding the deep vascular plexus.

Information



 Share This Article
 Twitter
 Linked In
 Facebook

 Copy
 Download