
 ,
Nahom Wondwossen,
Selamawit Sete,
Habtamu Seife,
Mahlet Shewangizaw,
Edilawit Abebaw Abera,
Yehenaw Tadele Tenaw,
Biruk Habtamu,
Nahom Girma Belete*
Background: Breast cancer is the leading cause of cancer-related morbidity and mortality among women globally, with disproportionate impacts in low-resource settings due to delayed diagnosis and limited access to screening. In Ethiopia, breast cancer accounts for over 30% of all female cancers, yet early detection remains critically underutilized. Harar Town, located in Eastern Ethiopia, presents unique challenges and opportunities for community-based interventions. This study aimed to strategically advance breast cancer prevention through a market-centered screening and awareness initiative targeting women in Shewa-Ber, the largest public market in Harar. Materials and Methods: A cross-sectional, community-based screening program was conducted on October 28–29, 2023. Women aged 16 years and above who visited Shewa-Ber market were recruited using convenience sampling. A total of 204 women underwent clinical breast examinations performed by trained healthcare professionals, and 166 completed structured interviews. The survey instrument captured socio-demographic data, reproductive history, substance use, breast health complaints, and knowledge and practice of self-breast examination (SBE). Ethical clearance was obtained, and referrals were provided for suspected cases. Results: Among the 166 respondents, only 43.4% had prior knowledge of SBE, and 23.5% reported practicing it. Notably, 13.3% of screened women exhibited clinical signs suggestive of breast cancer and were referred for further diagnostic evaluation. Risk factors included early menarche (≤13 years), family history of breast cancer (4.2%), contraceptive use (41%), and substance exposure (chat: 24.7%, alcohol: 5.4%, tobacco: 1.8%). Educational attainment was low, with 25.3% of participants having no formal education. Despite 26.5% reporting breast-related symptoms, only one woman had previously accessed ultrasound screening. The intervention revealed significant gaps in awareness, screening access, and health-seeking behavior. Conclusion: This initiative demonstrated the 1581350 feasibility and effectiveness of decentralized, community-based breast cancer screening in a high-traffic public setting. The findings underscore the urgent need for integrated public health strategies that combine education, screening, and referral systems to improve early detection and reduce mortality in underserved populations. Recommendations: We recommend scaling this model across similar urban and peri-urban markets in Ethiopia. Health authorities should prioritize training of frontline health workers in breast cancer awareness, embed SBE education into routine outreach, and establish referral linkages for diagnostic follow-up. Future studies should assess longitudinal outcomes, cost-effectiveness, and integration with national cancer control programs.
| Published in | International Journal of Clinical Oncology and Cancer Research (Volume 10, Issue 4) |
| DOI | 10.11648/j.ijcocr.20251004.12 |
| Page(s) | 135-143 |
| Creative Commons |
This is an Open Access article, distributed under the terms of the Creative Commons Attribution 4.0 International License (http://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, distribution and reproduction in any medium or format, provided the original work is properly cited. |
| Copyright |
Copyright © The Author(s), 2025. Published by Science Publishing Group |
Breast Cancer Screening, Community Health Intervention, Self-Breast Examination (SBE), Early Detection Strategies, Harar, Ethiopia
Educational Status | Count |
|---|---|
No Education | 42 |
Primary Education | 44 |
Parity | Count |
|---|---|
At least 1 child | 36 |
Up to 5 children | 27 |
Contraceptive Use | Count |
|---|---|
Pills/Implanon | 27 |
Injectables | 13 |
SBE Awareness | Count |
|---|---|
Heard Before | 73 |
Learned During Screening | 94 |
Screening Methods | Count |
|---|---|
SBE | 25 |
Clinical Exam | 13 |
Ultrasound | 1 |
BC | Breast Cancer |
CBE | Clinical Breast Examination |
IRB | Institutional Review Board |
CHAI | Clinton Health Access Initiative |
LMICs | Lower and Middle-Income Countries |
WMA | World Medical Association |
NGOs | Non-Governmental Organisations |
SBE | Self Breast Examination |
WHO | World Health Organisation |
| [1] | Bray F, Ferlay J, Soerjomataram I, Siegel RL, Torre LA, Jemal A. Global cancer statistics 2018: GLOBOCAN estimates of incidence and mortality worldwide for 36 cancers in 185 countries. CA Cancer J Clin (2018) 68: 394–424. |
| [2] | Awedew AF, Asefa Z, Belay WB. National Burden and Trend of Cancer in Ethiopia, 2010–2019: a systemic analysis for Global burden of disease study. Sci Rep (2022) 12: 12736. https://doi.org/10.1038/s41598-022-17128-9 |
| [3] |
Clinton Health Access Initiative (CHAI). Over 21,000 Women Screened for Breast Cancer in Ethiopia Thanks to Decentralized Services. 2023. Available from:
https://www.clintonhealthaccess.org/case-study/over-21000-women-screened-for-breast-cancer-in-ethiopia-thanks-to-decentralized-services/ (Accessed November 2, 2025). |
| [4] | Federal Ministry of Health of Ethiopia. National Guideline for Breast Health, Early Diagnosis and Timely Breast Cancer Management in Ethiopia (2024–2028). 2024. |
| [5] | Colditz GA. Cumulative Risk of Breast Cancer to Age 70 Years According to Risk Factor Status: Data from the Nurses’ Health Study. Am J Epidemiol (2000) 152: 950–964. |
| [6] |
U.S. Department of Health & Human Services. Informed Consent FAQs. (2023)
https://www.hhs.gov/ohrp/regulations-and-policy/guidance/faq/informed-consent/index.html |
| [7] | Southern Illinois University Carbondale Institutional Review Board. Oral (Verbal) Consent Guidance. (2025) https://research.siu.edu/compliance/human-subjects/ |
| [8] | World Medical Association. Declaration of Helsinki. 2024. Available from: https://www.wma.net/what-we-do/medical-ethics/declaration-of-helsinki/ (Accessed November 2, 2025). |
| [9] |
Exempt Research Determination FAQs | HHS.gov. (2018)
https://www.hhs.gov/ohrp/regulations-and-policy/guidance/faq/exempt-research-determination/index.html (Accessed November 2, 2025). |
| [10] | Federal Ministry of Health of Ethiopia. National Guideline for Breast Health, Early Diagnosis and Timely Breast Cancer Management in Ethiopia (2024–2028). (2024). |
| [11] | Abeje S, Seme A, Tibelt A. Factors associated with breast cancer screening awareness and practices of women in Addis Ababa, Ethiopia. BMC Womens Health (2019) 19: 4. |
| [12] | Aliyi M, Hotessa Y, Haro A, Beyene BN, Desalegn M, Debela DE. Breast self-examination practice and associated factors among pastoralist women in the West Guji Zone, Oromia, Ethiopia: a community-based cross-sectional study. Front Glob Womens Health (2025) 6: 1501001. |
| [13] | Bekele K, Nugusu F, Beressa G, Hollis T, Ferreres A, Duguma D, Guta B, Gutnik L, Lemesse B, Gezahegn H. Proportion of early-stage breast cancer at diagnosis in Ethiopia: a systematic review and meta-analysis. BMC Cancer (2024) 24: 1017. |
| [14] | Agide FD, Garmaroudi G, Sadeghi R, Shakibazadeh E, Yaseri M, Birhanu Z. Designing and evaluation of the effect of community-based intervention on breast self-examination among reproductive-aged women in Ethiopia: A Cluster Randomized Controlled Trial. PLOS One (2025) 20: e0329839. |
| [15] | Hailegebireal AH, Bizuayehu HM, Wolde BB, Tirore LL, Woldegeorgis BZ, Kassie GA, Asgedom YS. The prevalence and predictors of clinical breast cancer screening in Sub-Saharan African countries: a multilevel analysis of Demographic Health Survey. Front Public Health (2024) 12: 1409054. https://doi.org/10.3389/fpubh.2024.1409054 |
| [16] | Baidoo K. MYO Global marks Breast Cancer Awareness Month with Bu O’ Forfor Screening at Dodowa Market. Happy Ghana (2025) https://www.happyghana.com/myo-global-marks-breast-cancer-awareness-month-with-bu-o-forfor-screening-at-dodowa-market/ (Accessed January 1, 2025). |
| [17] |
Sarene Kloren. Bridging the gap: How mobile breast-cancer screening is saving lives in SA. IOL (2025)
https://iol.co.za/lifestyle/health/2025-10-30-bridging-the-gap-how-mobile-breast-cancer-screening-is-saving-lives-in-sa/ (Accessed January 1, 2025). |
| [18] | Geremew H, Golla EB, Simegn MB, Abate A, Ali MA, Kumbi H, Wondie SG, Mengstie MA, Tilahun WM. Late-stage diagnosis: The driving force behind high breast cancer mortality in Ethiopia: A systematic review and meta-analysis. PLOS ONE (2024) 19: e0307283. https://doi.org/10.1371/journal.pone.0307283 |
| [19] |
Implementation of the Global Breast Cancer Initiative (GBCI) Framework - Global Health Progress. Glob Health Prog (2025)
https://globalhealthprogress.org/collaboration/implementation-of-the-global-breast-cancer-initiative-gbci-framework/ (Accessed January 1, 2025). |
APA Style
Lemma, M. S., Wondwossen, N., Sete, S., Seife, H., Shewangizaw, M., et al. (2025). Enhancing Early Detection of Breast Cancer Through Community-Based Screening and Awareness in Harar Town, Eastern Ethiopia. International Journal of Clinical Oncology and Cancer Research, 10(4), 135-143. https://doi.org/10.11648/j.ijcocr.20251004.12
ACS Style
Lemma, M. S.; Wondwossen, N.; Sete, S.; Seife, H.; Shewangizaw, M., et al. Enhancing Early Detection of Breast Cancer Through Community-Based Screening and Awareness in Harar Town, Eastern Ethiopia. Int. J. Clin. Oncol. Cancer Res. 2025, 10(4), 135-143. doi: 10.11648/j.ijcocr.20251004.12
AMA Style
Lemma MS, Wondwossen N, Sete S, Seife H, Shewangizaw M, et al. Enhancing Early Detection of Breast Cancer Through Community-Based Screening and Awareness in Harar Town, Eastern Ethiopia. Int J Clin Oncol Cancer Res. 2025;10(4):135-143. doi: 10.11648/j.ijcocr.20251004.12
@article{10.11648/j.ijcocr.20251004.12,
  author = {Michael Shawel Lemma and Nahom Wondwossen and Selamawit Sete and Habtamu Seife and Mahlet Shewangizaw and Edilawit Abebaw Abera and Yehenaw Tadele Tenaw and Biruk Habtamu and Nahom Girma Belete},
  title = {Enhancing Early Detection of Breast Cancer Through Community-Based Screening and Awareness in Harar Town, Eastern Ethiopia},
  journal = {International Journal of Clinical Oncology and Cancer Research},
  volume = {10},
  number = {4},
  pages = {135-143},
  doi = {10.11648/j.ijcocr.20251004.12},
  url = {https://doi.org/10.11648/j.ijcocr.20251004.12},
  eprint = {https://article.sciencepublishinggroup.com/pdf/10.11648.j.ijcocr.20251004.12},
  abstract = {Background: Breast cancer is the leading cause of cancer-related morbidity and mortality among women globally, with disproportionate impacts in low-resource settings due to delayed diagnosis and limited access to screening. In Ethiopia, breast cancer accounts for over 30% of all female cancers, yet early detection remains critically underutilized. Harar Town, located in Eastern Ethiopia, presents unique challenges and opportunities for community-based interventions. This study aimed to strategically advance breast cancer prevention through a market-centered screening and awareness initiative targeting women in Shewa-Ber, the largest public market in Harar. Materials and Methods: A cross-sectional, community-based screening program was conducted on October 28–29, 2023. Women aged 16 years and above who visited Shewa-Ber market were recruited using convenience sampling. A total of 204 women underwent clinical breast examinations performed by trained healthcare professionals, and 166 completed structured interviews. The survey instrument captured socio-demographic data, reproductive history, substance use, breast health complaints, and knowledge and practice of self-breast examination (SBE). Ethical clearance was obtained, and referrals were provided for suspected cases. Results: Among the 166 respondents, only 43.4% had prior knowledge of SBE, and 23.5% reported practicing it. Notably, 13.3% of screened women exhibited clinical signs suggestive of breast cancer and were referred for further diagnostic evaluation. Risk factors included early menarche (≤13 years), family history of breast cancer (4.2%), contraceptive use (41%), and substance exposure (chat: 24.7%, alcohol: 5.4%, tobacco: 1.8%). Educational attainment was low, with 25.3% of participants having no formal education. Despite 26.5% reporting breast-related symptoms, only one woman had previously accessed ultrasound screening. The intervention revealed significant gaps in awareness, screening access, and health-seeking behavior. Conclusion: This initiative demonstrated the 1581350 feasibility and effectiveness of decentralized, community-based breast cancer screening in a high-traffic public setting. The findings underscore the urgent need for integrated public health strategies that combine education, screening, and referral systems to improve early detection and reduce mortality in underserved populations. Recommendations: We recommend scaling this model across similar urban and peri-urban markets in Ethiopia. Health authorities should prioritize training of frontline health workers in breast cancer awareness, embed SBE education into routine outreach, and establish referral linkages for diagnostic follow-up. Future studies should assess longitudinal outcomes, cost-effectiveness, and integration with national cancer control programs.},
 year = {2025}
}
TY  - JOUR
T1  - Enhancing Early Detection of Breast Cancer Through Community-Based Screening and Awareness in Harar Town, Eastern Ethiopia
AU  - Michael Shawel Lemma
AU  - Nahom Wondwossen
AU  - Selamawit Sete
AU  - Habtamu Seife
AU  - Mahlet Shewangizaw
AU  - Edilawit Abebaw Abera
AU  - Yehenaw Tadele Tenaw
AU  - Biruk Habtamu
AU  - Nahom Girma Belete
Y1  - 2025/12/09
PY  - 2025
N1  - https://doi.org/10.11648/j.ijcocr.20251004.12
DO  - 10.11648/j.ijcocr.20251004.12
T2  - International Journal of Clinical Oncology and Cancer Research
JF  - International Journal of Clinical Oncology and Cancer Research
JO  - International Journal of Clinical Oncology and Cancer Research
SP  - 135
EP  - 143
PB  - Science Publishing Group
SN  - 2578-9511
UR  - https://doi.org/10.11648/j.ijcocr.20251004.12
AB  - Background: Breast cancer is the leading cause of cancer-related morbidity and mortality among women globally, with disproportionate impacts in low-resource settings due to delayed diagnosis and limited access to screening. In Ethiopia, breast cancer accounts for over 30% of all female cancers, yet early detection remains critically underutilized. Harar Town, located in Eastern Ethiopia, presents unique challenges and opportunities for community-based interventions. This study aimed to strategically advance breast cancer prevention through a market-centered screening and awareness initiative targeting women in Shewa-Ber, the largest public market in Harar. Materials and Methods: A cross-sectional, community-based screening program was conducted on October 28–29, 2023. Women aged 16 years and above who visited Shewa-Ber market were recruited using convenience sampling. A total of 204 women underwent clinical breast examinations performed by trained healthcare professionals, and 166 completed structured interviews. The survey instrument captured socio-demographic data, reproductive history, substance use, breast health complaints, and knowledge and practice of self-breast examination (SBE). Ethical clearance was obtained, and referrals were provided for suspected cases. Results: Among the 166 respondents, only 43.4% had prior knowledge of SBE, and 23.5% reported practicing it. Notably, 13.3% of screened women exhibited clinical signs suggestive of breast cancer and were referred for further diagnostic evaluation. Risk factors included early menarche (≤13 years), family history of breast cancer (4.2%), contraceptive use (41%), and substance exposure (chat: 24.7%, alcohol: 5.4%, tobacco: 1.8%). Educational attainment was low, with 25.3% of participants having no formal education. Despite 26.5% reporting breast-related symptoms, only one woman had previously accessed ultrasound screening. The intervention revealed significant gaps in awareness, screening access, and health-seeking behavior. Conclusion: This initiative demonstrated the 1581350 feasibility and effectiveness of decentralized, community-based breast cancer screening in a high-traffic public setting. The findings underscore the urgent need for integrated public health strategies that combine education, screening, and referral systems to improve early detection and reduce mortality in underserved populations. Recommendations: We recommend scaling this model across similar urban and peri-urban markets in Ethiopia. Health authorities should prioritize training of frontline health workers in breast cancer awareness, embed SBE education into routine outreach, and establish referral linkages for diagnostic follow-up. Future studies should assess longitudinal outcomes, cost-effectiveness, and integration with national cancer control programs.
VL  - 10
IS  - 4
ER  -
Department of Oncology, Hiwot Fana Specialized University Hospital, Harar, Ethiopia
Research Fields: Breast cancer management, Cervical cancer treatment, Clinical oncology, Cancer prevention strategies, Chemotherapy protocols, Oncology patient care.
Department of Oncology, Hiwot Fana Specialized University Hospital, Harar, Ethiopia
Research Fields: Solid tumor oncology, Radiation oncology, Clinical oncology, Cancer treatment planning, Tumor biology, Oncology therapeutics.
Department of Dermatology, Hiwot Fana Specialized University Hospital, Harar, Ethiopia
Research Fields: Dermatology, Skin cancer screening, Clinical dermatology, Dermatologic oncology, Patient education in dermatology.
Department of Oncology, Hiwot Fana Specialized University Hospital, Harar, Ethiopia
Research Fields: Clinical oncology, Cancer screening programs, Oncology data analysis, Tumor registry management, Cancer epidemiology.
Department of Oncology, Hiwot Fana Specialized University Hospital, Harar, Ethiopia
Research Fields: Dermatology, Skin cancer prevention, Dermatologic surgery, Community dermatology outreach, Clinical dermatology research.
Department of Dermatology, Hiwot Fana Specialized University Hospital, Harar, Ethiopia
Research Fields: Dermatology, Skin cancer awareness, Dermatologic oncology, Preventive dermatology, Patient counseling.
Department of Oncology, Hiwot Fana Specialized University Hospital, Harar, Ethiopia
Research Fields: Clinical oncology, Cancer screening implementation, Oncology program management, Tumor staging, Cancer care coordination.
Department of Oncology, Hiwot Fana Specialized University Hospital, Harar, Ethiopia
Research Fields: Cancer epidemiology, Radiation oncology, Oncology data visualization, Cancer survival analysis, Public health oncology.
Department of Oncology, Hiwot Fana Specialized University Hospital, Harar, Ethiopia
Biography: Nahom Girma Belete holds a Bachelor of Science in Nursing and a Master of Public Health in Nutrition from Haramaya University, Ethiopia. He has over five years of experience in public health research, having contributed to and co-authored several published studies addressing nutrition, oral health, and aging populations. His work demonstrates a strong commitment to improving evidence-based interventions and advancing health outcomes in underserved communities. His current research interests center on oncology, healthcare access and equity, nutrition, and global health. He is particularly passionate about exploring the intersection of health economics and policy to promote sustainable and equitable healthcare systems. Nahom currently serves as the Research and Program Coordinator at the October Cancer Support Association in Harar, Ethiopia.
Research Fields: Public health, Cancer epidemiology, Community-based screening, Health systems strengthening, Global health policy, Implementation science.
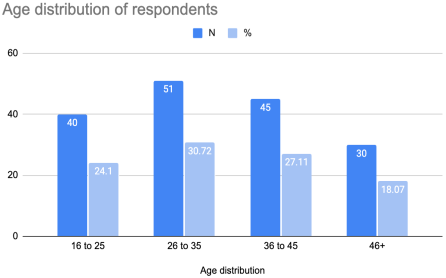
Figure 1. Adjusted Age Distribution of Participants (N = 166) in Harar Town, Eastern Ethiopia.
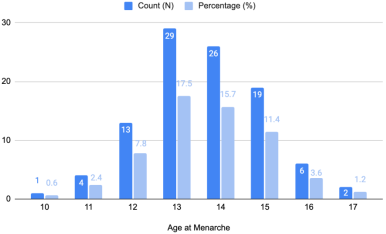
Figure 2. Distribution of Age at First Menarche Among Participants (N = 166) in Harar Town, Eastern Ethiopia.
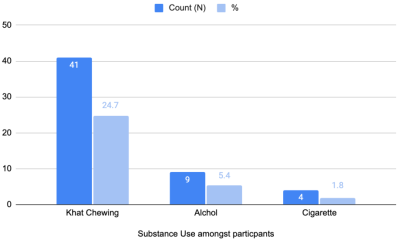
Figure 3. Substance Use Among Participants Screened in Harar Town, Eastern Ethiopia.
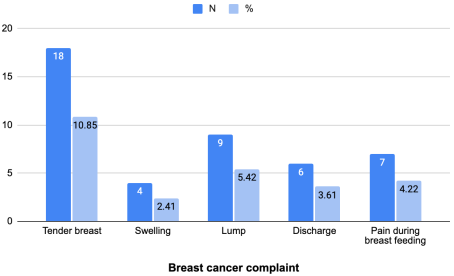
Figure 4. Complaint before Community Breast Cancer Screening Among Participants in Harar Town, Eastern Ethiopia.
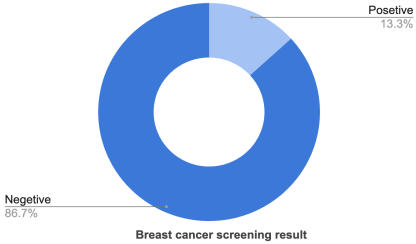
Figure 5. Breast Cancer Screening Outcomes (Positive vs. Negative) Among Participants in Harar Town, Eastern Ethiopia.

Information


 Share This Article
 Twitter
 Linked In
 Facebook

 Copy
 Download