Research Article | | Peer-Reviewed

Healthcare Access Patterns and Challenges Among the Elderly in Edo State, Nigeria: A Cross-sectional Mixed-methods Study

Received: 19 December 2025     Accepted: 31 December 2025     Published: 11 February 2026
Views:       Downloads:
Abstract

The global increase in life expectancy has increased among the elderly population, creating challenges for healthcare systems in developing countries like Nigeria. In Edo State, accessing healthcare services among elderly population remains limited. Understanding healthcare access patterns and challenges among the elderly is crucial for developing targeted interventions that promote healthy ageing in line with the United Nations Decade of Healthy Ageing (2021–2030). To determine elderly access to healthcare services, a cross-sectional, mixed-methods study sampled elderly individuals of the ages of 60 years and above across primary, secondary, and tertiary healthcare facilities in Edo State using multistage cluster sampling. Quantitative data were extracted from outpatient registers, capturing demographics, complaints, diagnoses, and outcomes. Qualitative interviews with healthcare workers provided additional insights. Data analysis included descriptive statistics, correlation tests, and thematic analysis. The data showed that elderly patients constituted 9.82% of outpatient visits, mostly female (52%) with an average age of 70 years. Tertiary (42%) and secondary facilities (40%) were preferred over primary healthcare centres-PHC (19%). Common complaints included body pain, weakness, and malaria-related symptoms, with a moderate positive correlation between number of complaints and diagnoses (r = 0.353, p < 0.01). Barriers identified qualitatively included limited geriatric services, poor data disaggregation, rural access challenges and lack of infrastructure at the PHC. Further findings revealed gender and age disparities in elderly healthcare utilization, preference for higher-tier facilities, and systemic barriers limiting care at primary levels. Strengthening age-sensitive healthcare systems, improving data practices, establish geriatric units, training more healthcare workers on elderly care, age-disaggregated data systems, strengthening rural primary healthcare, expanding subsidized health insurance for the elderly, and implementing mobile clinics and transportation support for the elderly. These are needed to address elderly healthcare needs in Edo State, Nigeria.

Published in International Journal of Gerontology and Geriatrics (Volume 1, Issue 1)
DOI 10.11648/j.ijgege.20260101.11
Page(s) 1-11
Creative Commons

This is an Open Access article, distributed under the terms of the Creative Commons Attribution 4.0 International License (http://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, distribution and reproduction in any medium or format, provided the original work is properly cited.

Copyright

Copyright © The Author(s), 2026. Published by Science Publishing Group

Previous article
Keywords

Edo State, Elderly Care Access, Healthy Ageing, Geriatrics Services, Primary Healthcare Barrier

1. Introduction
The global demographic landscape is undergoing a profound transformation, marked by a significant increase in life expectancy. People worldwide are experiencing longer lifespans, leading to a notable rise in both the absolute number and the proportion of older individuals within populations . According to projections, by 2030, approximately 1 in 6 people globally will be aged 60 years or older, and this trend is expected to escalate further, with the population of people aged 60 years and older doubling to 2.1 billion by 2050 .
Nigeria's population stands at approximately 206 million (United Nations, 2022). As of 2020, about 9.4 million individuals were aged 60 years and above, with women constituting 46% of this demographic, representing approximately 4.3 million people. The phenomenon of population ageing, once predominant in high-income countries, is now a growing trend in low- and middle-income nations, including Nigeria .
Ageing is biologically characterized by the gradual accumulation of molecular and cellular damage, leading to a decline in physical and mental capabilities. In addition to biological processes, the experience of ageing is shaped by life transitions such as retirement, changes in housing, and the loss of social connections . Consequently, older adults are at an increased risk for a variety of health conditions, ranging from chronic diseases like hypertension and diabetes to geriatric syndromes such as frailty, falls, and cognitive decline.
In the context of Edo State, Nigeria, understanding the healthcare access patterns among elderly individuals is critical. Although the state follows the global ageing trend, there is a notable lack of disaggregated data beyond the age of 20 in health records. This data limitation, particularly in platforms like the District Health Information Software 2 (DHIS2), hampers the development of tailored interventions for the elderly population.
As the world enters the United Nations Decade of Healthy Ageing (2021–2030), which emphasizes action to improve the lives of older people , localized studies are vital. These studies not only help understand regional ageing trends but also support policies that counteract ageist attitudes and promote healthy ageing. Therefore, this study seeks to explore the proportion of elderly patients accessing healthcare services in Edo State, addressing the gap by focusing on the healthcare-seeking patterns of elderly patients in Edo State, particularly in outpatient departments, identifying patterns and challenges to inform policy and improve healthcare delivery.
2. Methodology
Prior to this study, ethical approval was obtained from the Ministry of Health, Edo State, Nigeria. A cross-sectional research design was employed to collect data at a single point in time. This design enabled the investigation of healthcare utilization patterns among elderly individuals, providing a snapshot of the current state of healthcare access.
2.1. Population and Sample
The target population comprised elderly individuals aged 60 years and above residing in Edo State, Nigeria. A multistage cluster sampling technique was adopted to ensure a representative sample across the state's three senatorial districts—Edo North, Edo Central, and Edo South, covering different the three tiers of healthcare facilities (tertiary, secondary and primary healthcare facilities).
2.2. Sampling Technique
Within each senatorial district, three Local Government Areas (LGAs) were randomly selected. Subsequently, primary, secondary private, and secondary public healthcare facilities within these LGAs were randomly sampled. The sampling frame represented approximately 5% of facilities within each district.
Facility Selection and Sample Size
Primary Facilities
1. Edo North: 6
2. Edo Central: 3
3. Edo South: 6
Secondary Private Facilities
1. Edo North: 3
2. Edo Central: 3
3. Edo South: 12
Secondary Public Facilities
1. Edo North: 1
2. Edo Central: 1
3. Edo South: 1
Tertiary Health Facilities
1. Five tertiary health facilities across the State were purposively selected.
2.3. Data Collection
A mixed-method approach was used, incorporating both quantitative and qualitative techniques to obtain a comprehensive understanding of healthcare utilization by the elderly.
2.3.1. Quantitative Data
Data were extracted from the Outpatient Department (OPD) registers using a structured template. The template captured information on:
1) Case note number
2) Sex
3) Age
4) Patient complaints
5) Diagnosis
6) Outcome
2.3.2. Qualitative Data
Open-ended questions were administered to healthcare workers to understand their perspectives on elderly healthcare access. Responses were subjected to thematic analysis, enabling the identification of recurring themes .
2.4. Data Analysis
Both descriptive and inferential statistical techniques were used to analyze the data collected. Descriptive statistics such as frequencies and percentages were computed to summarize demographic characteristics, common health complaints, and utilization patterns while Inferential statistical methods were applied to explore relationships between variables.
All tests were conducted at a significance level of p < 0.05. Qualitative data were analyzed using thematic analysis, allowing a deeper understanding of healthcare providers’ insights into elderly patients’ experiences.
2.5. Ethical Considerations
Ethical approval was obtained from the Edo State Health Research and Ethics Committee, Edo State Ministry of Health.
Informed consent was secured from all participants.
Confidentiality, anonymity, and the right to withdraw without any consequences were assured.
3. Results
The key findings from the study on the elderly accessing healthcare in Edo State, alongside a detailed analysis of key variables, including demographic patterns, health complaints, facility preferences, and the implications for healthcare delivery is discussed below. These results are discussed in the context of existing research to identify areas for improvement and inform future healthcare policy and practice for elderly care in the State.
3.1. Descriptive Statistics
3.1.1. Proportion of Elderly Accessing Healthcare Services
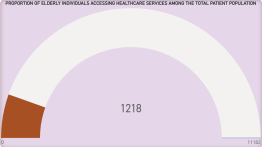
Figure 1. Proportion of Elderly Accessing Healthcare services among the total population.
The study revealed that elderly individuals (aged 60 and above) account for 9.82% of the total patient population across the surveyed healthcare centres. While this figure remains below 10%, it signifies a considerable proportion of elderly individuals seeking healthcare services. The relatively small proportion of elderly patients accessing healthcare highlights the ongoing barriers to healthcare utilization faced by this demographic, such as limited accessibility, high costs, and lack of awareness. However, the data underscores a need for enhanced healthcare services targeting the elderly, especially given Nigeria's increasing life expectancy and the growing demands of this age group.
3.1.2. Gender and Age Distribution of Elderly Patients
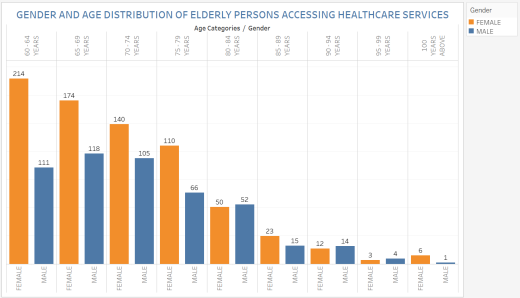
The gender distribution of elderly patients accessing healthcare services shows a clear disparity of 52% of elderly patients are female, while 33% are male. This is consistent with global findings that women are more likely to seek healthcare services due to stronger health-seeking behaviours and longer life expectancy.
Figure 2. Gender and age distribution of elderly persons accessing healthcare services.
3.1.3. Gender and Diagnosis
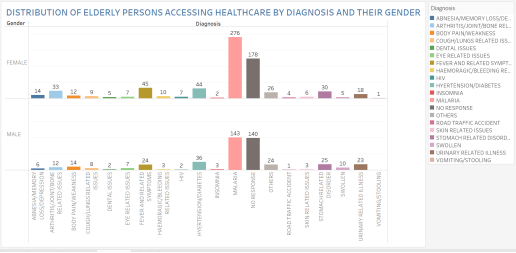
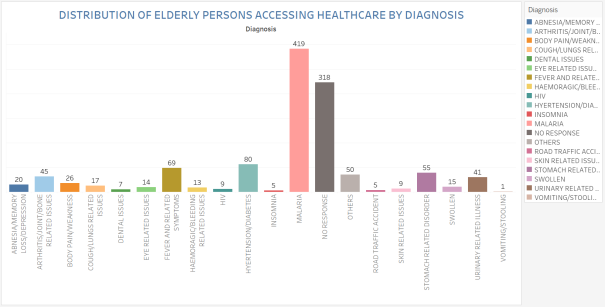
Figure 3. Distribution of elderly persons accessing healthcare by diagnosis.
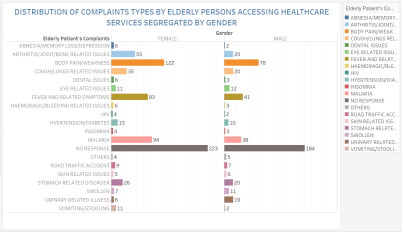
Higher rates of complaints related to malaria and generalized body weakness, which may be linked to both biological factors and sociocultural roles such as caregiving. Women in this age group are often primary caregivers for family members, which may increase their exposure to infectious diseases and health-related risks. However, a lower proportion of males seek healthcare services, and those who do present with more specific complaints, including urinary issues, skin conditions, and eye problems. The lower healthcare utilization among elderly males could be attributed to cultural norms that encourage men to avoid seeking medical care unless their health issues are severe, thus resulting in delayed treatment.
This study also observed that elderly patients ranged from 60 to 101 years, with an average age of 70.33 years. A notable 6.4% of elderly patients were aged 85 years or older, indicating a significant age-based variation in healthcare utilization. This relatively small proportion of elderly patients is most likely due to the demographic makeup of the state's population, where the elderly age group represents a smaller share.
The age distribution of respondents in this study spans 41 years, from 60 to 101 years old. This wide age range provide valuable insights into the changing healthcare needs and preferences of the elderly population in the State.
The relatively low proportion of patients aged 85+ seeking healthcare may be indicative of mobility challenges, frailty, or insufficient caregiver support. This group is also more likely to experience complex medical conditions that require specialized care, which may not always be available in local healthcare facilities.
The healthcare needs of the oldest patients require targeted interventions, including home-based care and improved accessibility to geriatric services at local healthcare centres. Enhancing transportation and mobility solutions for elderly patients is critical to facilitating access to medical care for those in this age group.
3.1.4. Common Health Complaints Reported by Elderly Patients
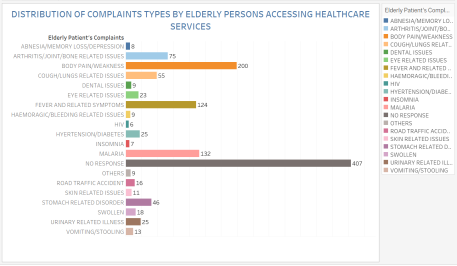
Figure 4. Common complaints types by elderly persons accessing healthcare services.
Body Pain and Weakness (16%): This was a frequently reported complaint and was associated with underlying conditions such as malaria, musculoskeletal issues, or chronic illnesses.
Malaria-Specific Complaints (11%): The prevalence of malaria-related symptoms suggests endemic challenges in the region, highlighting the need for targeted malaria prevention and treatment strategies.
Unspecified Complaints (33%): This category represented cases where a diagnosis could not be made or was incomplete, indicating potential gaps in diagnostic capabilities or access to healthcare.
3.1.5. Common Health Complaints Reported Among Elderly Patients by Gender
Figure 5. Common complaints types by elderly persons by gender accessing healthcare services.
Female patients exhibited a higher prevalence of malaria and generalized weakness, while male patients presented with more specific issues like urinary and skin conditions.
Implications:
Healthcare Training: There is a need to enhance diagnostic skills among healthcare workers to reduce the number of unspecified complaints and ensure timely and accurate diagnosis of common health issues.
Public Health Education: Malaria prevention programs should be tailored for the elderly population to increase awareness and reduce malaria-related health complaints among elderly individuals.
3.1.6. Utilization of Healthcare Facilities by Gender
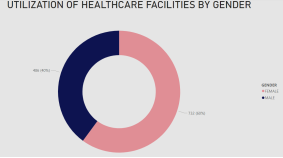
Elderly females are more likely to utilize healthcare facilities compared to their male counterparts. This suggests that elderly females have a greater inclination to seek medical attention when experiencing discomfort or illness.
Elderly males are less likely to utilize healthcare facilities, opting instead for alternative mediums of treatment. This may lead to delayed or foregone care, potentially exacerbating health issues and reducing quality of life.
Implications:
Targeted outreach programs: Implement targeted outreach programs to encourage elderly males to visit recognized healthcare facilities.
Awareness campaigns: Conduct awareness campaigns to educate elderly males about the importance of seeking medical attention when experiencing discomfort or illness.
Figure 6. Gender distribution of elderly accessing healthcare services.
Culturally sensitive approaches: Develop culturally sensitive approaches to address the unique needs and concerns of elderly males.
Incentivizing healthcare utilization: Consider incentivizing healthcare utilization among elderly males, such as offering free or low-cost consultations, tests, or treatments.
3.1.7. Identified Patterns in Complaints and Diagnoses for Informed Interventions
Figure 7. Distribution of elderly persons accessing healthcare services by diagnosis.
The survey carried out highlights the most common illnesses diagnosed among the elderly population. Malaria accounts for almost 35% of the total distribution, making it the most prevalent illness among the elderly population, Hypertension/Diabetes accounts for about 6.6% of the total distribution, fever and related issues accounts for about 5.7% of the total distribution.
Least Diagnosed Illnesses are vomiting and Stooling which accounts for about 0.08% of the total distribution, Insomnia and Road Traffic Accidents accounts for about 0.41% of the total distribution.
Implications
Prioritize malaria treatment: Focus on providing proper medication and treatment for malaria to reduce the alarming rate of malaria parasite diseases among the elderly population.
Improve access to healthcare: Ensure that elderly patients have access to healthcare facilities and services to address their health concerns.
Promote health education: Educate the elderly population about the importance of seeking medical attention early, especially for malaria and other prevalent illnesses.
3.1.8. Distribution of Elderly Persons Accessing Healthcare by Diagnosis and Their Outcome
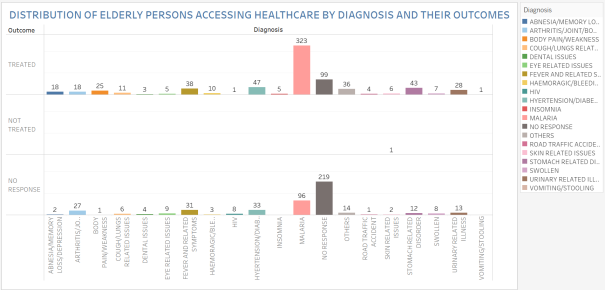
Figure 8. Distribution of elderly persons accessing healthcare services by diagnosis and outcomes.
Small proportion-Just a case (skin related ailment) where an Elderly patient was diagnosed and not treated possibly due the facilities inability to handle such ailment.
Potential health risks: Leaving diagnosed cases untreated can lead to further health complications and decreased quality of life.
Unknown treatment status:
Larger percentage: A significant proportion of cases have an unknown treatment status, which raises concerns about the follow-up and management of these cases.
Data quality issues: This highlights potential data quality issues, such as incomplete or inaccurate recording of treatment information.
Implications:
Improved data collection: Healthcare facilities should prioritize accurate and complete data collection to ensure that treatment information is properly recorded.
Follow-up and tracking: Healthcare providers should establish effective follow-up and tracking mechanisms to ensure that diagnosed cases receive appropriate treatment and care.
Patient education and empowerment: Patients should be educated and empowered to take an active role in their healthcare, including seeking follow-up care and adhering to treatment plans.
3.1.9. Healthcare Facility Preferences of Elderly Patients
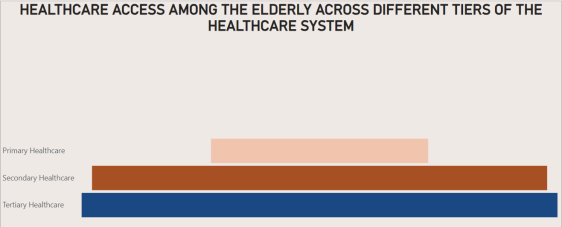
Tertiary Facilities (42%): Many elderly patients preferred tertiary healthcare centres, likely due to access to specialized care and advanced diagnostic technologies. Secondary Facilities (40%): Secondary healthcare centres were also popular, as they provide specialized care without the complexity or cost of tertiary centres. Primary Facilities (19%): Primary healthcare centres were the least favored, despite being more accessible and affordable.
There is a clear perception among elderly patients that tertiary and secondary healthcare centres provide higher-quality care. This could be due to the advanced diagnostic tools and specialists available at these facilities. Despite the preference for tertiary and secondary facilities, barriers such as distance, cost, and inadequate transportation mean that primary healthcare centres could play a larger role in providing care if adequately resourced.
Implications:
Strengthening Primary Care: Primary healthcare services need to be strengthened to improve access for the elderly, including adequate staffing, equipment, and specialized training in geriatrics.
Resource Allocation: A significant portion of healthcare resources should be allocated to improving the quality and availability of services at primary and secondary healthcare centres to ensure equitable access for all elderly patients.
Figure 9. Percentage of elderly accessing care at different tier of healthcare.

3.1.10. Variations in Healthcare Access Across Demographics
Gender Variations: Female elderly patients are more likely to seek healthcare services compared to males, suggesting a gendered disparity in health-seeking behaviour that may require targeted health interventions to engage elderly males more effectively.
Rural-Urban Divide: Elderly patients in rural areas tend to rely more on secondary healthcare facilities due to limited access to tertiary facilities, underscoring the importance of strengthening rural healthcare infrastructure to bridge this gap.
3.2. Inferential Statistics
3.2.1. Correlation Analysis Between Age and Complaints
A Pearson correlation analysis showed a very weak negative correlation between age and complaints (r = -0.029, p = 0.317). Although the coefficient suggests that as age increases, complaints may slightly decrease, the relationship is not statistically significant (p > 0.05). This indicates that age does not significantly influence the number of complaints among elderly patients accessing healthcare in Edo State.
3.2.2. Correlation Between Complaints and Healthcare Tiers
The analysis revealed a weak positive correlation between complaints and the tier of health facilities visited (r = 0.052, p = 0.069). Although the coefficient suggests a trend where more complaints are associated with higher-tier facilities, the relationship was not statistically significant (p > 0.05). This implies that the number of complaints does not significantly predict the healthcare tier accessed by the elderly.
3.2.3. Correlation Between Diagnosis and Healthcare Tiers
There was a very weak positive correlation between the number of diagnoses and healthcare tiers (r = 0.025, p = 0.383). This relationship was also not statistically significant, suggesting no strong evidence that healthcare tiers influence the number of diagnoses made among the elderly.
3.2.4. Correlation Between Complaints and Diagnosis
The Pearson correlation between complaints and diagnosis showed a moderate, statistically significant positive relationship (r = 0.353, p = 0.000). This implies that an increase in the number of complaints was strongly associated with an increase in the number of diagnoses made. The result emphasizes the critical role of patient-reported symptoms in elderly healthcare and reinforces the importance of taking complaints seriously in diagnosis.
3.2.5. Summary of Inferential Findings
Only the relationship between complaints and diagnoses was statistically significant, demonstrating that the more complaints elderly patients present with, the more likely a diagnosis will be made. Other relationships (age vs. complaints, complaints vs. tiers, diagnosis vs. tiers) showed weak or negligible associations and were not statistically significant. These findings suggest that patient complaints are a key driver of diagnosis in elderly care, rather than demographic or facility-related factors.
4. Discussion
4.1. Proportion of Elderly Patients in Healthcare Facilities
The finding that 9.82% of total patients in the study population were aged 60 years and above is consistent with the global and national trend of an ageing population. According to the United Nations (2023), the population of persons aged 60+ is projected to double by 2050, particularly in developing regions such as sub-Saharan Africa. The 9.82% representation in healthcare facilities could suggest both a growing demand for geriatric care and persistent barriers to access.
A study by in south-eastern Nigeria, Uganda, Ghana and South Africa found a similarly low health service utilization rate among older adults, attributing it to socioeconomic challenges, lack of geriatric care specialization, and physical inaccessibility of facilities. This underscores the urgent need for age-disaggregated planning in Nigeria’s health information systems .
4.2. Gender Differences in Healthcare Utilization
The slightly higher proportion of female elderly patients (52%) aligns with the established demographic phenomenon of female longevity and healthcare utilization behaviour. Women generally outlive men due to both biological and behavioral factors and are more likely to seek medical help . This study also correlate with the finding of , who noticed that elderly outpatient clinic data from southwestern Nigeria reports females outnumbering males by 1.7: 1 in healthcare access and utilization and this is linked to longer female life expectancy and higher clinic-seeking behavior. This trend is reinforced by cultural roles in Nigeria, where elderly women often assume caregiving roles within extended families and thus remain more engaged with healthcare systems.
Conversely, the underrepresentation of elderly men in healthcare centres may reflect ingrained cultural norms where men may delay care due to perceptions of strength or invulnerability . This gender gap has implications for targeted interventions to encourage health-seeking behaviour in older men, especially in preventive care contexts.
4.3. Age Distribution and Decline in Utilization Among the Oldest-Old
The study found that most patients fell within the 60–70 years age range, with a marked decline in utilization among those aged 85+. This is consistent with findings by the study who found that very old adults often face increasing physical limitations, cognitive decline, and social isolation that hinder their ability to access healthcare.
The ‘oldest-old’ may also suffer from “hidden morbidity,” where multiple comorbid conditions are underdiagnosed due to atypical presentations, compounded by healthcare providers' limited geriatric training. For example, cognitive impairments, sensory deficits, or communication barriers may lead to underreporting of symptoms .
4.4. Nature of Health Complaints and Diagnostic Outcomes
Body pain, weakness, and malaria-like symptoms dominated the complaint profile of elderly patients. This reflects both the physiological vulnerability of ageing bodies and the prevalence of infectious diseases in the Nigerian context. Elderly individuals have weakened immune responses, making them more susceptible to recurrent malaria infections despite previous exposure .
However, 33% of complaints were vague or unrecorded, raising concerns about poor documentation or incomplete clinical assessments. reported similar findings, highlighting how overburdened healthcare workers in Nigeria often provide symptomatic rather than holistic, person-centred care, especially for elderly patients.
This study’s finding of a moderate positive correlation (r = 0.353, p < 0.01) between the number of complaints and diagnoses affirms the clinical intuition that more reported symptoms increase the likelihood of detecting multiple morbidities. It underscores the need for elderly patients to be encouraged to report all symptoms and for clinicians to be trained in geriatric syndromes and polypharmacy management.
4.5. Healthcare Tier Preferences
Elderly patients’ preference for tertiary (42%) and secondary (40%) facilities over primary care (18%) reveals a lack of confidence in the quality or availability of care at the primary healthcare (PHC) level. In a study across six States, found that PHC were grossly underutilized by elderly Nigerians due to frequent stockouts, inadequate staffing, and poor infrastructure.
Patients perceive tertiary hospitals as better equipped with specialists and diagnostic capabilities. While this reflects rational health-seeking behaviour , it results in the overcrowding of tertiary institutions and undermines the efficiency of the referral system. This utilization pattern signals the need to re-invest in PHC revitalization, especially under the Basic Health Care Provision Fund (BHCPF) mandate.
4.6. Rural-Urban Divide
A significant portion of elderly patients came from urban LGAs, particularly in Egor and Oredo Local Government Areas. In contrast, those in rural LGAs like Etsako East and Akoko-Edo faced higher barriers to access healthcare services due to longer travel distances, poor roads, and limited public transportation options. A study affirmed that geographic inaccessibility disproportionately affects elderly rural dwellers, resulting in late or no presentation at health facilities.
Urban-rural disparities are further exacerbated by uneven distribution of health personnel and the concentration of secondary/tertiary hospitals in urban centres. This systemic imbalance is a core reason for the observed disparities in healthcare outcomes.
5. Conclusion
This study provides compelling evidence of the evolving healthcare needs of the elderly population in Edo State. The data reveal patterns consistent with national and global trends in ageing but also illuminate unique local challenges, such as underutilization of PHC, rural access barriers, gender disparities, and vague diagnostic documentation. Elderly healthcare is still largely reactive and fragmented, with significant structural and systemic inefficiencies. A shift toward proactive, integrated, and age-sensitive health planning is needed. The health system must evolve to meet the demands of a demographic that will only continue to grow, with chronic diseases, multimorbidity, and long-term care becoming central concerns.
6. Recommendations
A. Health System Strengthening
1) Establish Geriatric Units in Secondary and Primary Care Facilities:
Train healthcare workers on geriatric syndromes, frailty assessment, and polypharmacy. This will enhance diagnostic accuracy and age-appropriate treatment.
2) Upgrade DHIS2 to Support Age-Segregated Reporting:
Modify routine data tools to collect age-specific indicators to enable effective planning for elderly care programs.
3) Improve PHC Infrastructure and Staffing:
Invest in PHC revitalization with a focus on rural areas through the BHCPF, ensuring continuous drug supply, clean water, and referral linkages.
B. Policy and Financing
4) Expand Health Insurance for the Elderly:
Introduce a subsidized elderly care scheme under NHIA to reduce out-of-pocket spending and encourage early presentation.
5) Integrate Elderly Care in National and State Health Policies:
Include geriatric health in the State Strategic Health Development Plan II (SSHDP II) and Annual Operational Plans (AOPs).
C. Community-Based Interventions
6) Mobile Clinics and Home-Based Care:
Deploy mobile clinics and trained community health workers to reach immobile elderly persons, especially in hard-to-reach rural areas.
7) Transportation Vouchers or Community Shuttles:
Collaborate with NGOs to provide elderly-specific transportation options to reduce missed appointments due to mobility issues.
D. Research and Advocacy
8) Continuous Monitoring and Research on Elderly Health Trends:
Fund studies on chronic disease prevalence, elderly mental health, and long-term care needs in Edo State.
9) Exploration of Traditional Medicine Use:
10) Investigate the role of traditional medicine in elderly healthcare practices to understand its impact and potential integration into formal healthcare systems.
11) Awareness Campaigns:
Engage religious leaders, traditional rulers, and media to promote elderly health rights and encourage routine checkups.
Abbreviations

PHC

Primary Healthcare Center

OPD

Outpatient Department

LGA

Local Government Area

BHCPF

Basic Health Care Provision Fund

SSHDP II

State Strategic Health Development Plan II

DHIS2

District Health Information Software 2

Conflicts of Interest
There is no conflicts of interest among the authors.
References
[1] World Health Organization. (2022). Ageing and health.
[2] Sudharsanan, N., Bloom, D. E., & Sudharsanan, N. (2018). The demography of aging in low-and middle-income countries: chronological versus functional perspectives. In Future directions for the demography of aging: Proceedings of a workshop (pp. 309-338). Washington, DC: National Academies Press.
[3] Okoye, U. O., & Asa, S. (2014). Care of the aged in Nigeria: A review. International Journal of Sociology and Anthropology, 6(7), 123–131.
[4] Wandera, S. O., Kwagala, B., & Ntozi, J. (2015). Determinants of access to healthcare by older persons in Uganda: a cross-sectional study. International journal for equity in health, 14(1), 26.
[5] Nwakasi, C., Brown, J. S., Subedi, S., & Darlingtina, E. (2021). Depression, functional disability, and accessing health care among older Ghanaians and South Africans: A comparative study based on WHO study on global ageing and adult health (SAGE). Aging & Mental Health, 25(6), 1077-1085.
[6] Saka, S. A., et al. (2019). Patterns of health-seeking behavior among older adults in Nigeria. Journal of Aging Research, 2019, Article ID 5381404.
[7] Agbeyegbe, E. B., Francis, E. O., & Ibeodo, J. C. (2025). Gender Distribution of Chronic Diseases and Healthcare Seeking Behaviour: Evidence from a Cohort of 39, 876 Patients Across Nigeria. Asian Basic and Applied Research Journal, 7(1), 320-326.
[8] Ajayi, A. I., & Akpan, W. (2021). Masculinity and men’s health-seeking behavior in Nigeria. Social Science & Medicine, 275, 113812. Ani, C. O. (2014). Challenges of ageing in Nigeria: Implications for policy directions. African Population Studies, 28(2), 1262–1270.
[9] Adebowale, S. A., et al. (2017). Elderly care in Nigeria: A neglected issue in the health.
[10] Gureje, O., et al. (2019). Mental and physical health in elderly Nigerians: A cross-sectional study. BMJ Global Health, 4(2), e001223.
[11] Sokhna, C., et al. (2014). Malaria in older adults: The forgotten vulnerable group? Lancet Infectious Diseases, 14(6), 520–521.
[12] Ogunniyi, A., et al. (2022). Clinical profiles and healthcare needs of elderly Nigerians. Annals of African Medicine, 21(1), 45–53.
[13] Adewole, D. A., et al. (2020). Factors influencing utilization of PHC by older Nigerians. International Journal of Health Policy and Management, 9(7), 302–309.
[14] Osiya, D. A., Ogaji, D. S., & Onotai, L. (2017). Patients’ satisfaction with healthcare: comparing general practice services in a tertiary and primary healthcare settings. The Nigerian Health Journal, 17(1).
[15] Jiang, S., Gu, Y., Yang, F., Wu, T., Wang, H., Cutler, H., & Zhang, L. (2020). Tertiary hospitals or community clinics? An enquiry into the factors affecting patients' choice for healthcare facilities in urban China. China Economic Review, 63, 101538.
[16] Zhang, W., Ung, C. O. L., Lin, G., Liu, J., Li, W., Hu, H., & Xi, X. (2020). Factors contributing to patients' preferences for primary health care institutions in China: a qualitative study. Frontiers in public health, 8, 414.
[17] Obembe, T. A., et al. (2021). Rural-urban disparities in healthcare access in Nigeria. Journal of Public Health in Africa, 12(2), 1773.
Cite This Article
  • APA Style

    Omijie, G., Oshiomhole, C. A., Iruobe, L., Aigbogun, E. I., Ugiesomhe, M. T., et al. (2026). Healthcare Access Patterns and Challenges Among the Elderly in Edo State, Nigeria: A Cross-sectional Mixed-methods Study. International Journal of Gerontology and Geriatrics, 1(1), 1-11. https://doi.org/10.11648/j.ijgege.20260101.11

    Copy | Download

    ACS Style

    Omijie, G.; Oshiomhole, C. A.; Iruobe, L.; Aigbogun, E. I.; Ugiesomhe, M. T., et al. Healthcare Access Patterns and Challenges Among the Elderly in Edo State, Nigeria: A Cross-sectional Mixed-methods Study. Int. J. Gerontol. Geriatr. 2026, 1(1), 1-11. doi: 10.11648/j.ijgege.20260101.11

    Copy | Download

    AMA Style

    Omijie G, Oshiomhole CA, Iruobe L, Aigbogun EI, Ugiesomhe MT, et al. Healthcare Access Patterns and Challenges Among the Elderly in Edo State, Nigeria: A Cross-sectional Mixed-methods Study. Int J Gerontol Geriatr. 2026;1(1):1-11. doi: 10.11648/j.ijgege.20260101.11

    Copy | Download

  • @article{10.11648/j.ijgege.20260101.11,
      author = {Godswill Omijie and Cyril Adams Oshiomhole and Lauretta Iruobe and Edwin Ighodaro Aigbogun and Maryjane Timothy Ugiesomhe and Emmanuel Aiyegbeni and Ehigiator Clement Idiagbonya and Odion Paulina Ototobor and Osemwegie Vincent Omorodion and Erhahon Isimamwen and Esther Omigie and Racheal Etuwe Ugbodaga and Oritsemisan Blessing Jiringho and Mary Osuare Oboigbe and Angela Levi Kangla},
      title = {Healthcare Access Patterns and Challenges Among the Elderly in Edo State, Nigeria: A Cross-sectional Mixed-methods Study},
      journal = {International Journal of Gerontology and Geriatrics},
      volume = {1},
      number = {1},
      pages = {1-11},
      doi = {10.11648/j.ijgege.20260101.11},
      url = {https://doi.org/10.11648/j.ijgege.20260101.11},
      eprint = {https://article.sciencepublishinggroup.com/pdf/10.11648.j.ijgege.20260101.11},
      abstract = {The global increase in life expectancy has increased among the elderly population, creating challenges for healthcare systems in developing countries like Nigeria. In Edo State, accessing healthcare services among elderly population remains limited. Understanding healthcare access patterns and challenges among the elderly is crucial for developing targeted interventions that promote healthy ageing in line with the United Nations Decade of Healthy Ageing (2021–2030). To determine elderly access to healthcare services, a cross-sectional, mixed-methods study sampled elderly individuals of the ages of 60 years and above across primary, secondary, and tertiary healthcare facilities in Edo State using multistage cluster sampling. Quantitative data were extracted from outpatient registers, capturing demographics, complaints, diagnoses, and outcomes. Qualitative interviews with healthcare workers provided additional insights. Data analysis included descriptive statistics, correlation tests, and thematic analysis. The data showed that elderly patients constituted 9.82% of outpatient visits, mostly female (52%) with an average age of 70 years. Tertiary (42%) and secondary facilities (40%) were preferred over primary healthcare centres-PHC (19%). Common complaints included body pain, weakness, and malaria-related symptoms, with a moderate positive correlation between number of complaints and diagnoses (r = 0.353, p < 0.01). Barriers identified qualitatively included limited geriatric services, poor data disaggregation, rural access challenges and lack of infrastructure at the PHC. Further findings revealed gender and age disparities in elderly healthcare utilization, preference for higher-tier facilities, and systemic barriers limiting care at primary levels. Strengthening age-sensitive healthcare systems, improving data practices, establish geriatric units, training more healthcare workers on elderly care, age-disaggregated data systems, strengthening rural primary healthcare, expanding subsidized health insurance for the elderly, and implementing mobile clinics and transportation support for the elderly. These are needed to address elderly healthcare needs in Edo State, Nigeria.},
     year = {2026}
    }
    

    Copy | Download

  • TY  - JOUR
    T1  - Healthcare Access Patterns and Challenges Among the Elderly in Edo State, Nigeria: A Cross-sectional Mixed-methods Study
    AU  - Godswill Omijie
    AU  - Cyril Adams Oshiomhole
    AU  - Lauretta Iruobe
    AU  - Edwin Ighodaro Aigbogun
    AU  - Maryjane Timothy Ugiesomhe
    AU  - Emmanuel Aiyegbeni
    AU  - Ehigiator Clement Idiagbonya
    AU  - Odion Paulina Ototobor
    AU  - Osemwegie Vincent Omorodion
    AU  - Erhahon Isimamwen
    AU  - Esther Omigie
    AU  - Racheal Etuwe Ugbodaga
    AU  - Oritsemisan Blessing Jiringho
    AU  - Mary Osuare Oboigbe
    AU  - Angela Levi Kangla
    Y1  - 2026/02/11
    PY  - 2026
    N1  - https://doi.org/10.11648/j.ijgege.20260101.11
    DO  - 10.11648/j.ijgege.20260101.11
    T2  - International Journal of Gerontology and Geriatrics
    JF  - International Journal of Gerontology and Geriatrics
    JO  - International Journal of Gerontology and Geriatrics
    SP  - 1
    EP  - 11
    PB  - Science Publishing Group
    UR  - https://doi.org/10.11648/j.ijgege.20260101.11
    AB  - The global increase in life expectancy has increased among the elderly population, creating challenges for healthcare systems in developing countries like Nigeria. In Edo State, accessing healthcare services among elderly population remains limited. Understanding healthcare access patterns and challenges among the elderly is crucial for developing targeted interventions that promote healthy ageing in line with the United Nations Decade of Healthy Ageing (2021–2030). To determine elderly access to healthcare services, a cross-sectional, mixed-methods study sampled elderly individuals of the ages of 60 years and above across primary, secondary, and tertiary healthcare facilities in Edo State using multistage cluster sampling. Quantitative data were extracted from outpatient registers, capturing demographics, complaints, diagnoses, and outcomes. Qualitative interviews with healthcare workers provided additional insights. Data analysis included descriptive statistics, correlation tests, and thematic analysis. The data showed that elderly patients constituted 9.82% of outpatient visits, mostly female (52%) with an average age of 70 years. Tertiary (42%) and secondary facilities (40%) were preferred over primary healthcare centres-PHC (19%). Common complaints included body pain, weakness, and malaria-related symptoms, with a moderate positive correlation between number of complaints and diagnoses (r = 0.353, p < 0.01). Barriers identified qualitatively included limited geriatric services, poor data disaggregation, rural access challenges and lack of infrastructure at the PHC. Further findings revealed gender and age disparities in elderly healthcare utilization, preference for higher-tier facilities, and systemic barriers limiting care at primary levels. Strengthening age-sensitive healthcare systems, improving data practices, establish geriatric units, training more healthcare workers on elderly care, age-disaggregated data systems, strengthening rural primary healthcare, expanding subsidized health insurance for the elderly, and implementing mobile clinics and transportation support for the elderly. These are needed to address elderly healthcare needs in Edo State, Nigeria.
    VL  - 1
    IS  - 1
    ER  - 

    Copy | Download

Author Information
  • Abstract
  • Keywords
  • Document Sections

    1. 1. Introduction
    2. 2. Methodology
    3. 3. Results
    4. 4. Discussion
    5. 5. Conclusion
    6. 6. Recommendations
    Show Full Outline
  • Abbreviations
  • Conflicts of Interest
  • References
  • Cite This Article
  • Author Information