Case Report on Rare Presentation of Hepatic Cavernous Haemangioma with Diffuse Hemangiomatosis from Yekatit 12 Hospital Medical College Addis Ababa, Ethiopia
Hepatic hemangiomas are the most common liver tumors. They are usually small and asymptomatic, and most often detected incidentally due to the increasing use of imaging modalities. While hemangiomas can occur at any age, they are most commonly found in individuals in their 4th to 6th decade. The majority of haemangiomas are less than 5 cm in size, while those larger than 10 cm are classified as giant hemangiomas. Most of the hemangiomas are solitary, but in 40% of cases, it may involve both right and left lobes and in rare cases, it is associated with diffuse hemangiomatosis. Most hemangiomas are asymptomatic but rarely they may present as an abdominal mass or pain. Large lesions located in the left lobe of the liver may cause pressure effects on adjacent structures such as stomach and bile duct causing nausea leading to anorexia, nausea and jaundice. Rarely large hemangiomas may compress Inferior Vena cava and patients may present with lower limb edema. The diagnosis of hepatic haemangioma mostly depends on cross-sectional imaging. Modalities like CT and MRI are used to diagnose hemangioma and to rule out other differential diagnoses, such as cysts, hepatic adenomas, hepatocellular carcinoma, and distant metastases. Laboratory tests like α-fetoprotein (AFP), carcinoembryonic antigen (CEA), cancer antigen 125 (CA 125) and cancer antigen 19-9 (CA19-9) are important to help rule out malignant lesions. Most hemangiomas do not require any surgical management. However, in patients who present with bothersome symptoms, have a larger size (greater than 10 cm), experience complications like rupture, or have lesions where malignancy cannot be ruled out, surgical treatment should be considered. In our case, the patient presented with compression effects and was diagnosed with a huge hemangioma with hemangiomatous. Resection was performed, and the patient was relieved of symptoms after the surgical intervention.
This is an Open Access article, distributed under the terms of the Creative Commons Attribution 4.0 International License (http://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, distribution and reproduction in any medium or format, provided the original work is properly cited.
Diffuse Hepatic Hemangiomatosis, Cavernous Hemangioma, Oral Contraceptives, Surgery
1. Introduction
Hepatic hemangiomas are benign liver hyper vascular venous malformations consisting of blood-filled cavities lined by endothelial cells and fed by hepatic arterial circulation. They are categorized based on size as small hemangioma (1 to 2cm), typical hemangioma (2 to 10cm) and giant hemangioma (greater than 10cm). Hepatic hemangiomatosis is a rare condition characterized by replacement of the hepatic parenchyma with hemangiomatous lesions, and it doesn’t have any clear border. Though the aetiology of hepatic hemangiomatosis is unknown it is associated with usage of oral contraceptive medications
[1]
Bajenaru N, Balaban V, Săvulescu F, Campeanu I, Patrascu T. Hepatic hemangioma -review-. J Med Life. 2015; 8 Spec Issue (Spec Issue):4-11.
[2]
Ota T, Kondo S, Kato K, Hirano S, Ambo Y, Tanaka E, et al. A rare case of cavernous hemangioma accompanied with diffuse hepatic hemangiomatosis. Surg Case Rep. 2020 Sep 29; 6(1):251.
Giannitrapani L, Soresi M, La Spada E, Cervello M, D'Alessandro N, Montalto G. Sex hormones and risk of liver tumor. Ann N Y Acad Sci. 2006 Nov; 1089:228-36.
Ponnatapura J, Kielar A, Burke LMB, Lockhart ME, Abualruz AR, Tappouni R, et al. Hepatic complications of oral contraceptive pills and estrogen on MRI: controversies and update - Adenoma and beyond. Clin Imaging. 2021; 80:87-103.
. We present a case report on rare presentation of a hepatic Cavernous Haemangioma with diffuse haemangiomatosis for whom resection was performed.
2. Case Summary
This is a case of a 47 years old female patient who presented to surgical referral clinic with a compliant of progressive swelling over upper abdomen of seven years duration. The swelling was initially small in size and increases to attain the current size. Associated with this she had a history of early satiety and loss of appetite of one year duration. She also had anterior neck swelling of 12 years duration. She had a history of contraceptive usage.
On physical examination, she was chronically sick looking. Her vital signs showed a PR of 94 beat per minute and a BP of 100/80 mmHg. She had a pink conjunctiva, non-icteric sclera, no lymphadenopathy, and there was a 4 x 3cm anterior neck mass which moves with swallowing. Her chest examination was normal. Abdominal examination revealed 10cm x 15cm intra-abdominal mass that reaches to the pelvis and crosses the midline to the left.
Investigation WBC 4.4k/ul with neutrophil count of 70.2%, haemoglobin of 11.2mg/dl, haematocrit of 32.6% and a Platelet count of 238K. Viral markers for hepatitis B and C were negative. Albumin 3.8g/dl, ALT 59U/L, AST 53U/L, ALP 286U/L. Serum bilirubin, creatinine, serum electrolyte, coagulation profile and thyroid function tests were all in normal range.
An Abdomeno-pelvic CT scan showed multiple homogeneously hyperatunuated poorly defined lesion diffusely involving the liver and large pedunculated mass lesion arising from inferior surface of segment of 4, measuring 21cm by 10cm by 29cm with peripheral nodular enhancement in arterial phase and centripetal enhancement in subsequent phases with central calcification in the lesions likely of hemangiomatosis of liver.
After the patient and family was counselled about the disease condition and planned procedure, informed consent was obtained. Three units of whole blood, 3 units of FFP and 3 units of platelet prepared the patient transferred to OR table with impression of Giant haemangioma.
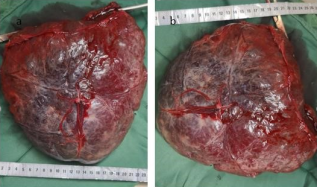
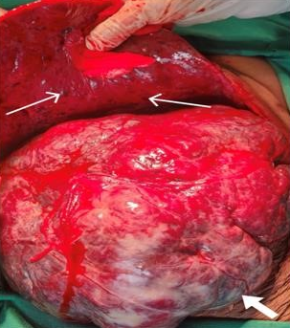
The abdomen was cleaned with povidone-iodine and draped with sterile drape and entered via an inverted L inscion in the upper abdomen. Intraoperative finding revealed giant haemangioma which arises from the caudate lobe with diffuse hemangiomatosis in the other segments of the liver (Figure 2). There was a clear demarcation between caudate lobe and haemangioma then hepatoduodenal ligament with portal triad isolated pringle maneuver applied, attachment of mass from liver dissected, and mass isolated and segmental resection of mass done from caudate lobe of liver (Figure 1). Hemostasis was secured with estimated blood loss of 200ml. Abdomen lavaged with saline drain left closed in layers and the patient extubated smoothly and transferred to PACU and ward.
On her first postop day patient started on sips tolerated well and her diet was escalated. A postoperative CBC showed Hemoglobin of 10.1g/dl. The drain output was around 50 milliliters. The patient had smooth postoperative course was and she was discharged on her 5th postoperative day. After 1 week she come to surgical referral clinic stitch removed and the patient was in stable condition.
3. Discussion
Hepatic haemangioma are the most common hepatic benign lesions. Majority of haemangiomas are size less than 5cm and those measuring greater than 10cm are referred to as Cavernous Haemangioma. Hepatic hemangiomatosis is a rare condition characterized by replacement of the hepatic parenchyma with hemangiomatous lesions, and is associated with hereditary diseases such as skeletal hemangiomatosis, Klippel-Trenaunay-Weber and Rendu–Osler– Weber disease
[1]
Bajenaru N, Balaban V, Săvulescu F, Campeanu I, Patrascu T. Hepatic hemangioma -review-. J Med Life. 2015; 8 Spec Issue (Spec Issue):4-11.
[2]
Ota T, Kondo S, Kato K, Hirano S, Ambo Y, Tanaka E, et al. A rare case of cavernous hemangioma accompanied with diffuse hepatic hemangiomatosis. Surg Case Rep. 2020 Sep 29; 6(1):251.
Giannitrapani L, Soresi M, La Spada E, Cervello M, D'Alessandro N, Montalto G. Sex hormones and risk of liver tumor. Ann N Y Acad Sci. 2006 Nov; 1089:228-36.
Both malignant and benign hepatic lesions like haemangioma, focal nodular hyperplasia, hepatocellular adenoma, and tumor-like lesions like peliosis hepatis have been associated with the use of oral contraceptives and related to pregnancy
[4]
Baek S, Sloane CE, Futterman SC. Benign liver cell adenoma associated with use of oral contraceptive agents. Ann Surg. 1976 Mar; 183(3):239-42.
Neuberger J, Nunnerley HB, Davis M, Portmann B, Laws JW, Williams R. Oral-contraceptive-associated liver tumours: occurrence of malignancy and difficulties in diagnosis. Lancet. 1980 Feb 9; 315(8163):273-6.
Ponnatapura J, Kielar A, Burke LMB, Lockhart ME, Abualruz AR, Tappouni R, et al. Hepatic complications of oral contraceptive pills and estrogen on MRI: controversies and update - Adenoma and beyond. Clin Imaging. 2021; 80:87-103.
. In our case the patient had history of contraceptive usage.
Most hemangiomas are asymptomatic but rarely they may present as an abdominal mass or pain, symptoms depend on the hemangioma’s size and anatomical location. Large lesions in the left lobe of the liver can cause pressure effects on adjacent structures. This may lead to gastric outlet obstruction, resulting in anorexia and nausea, as well as bile duct obstruction, causing jaundice. It can also result in Budd-Chiari syndrome following hepatic venous outflow obstruction.. Rarely large hemangiomas may compress Inferior Vena cava and patients may present with lower limb edema
Westwood ME, Joore MA, Grutters JPC, Redekop WK, Armstrong N, Lee K, et al. Contrast-enhanced ultrasound using SonoVue compared with contrast-enhanced computer tomography and contrast-enhanced magnetic resonance imaging for the characterization of focal liver lesions and detection of liver metastases: a systematic review and cost-effectiveness analysis. Health Technol Assess. 2013; 17(16):1-243.
Figure 1. shows resected specimen of hemangioma from caudate of the liver A. width of 21cm, B, length of 23cm.
Laboratory tests like α-fetoprotein (AFP), carcinoembryonic antigen (CEA), cancer antigen 125 (CA 125) and cancer antigen 19-9 (CA19-9) are important to help rule out malignant lesions. Typical haemangioma appears on CT scans as a hypodense lesion with peripheral nodular enhancement in the early phase, followed by a centripetal pattern of filling during the late phase
[8]
Nakanuma Y. Non-neoplastic nodular lesions in the liver. Pathol Int. 1995 Oct; 45(10):703-14.
. Hemangiomas with scar and huge cystic one’s enhancement may not be seen
[16]
Terkivatan T, Vrijland WW, Den Hoed PT, De Man RA, Hussain SM, Tilanus HW, et al. Size of lesion is not a criterion for resection during management of giant liver haemangioma. Br J Surg. 2002; 89(10):1240.
[16]
. In our case tri-phasic CT-scan shows typical features of haemangioma in segment 4 with peripheral nodular enhancement in arterial phase and centripetal enhancement in subsequent phases with central calcification in the lesions but intraoperatively the mass arises from caudate lobe rather than segment 4.
Figure 2. intraoperative finding of hemangioma which arises from caudate lobe (wide arrow) and visible hemangimatosis from left lobe of the liver (narrow arrows).
Most of hepatic hemangiomas are small in size and asymptomatic with no report of malignant transformation. Follow up with regular imaging every six month or annually in order to assess any increment is recommended in asymptomatic patients. Frequent follow-up is indicated in patients who have new-onset pain or are unresponsive to analgesics, estrogen therapy, and during pregnancy. Several medications, including antiangiogenic agents such as sorafenib and sirolimus in combination with propranolol, azithromycin, and corticosteroids, have demonstrated potential for inducing hemangioma regression. Despite this, no pharmacological therapy is currently recognized as a proven method for reducing hemangioma size. Rapid growth in size, size greater than 10cm, symptoms associated with extrinsic compressions, pain despite analgesics, rupture or other complications are indications to do surgery. Arterial embolization or radiofrequency ablation are other options of management apart from surgery
[4]
Baek S, Sloane CE, Futterman SC. Benign liver cell adenoma associated with use of oral contraceptive agents. Ann Surg. 1976 Mar; 183(3):239-42.
Abdel Wahab M, El Nakeeb A, Ali MA, Mahdy Y, Shehta A, Abdulrazek M, et al. Surgical management of giant hepatic hemangioma: single center's experience with 144 patients. J Gastrointest Surg. 2018; 22(4):849-58.
Yamashita S, Okita K, Harada K, Hirano A, Kimura T, Kato A, et al. Giant cavernous hepatic hemangioma shrunk by use of sorafenib. Clin J Gastroenterol. 2013 Feb; 6(1):55-62.
Zhang J, Ye Z, Tan L, Luo J. Giant hepatic hemangioma regressed significantly without surgical management: a case report and literature review. Front Med (Lausanne). 2021 Aug 19; 8:712324.
Four surgical methods can be used for treatment of hemangioma: liver resections, enucleation, lobectomy, and liver transplantation either by open surgery or minimally invasive procedures like laparoscopy or robotic surgery. The choice of the procedure depends on size and location, but also by the preference and skill of the surgeon
[10]
Jackson NR, Hauch A, Hu T, Buell JF, Slakey DP, Kandil E. The Safety and Efficacy of Approaches to Liver Resection: A Meta-Analysis. JSLS. 2015 Jan-Mar; 19(1): e2014.00186.
. According to some reports, trans arterial embolization (TAE) is recommended for large hemangiomas to reduce bleeding and make inoperable cases operable
[15]
Zhou JX, Huang JW, Wu H, Zeng Y. Successful liver resection in a giant hemangioma with intestinal obstruction after embolization. World J Gastroenterol. 2013; 19(19):2974-8.
. In our case we did segmental resection of the hemangioma from the caudate lobe of the liver via open surgery.
4. Conclusion
We report the successful resection of huge haemangioma arising in the setting of hepatic hemangiomatosis. The finding of huge haemangioma in hemangiomatosis is a rare scenario with only few cases were reported and also the case report finds an association between the use of OCP and haemangioma.
Bajenaru N, Balaban V, Săvulescu F, Campeanu I, Patrascu T. Hepatic hemangioma -review-. J Med Life. 2015; 8 Spec Issue (Spec Issue):4-11.
[2]
Ota T, Kondo S, Kato K, Hirano S, Ambo Y, Tanaka E, et al. A rare case of cavernous hemangioma accompanied with diffuse hepatic hemangiomatosis. Surg Case Rep. 2020 Sep 29; 6(1):251.
Giannitrapani L, Soresi M, La Spada E, Cervello M, D'Alessandro N, Montalto G. Sex hormones and risk of liver tumor. Ann N Y Acad Sci. 2006 Nov; 1089:228-36.
Neuberger J, Nunnerley HB, Davis M, Portmann B, Laws JW, Williams R. Oral-contraceptive-associated liver tumours: occurrence of malignancy and difficulties in diagnosis. Lancet. 1980 Feb 9; 315(8163):273-6.
Westwood ME, Joore MA, Grutters JPC, Redekop WK, Armstrong N, Lee K, et al. Contrast-enhanced ultrasound using SonoVue compared with contrast-enhanced computer tomography and contrast-enhanced magnetic resonance imaging for the characterization of focal liver lesions and detection of liver metastases: a systematic review and cost-effectiveness analysis. Health Technol Assess. 2013; 17(16):1-243.
Jackson NR, Hauch A, Hu T, Buell JF, Slakey DP, Kandil E. The Safety and Efficacy of Approaches to Liver Resection: A Meta-Analysis. JSLS. 2015 Jan-Mar; 19(1): e2014.00186.
Ponnatapura J, Kielar A, Burke LMB, Lockhart ME, Abualruz AR, Tappouni R, et al. Hepatic complications of oral contraceptive pills and estrogen on MRI: controversies and update - Adenoma and beyond. Clin Imaging. 2021; 80:87-103.
Abdel Wahab M, El Nakeeb A, Ali MA, Mahdy Y, Shehta A, Abdulrazek M, et al. Surgical management of giant hepatic hemangioma: single center's experience with 144 patients. J Gastrointest Surg. 2018; 22(4):849-58.
Yamashita S, Okita K, Harada K, Hirano A, Kimura T, Kato A, et al. Giant cavernous hepatic hemangioma shrunk by use of sorafenib. Clin J Gastroenterol. 2013 Feb; 6(1):55-62.
Zhang J, Ye Z, Tan L, Luo J. Giant hepatic hemangioma regressed significantly without surgical management: a case report and literature review. Front Med (Lausanne). 2021 Aug 19; 8:712324.
Zhou JX, Huang JW, Wu H, Zeng Y. Successful liver resection in a giant hemangioma with intestinal obstruction after embolization. World J Gastroenterol. 2013; 19(19):2974-8.
Terkivatan T, Vrijland WW, Den Hoed PT, De Man RA, Hussain SM, Tilanus HW, et al. Size of lesion is not a criterion for resection during management of giant liver haemangioma. Br J Surg. 2002; 89(10):1240.
Desta, G., Tilahun, T., Assefa, G., Lebeza, Y. (2025). Case Report on Rare Presentation of Hepatic Cavernous Haemangioma with Diffuse Hemangiomatosis from Yekatit 12 Hospital Medical College Addis Ababa, Ethiopia. International Journal of Medical Research and Innovation, 1(1), 28-31. https://doi.org/10.11648/j.ijmri.20250101.14
Desta, G.; Tilahun, T.; Assefa, G.; Lebeza, Y. Case Report on Rare Presentation of Hepatic Cavernous Haemangioma with Diffuse Hemangiomatosis from Yekatit 12 Hospital Medical College Addis Ababa, Ethiopia. Int. J. Med. Res. Innovation2025, 1(1), 28-31. doi: 10.11648/j.ijmri.20250101.14
Desta G, Tilahun T, Assefa G, Lebeza Y. Case Report on Rare Presentation of Hepatic Cavernous Haemangioma with Diffuse Hemangiomatosis from Yekatit 12 Hospital Medical College Addis Ababa, Ethiopia. Int J Med Res Innovation. 2025;1(1):28-31. doi: 10.11648/j.ijmri.20250101.14
@article{10.11648/j.ijmri.20250101.14,
  author = {Getachew Desta and Tsion Tilahun and Gezahegn Assefa and Yitayal Lebeza},
  title = {Case Report on Rare Presentation of Hepatic Cavernous Haemangioma with Diffuse Hemangiomatosis from Yekatit 12 Hospital Medical College Addis Ababa, Ethiopia},
  journal = {International Journal of Medical Research and Innovation},
  volume = {1},
  number = {1},
  pages = {28-31},
  doi = {10.11648/j.ijmri.20250101.14},
  url = {https://doi.org/10.11648/j.ijmri.20250101.14},
  eprint = {https://article.sciencepublishinggroup.com/pdf/10.11648.j.ijmri.20250101.14},
  abstract = {Hepatic hemangiomas are the most common liver tumors. They are usually small and asymptomatic, and most often detected incidentally due to the increasing use of imaging modalities. While hemangiomas can occur at any age, they are most commonly found in individuals in their 4th to 6th decade. The majority of haemangiomas are less than 5 cm in size, while those larger than 10 cm are classified as giant hemangiomas. Most of the hemangiomas are solitary, but in 40% of cases, it may involve both right and left lobes and in rare cases, it is associated with diffuse hemangiomatosis. Most hemangiomas are asymptomatic but rarely they may present as an abdominal mass or pain. Large lesions located in the left lobe of the liver may cause pressure effects on adjacent structures such as stomach and bile duct causing nausea leading to anorexia, nausea and jaundice. Rarely large hemangiomas may compress Inferior Vena cava and patients may present with lower limb edema. The diagnosis of hepatic haemangioma mostly depends on cross-sectional imaging. Modalities like CT and MRI are used to diagnose hemangioma and to rule out other differential diagnoses, such as cysts, hepatic adenomas, hepatocellular carcinoma, and distant metastases. Laboratory tests like α-fetoprotein (AFP), carcinoembryonic antigen (CEA), cancer antigen 125 (CA 125) and cancer antigen 19-9 (CA19-9) are important to help rule out malignant lesions. Most hemangiomas do not require any surgical management. However, in patients who present with bothersome symptoms, have a larger size (greater than 10 cm), experience complications like rupture, or have lesions where malignancy cannot be ruled out, surgical treatment should be considered. In our case, the patient presented with compression effects and was diagnosed with a huge hemangioma with hemangiomatous. Resection was performed, and the patient was relieved of symptoms after the surgical intervention.},
 year = {2025}
}
TY  - JOUR
T1  - Case Report on Rare Presentation of Hepatic Cavernous Haemangioma with Diffuse Hemangiomatosis from Yekatit 12 Hospital Medical College Addis Ababa, Ethiopia
AU  - Getachew Desta
AU  - Tsion Tilahun
AU  - Gezahegn Assefa
AU  - Yitayal Lebeza
Y1  - 2025/12/11
PY  - 2025
N1  - https://doi.org/10.11648/j.ijmri.20250101.14
DO  - 10.11648/j.ijmri.20250101.14
T2  - International Journal of Medical Research and Innovation
JF  - International Journal of Medical Research and Innovation
JO  - International Journal of Medical Research and Innovation
SP  - 28
EP  - 31
PB  - Science Publishing Group
SN  - 3070-6319
UR  - https://doi.org/10.11648/j.ijmri.20250101.14
AB  - Hepatic hemangiomas are the most common liver tumors. They are usually small and asymptomatic, and most often detected incidentally due to the increasing use of imaging modalities. While hemangiomas can occur at any age, they are most commonly found in individuals in their 4th to 6th decade. The majority of haemangiomas are less than 5 cm in size, while those larger than 10 cm are classified as giant hemangiomas. Most of the hemangiomas are solitary, but in 40% of cases, it may involve both right and left lobes and in rare cases, it is associated with diffuse hemangiomatosis. Most hemangiomas are asymptomatic but rarely they may present as an abdominal mass or pain. Large lesions located in the left lobe of the liver may cause pressure effects on adjacent structures such as stomach and bile duct causing nausea leading to anorexia, nausea and jaundice. Rarely large hemangiomas may compress Inferior Vena cava and patients may present with lower limb edema. The diagnosis of hepatic haemangioma mostly depends on cross-sectional imaging. Modalities like CT and MRI are used to diagnose hemangioma and to rule out other differential diagnoses, such as cysts, hepatic adenomas, hepatocellular carcinoma, and distant metastases. Laboratory tests like α-fetoprotein (AFP), carcinoembryonic antigen (CEA), cancer antigen 125 (CA 125) and cancer antigen 19-9 (CA19-9) are important to help rule out malignant lesions. Most hemangiomas do not require any surgical management. However, in patients who present with bothersome symptoms, have a larger size (greater than 10 cm), experience complications like rupture, or have lesions where malignancy cannot be ruled out, surgical treatment should be considered. In our case, the patient presented with compression effects and was diagnosed with a huge hemangioma with hemangiomatous. Resection was performed, and the patient was relieved of symptoms after the surgical intervention.
VL  - 1
IS  - 1
ER  -
Desta, G., Tilahun, T., Assefa, G., Lebeza, Y. (2025). Case Report on Rare Presentation of Hepatic Cavernous Haemangioma with Diffuse Hemangiomatosis from Yekatit 12 Hospital Medical College Addis Ababa, Ethiopia. International Journal of Medical Research and Innovation, 1(1), 28-31. https://doi.org/10.11648/j.ijmri.20250101.14
Desta, G.; Tilahun, T.; Assefa, G.; Lebeza, Y. Case Report on Rare Presentation of Hepatic Cavernous Haemangioma with Diffuse Hemangiomatosis from Yekatit 12 Hospital Medical College Addis Ababa, Ethiopia. Int. J. Med. Res. Innovation2025, 1(1), 28-31. doi: 10.11648/j.ijmri.20250101.14
Desta G, Tilahun T, Assefa G, Lebeza Y. Case Report on Rare Presentation of Hepatic Cavernous Haemangioma with Diffuse Hemangiomatosis from Yekatit 12 Hospital Medical College Addis Ababa, Ethiopia. Int J Med Res Innovation. 2025;1(1):28-31. doi: 10.11648/j.ijmri.20250101.14
@article{10.11648/j.ijmri.20250101.14,
  author = {Getachew Desta and Tsion Tilahun and Gezahegn Assefa and Yitayal Lebeza},
  title = {Case Report on Rare Presentation of Hepatic Cavernous Haemangioma with Diffuse Hemangiomatosis from Yekatit 12 Hospital Medical College Addis Ababa, Ethiopia},
  journal = {International Journal of Medical Research and Innovation},
  volume = {1},
  number = {1},
  pages = {28-31},
  doi = {10.11648/j.ijmri.20250101.14},
  url = {https://doi.org/10.11648/j.ijmri.20250101.14},
  eprint = {https://article.sciencepublishinggroup.com/pdf/10.11648.j.ijmri.20250101.14},
  abstract = {Hepatic hemangiomas are the most common liver tumors. They are usually small and asymptomatic, and most often detected incidentally due to the increasing use of imaging modalities. While hemangiomas can occur at any age, they are most commonly found in individuals in their 4th to 6th decade. The majority of haemangiomas are less than 5 cm in size, while those larger than 10 cm are classified as giant hemangiomas. Most of the hemangiomas are solitary, but in 40% of cases, it may involve both right and left lobes and in rare cases, it is associated with diffuse hemangiomatosis. Most hemangiomas are asymptomatic but rarely they may present as an abdominal mass or pain. Large lesions located in the left lobe of the liver may cause pressure effects on adjacent structures such as stomach and bile duct causing nausea leading to anorexia, nausea and jaundice. Rarely large hemangiomas may compress Inferior Vena cava and patients may present with lower limb edema. The diagnosis of hepatic haemangioma mostly depends on cross-sectional imaging. Modalities like CT and MRI are used to diagnose hemangioma and to rule out other differential diagnoses, such as cysts, hepatic adenomas, hepatocellular carcinoma, and distant metastases. Laboratory tests like α-fetoprotein (AFP), carcinoembryonic antigen (CEA), cancer antigen 125 (CA 125) and cancer antigen 19-9 (CA19-9) are important to help rule out malignant lesions. Most hemangiomas do not require any surgical management. However, in patients who present with bothersome symptoms, have a larger size (greater than 10 cm), experience complications like rupture, or have lesions where malignancy cannot be ruled out, surgical treatment should be considered. In our case, the patient presented with compression effects and was diagnosed with a huge hemangioma with hemangiomatous. Resection was performed, and the patient was relieved of symptoms after the surgical intervention.},
 year = {2025}
}
TY  - JOUR
T1  - Case Report on Rare Presentation of Hepatic Cavernous Haemangioma with Diffuse Hemangiomatosis from Yekatit 12 Hospital Medical College Addis Ababa, Ethiopia
AU  - Getachew Desta
AU  - Tsion Tilahun
AU  - Gezahegn Assefa
AU  - Yitayal Lebeza
Y1  - 2025/12/11
PY  - 2025
N1  - https://doi.org/10.11648/j.ijmri.20250101.14
DO  - 10.11648/j.ijmri.20250101.14
T2  - International Journal of Medical Research and Innovation
JF  - International Journal of Medical Research and Innovation
JO  - International Journal of Medical Research and Innovation
SP  - 28
EP  - 31
PB  - Science Publishing Group
SN  - 3070-6319
UR  - https://doi.org/10.11648/j.ijmri.20250101.14
AB  - Hepatic hemangiomas are the most common liver tumors. They are usually small and asymptomatic, and most often detected incidentally due to the increasing use of imaging modalities. While hemangiomas can occur at any age, they are most commonly found in individuals in their 4th to 6th decade. The majority of haemangiomas are less than 5 cm in size, while those larger than 10 cm are classified as giant hemangiomas. Most of the hemangiomas are solitary, but in 40% of cases, it may involve both right and left lobes and in rare cases, it is associated with diffuse hemangiomatosis. Most hemangiomas are asymptomatic but rarely they may present as an abdominal mass or pain. Large lesions located in the left lobe of the liver may cause pressure effects on adjacent structures such as stomach and bile duct causing nausea leading to anorexia, nausea and jaundice. Rarely large hemangiomas may compress Inferior Vena cava and patients may present with lower limb edema. The diagnosis of hepatic haemangioma mostly depends on cross-sectional imaging. Modalities like CT and MRI are used to diagnose hemangioma and to rule out other differential diagnoses, such as cysts, hepatic adenomas, hepatocellular carcinoma, and distant metastases. Laboratory tests like α-fetoprotein (AFP), carcinoembryonic antigen (CEA), cancer antigen 125 (CA 125) and cancer antigen 19-9 (CA19-9) are important to help rule out malignant lesions. Most hemangiomas do not require any surgical management. However, in patients who present with bothersome symptoms, have a larger size (greater than 10 cm), experience complications like rupture, or have lesions where malignancy cannot be ruled out, surgical treatment should be considered. In our case, the patient presented with compression effects and was diagnosed with a huge hemangioma with hemangiomatous. Resection was performed, and the patient was relieved of symptoms after the surgical intervention.
VL  - 1
IS  - 1
ER  -





 Share This Article
 Twitter
 Linked In
 Facebook

 Copy
 Download