
 ,
Fofana Naby,
Sylla Ibrahima Boffa,
Sow Fatoumata Binta,
Diallo Boubacar Alpha,
Diallo Abdourahamane,
Sy Telly
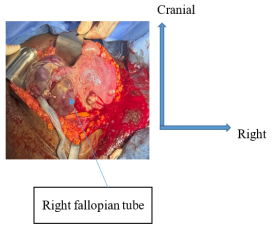
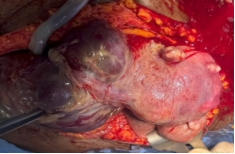
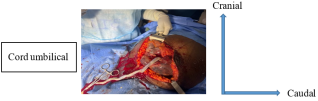
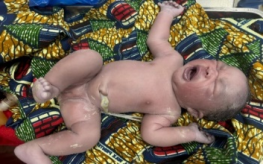
Abdominal pregnancy is a rare form of ectopic pregnancy, in which the fertilized egg implants and develops in the abdominal cavity. Diagnosis and management are difficult. We report the case of a 31 year-old female accountant referred from a local clinic for abdominal pregnancy in the context of 10 years of primary infertility. Despite the presence of suggestive signs and the number of ultrasounds performed, it was not until the 29th and 31st weeks that the diagnosis of abdominal pregnancy was made. We performed a laparotomy at 37 weeks and extracted a healthy live infant. Fetal extraction led to placental intrusion, the after-effects of which were enamelled with haemorrhagic complications originating from the placenta. These led to a right adnexectomy removing the placenta after an unsuccessful attempt to stop the abundant haemorrhage originating from the placenta. The immediate post-operative course was straightforward, with the patient discharged on the third post-operative day and the newborn well. The importance of this case is to underline the delay in making the diagnosis of abdominal pregnancy in our environment, despite the more frequent use of ultrasound and the possibility of full-term delivery of a healthy child. Conclusion: Abdominal pregnancy is a rare event. It is difficult to diagnose, and a conservative attitude to pregnancy is possible.
| Published in | Journal of Gynecology and Obstetrics (Volume 13, Issue 2) |
| DOI | 10.11648/j.jgo.20251302.13 |
| Page(s) | 30-34 |
| Creative Commons |
This is an Open Access article, distributed under the terms of the Creative Commons Attribution 4.0 International License (http://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, distribution and reproduction in any medium or format, provided the original work is properly cited. |
| Copyright |
Copyright © The Author(s), 2025. Published by Science Publishing Group |
Abdominal Pregnancy, Maternity Hospital, Ignace Deen
CHU | University Hospital Center |
PAA | Advanced Abdominal Pregnancy |
SA | Week of Amenorrhea |
IRM | Magnetic Resonance Imaging |
Coll | Collaborators |
| [1] | Serge R N, Mendoua M, Cliford E E, Claude Cyrille Noa N, Stéphane E M, Jackson L: Grossesse Abdominale de Diagnostic Tardif avec Naissance Vivante : À Propos d’un Cas, Health Sci. Dis: 2022; 23, (12)107-110. |
| [2] | Armand KT, Florent FY, Dingom MN, Fouedjio J: Grossesse abdominale: épidémiologique, Diagnostic, Thérapeutique et Pronostique Aspects: un rapport de cas de Yaoundé Hôpital Central (Cameroun), Open Journal of Obstetrics and Gynecology, 2021; 11: 381-390. |
| [3] | Kasongo K. O, Kubiole M, baKaMwiMba, NshoMbo N, KaKinga T, Ilungang H, ITeKe F. R,, KinenKinda K. X, KaKoMa S. Z: Ambiguïté diagnostique d’une grossesse abdominale très prolongée : À propos d’un cas observé à l’Hôpital Général de Référence Jason Sendwe de Lubumbashi en RD Congo. Revue Africaine et Malgache de Recherche Scientifique/Sciences de la Santé, 2021; 1(3). 80-86. |
| [4] | Camara M, Chomba KA, Bah K. H, Diallo M, Sacko A, Bah O A, Baldé T A, BAh A: Révélation à l’imagerie d’une grossesse ectopique dégénérée en lithopédion à Conakry. J Afr Imag Méd 2023; 15(4): 285-290. |
| [5] | Bohoussou E, GUIE P, Saki C, Okon G, Anongba S, TOURE-C K. Diagnostic et prise en charge d’une grossesse abdominale avancée. (Abidjan, Côte d’Ivoire). Diagnosis and management of advanced abdominal. Rev Int Sc Méd 2013; 15(1): 30-32. |
| [6] | Kossa-Ko-Ouakoua GD, Koirokpi A, Wa-Ngogbe SMM, M’Betid-Degana R, Serdouma E, Songrou FKB, Dotte GR, Ngbale NR, Sepou A. Abdominal Pregnancy: About a Case Observed at the Maternity of the Community University Hospital Center, Bangui, Central African Republic. OJOG. 2021; 11(03): 296‑302. |
| [7] | Kangulu IB, Ngoy EK, Cibuabua DK, Ilunga CM, Ndolo AU, Nzaji MK, Mwenze PK. A propos d’un cas de grossesse abdominale très prolongée. Pan African Medical Journal, 2014; 16: 1-4. |
| [8] | Guèye M, Cissé M. L S, Guèye M. K, Guèye M, Diaw H, Moreau. J. C: Difficultés du diagnostic et de prise en charge de la grossesse abdominale : à propos de deux cas diagnostiqués à terme au Centre Hospitalier Régional de Diourbel du Sénégal. clinics in Mother and Child Health 2012; 9: 1-3. Disponible sur: |
| [9] | Akoli Eklou Baudouin BT, Debato T G, Bouassa Davy M K, Kesseh ET, Kouamé Paul K: Grossesse abdominale de datation tardive (à terme) chez une parturiente prise en charge au centre hospitalier universitaire de Bouaké (Côte d’Ivoire), imagerie de la femme, 2021; 31, (4): 172-176. |
| [10] | Rabarikoto H F, Rakotomboahangy T M, Razafindrabia T R, Razafindratasy E, Randriambololona D M A: Grossesse abdominale: les difficultés diagnostiques à travers un cas, Rev. Anesth.-Réanim. Med. Urg. Toxicol. 2018; 10(1): 9-10. |
| [11] | Mengistu Z, Getachew A A, Adefris Mulat: Grossesse abdominale à terme: à propos d’un cas, J Med Case Rep. 2015: |
| [12] | Bang Ntamacka J. A, Ngou Mve Ngouc J. P, Sima Olea B, Sima Zuea A, Mayi Tsongab S. Meyea. |
| [13] | J. F: Grossesse abdominale à Libreville de 1999 à 2009 Abdominal pregnancy in Libreville from 1999 to 2009, Journal de Gynecologie Obstétrique et Biologie de la Reproduction, 2012; 41(1): 83-8. |
| [14] | Siati A, Berrada T, Baidada A, Kharbach A:Grossesse abdominale avec un nouveauné en bonne santé: un nouveau cas, J. médical panafricain, 2019; 34: 35 |
| [15] | Gudu W, Bekele D: Une grossesse abdominale avancée diagnostiquée préopératoirement avec un nouveau-né survivant: un rapport de cas, Journal of Medical Case Reports (2015) 9: 228 |
| [16] | Hounkponou F, Salifou K, Aubin Kotchofa J, Eouani M, Laourou H, Ahouingnan A et all:Abdominal Pregnancy with Live Fetus: A Case Report at Dassa-Glazoue Regional Hospital, Benin 2019, Journal of Gynecology and Obstetrics, 2020; 8(4): 81-84. |
APA Style
Sory, S. I., Naby, F., Boffa, S. I., Binta, S. F., Alpha, D. B., et al. (2025). Full-term Abdominal Pregnancy with Live Child: About a Case in the Service of Gynecology-Obstetrics at the Ignace Deen National Hospital, Conakry / Guinea. Journal of Gynecology and Obstetrics, 13(2), 30-34. https://doi.org/10.11648/j.jgo.20251302.13
ACS Style
Sory, S. I.; Naby, F.; Boffa, S. I.; Binta, S. F.; Alpha, D. B., et al. Full-term Abdominal Pregnancy with Live Child: About a Case in the Service of Gynecology-Obstetrics at the Ignace Deen National Hospital, Conakry / Guinea. J. Gynecol. Obstet. 2025, 13(2), 30-34. doi: 10.11648/j.jgo.20251302.13
AMA Style
Sory SI, Naby F, Boffa SI, Binta SF, Alpha DB, et al. Full-term Abdominal Pregnancy with Live Child: About a Case in the Service of Gynecology-Obstetrics at the Ignace Deen National Hospital, Conakry / Guinea. J Gynecol Obstet. 2025;13(2):30-34. doi: 10.11648/j.jgo.20251302.13
@article{10.11648/j.jgo.20251302.13,
  author = {Sow Ibrahima Sory and Fofana Naby and Sylla Ibrahima Boffa and Sow Fatoumata Binta and Diallo Boubacar Alpha and Diallo Yaya and Diallo Abdourahamane and Sy Telly},
  title = {Full-term Abdominal Pregnancy with Live Child: About a Case in the Service of Gynecology-Obstetrics at the Ignace Deen National Hospital, Conakry / Guinea
},
  journal = {Journal of Gynecology and Obstetrics},
  volume = {13},
  number = {2},
  pages = {30-34},
  doi = {10.11648/j.jgo.20251302.13},
  url = {https://doi.org/10.11648/j.jgo.20251302.13},
  eprint = {https://article.sciencepublishinggroup.com/pdf/10.11648.j.jgo.20251302.13},
  abstract = {Abdominal pregnancy is a rare form of ectopic pregnancy, in which the fertilized egg implants and develops in the abdominal cavity. Diagnosis and management are difficult. We report the case of a 31 year-old female accountant referred from a local clinic for abdominal pregnancy in the context of 10 years of primary infertility. Despite the presence of suggestive signs and the number of ultrasounds performed, it was not until the 29th and 31st weeks that the diagnosis of abdominal pregnancy was made. We performed a laparotomy at 37 weeks and extracted a healthy live infant. Fetal extraction led to placental intrusion, the after-effects of which were enamelled with haemorrhagic complications originating from the placenta. These led to a right adnexectomy removing the placenta after an unsuccessful attempt to stop the abundant haemorrhage originating from the placenta. The immediate post-operative course was straightforward, with the patient discharged on the third post-operative day and the newborn well. The importance of this case is to underline the delay in making the diagnosis of abdominal pregnancy in our environment, despite the more frequent use of ultrasound and the possibility of full-term delivery of a healthy child. Conclusion: Abdominal pregnancy is a rare event. It is difficult to diagnose, and a conservative attitude to pregnancy is possible.
},
 year = {2025}
}
TY  - JOUR
T1  - Full-term Abdominal Pregnancy with Live Child: About a Case in the Service of Gynecology-Obstetrics at the Ignace Deen National Hospital, Conakry / Guinea

AU  - Sow Ibrahima Sory
AU  - Fofana Naby
AU  - Sylla Ibrahima Boffa
AU  - Sow Fatoumata Binta
AU  - Diallo Boubacar Alpha
AU  - Diallo Yaya
AU  - Diallo Abdourahamane
AU  - Sy Telly
Y1  - 2025/04/29
PY  - 2025
N1  - https://doi.org/10.11648/j.jgo.20251302.13
DO  - 10.11648/j.jgo.20251302.13
T2  - Journal of Gynecology and Obstetrics
JF  - Journal of Gynecology and Obstetrics
JO  - Journal of Gynecology and Obstetrics
SP  - 30
EP  - 34
PB  - Science Publishing Group
SN  - 2376-7820
UR  - https://doi.org/10.11648/j.jgo.20251302.13
AB  - Abdominal pregnancy is a rare form of ectopic pregnancy, in which the fertilized egg implants and develops in the abdominal cavity. Diagnosis and management are difficult. We report the case of a 31 year-old female accountant referred from a local clinic for abdominal pregnancy in the context of 10 years of primary infertility. Despite the presence of suggestive signs and the number of ultrasounds performed, it was not until the 29th and 31st weeks that the diagnosis of abdominal pregnancy was made. We performed a laparotomy at 37 weeks and extracted a healthy live infant. Fetal extraction led to placental intrusion, the after-effects of which were enamelled with haemorrhagic complications originating from the placenta. These led to a right adnexectomy removing the placenta after an unsuccessful attempt to stop the abundant haemorrhage originating from the placenta. The immediate post-operative course was straightforward, with the patient discharged on the third post-operative day and the newborn well. The importance of this case is to underline the delay in making the diagnosis of abdominal pregnancy in our environment, despite the more frequent use of ultrasound and the possibility of full-term delivery of a healthy child. Conclusion: Abdominal pregnancy is a rare event. It is difficult to diagnose, and a conservative attitude to pregnancy is possible.

VL  - 13
IS  - 2
ER  -
Gynecology-Obstetrics Department, Ignace Deen National Hospital, Conakry, Guinea
General Surgery Department, Ignace Deen National Hospital, Conakry, Guinea
Gynecology-Obstetrics Department, Ignace Deen National Hospital, Conakry, Guinea
Gynecology-Obstetrics Department, Ignace Deen National Hospital, Conakry, Guinea
Gynecology-Obstetrics Department, Donka National Hospital, Conakry, Guinea
Gynecology-Obstetrics Department, Ignace Deen National Hospital, Conakry, Guinea
Gynecology-Obstetrics Department, Ignace Deen National Hospital, Conakry, Guinea

Information


 Share This Article
 Twitter
 Linked In
 Facebook

 Copy
 Download