Research Article | | Peer-Reviewed

Utilisation of Integrated Child Development Services Among Women Beneficiaries in India

Received: 15 September 2025     Accepted: 28 September 2025     Published: 30 October 2025
Views:       Downloads:
Abstract

Integrated Child Development Services (ICDS) program was introduced in India in 1975 and aims to improve early childhood care and development by offering a full range of early education, nutrition, and health services. Addressing the persistent issues of socioeconomic and geographic disparities in service access is essential to ICDS's success. This study focuses on understanding the extent and patterns of ICDS service use among mothers during pregnancy and lactation across different social categories and residential settings, using data from the National Family Health Survey-5 (2019–2021). The findings indicate that approximately 71% of pregnant women reported using at least one ICDS service, a figure that is only marginally higher by about 4 percentage points than that for breastfeeding mothers. However, considerable state-level variations remain evident, with the uptake of nutrition-related and health education services particularly low in several regions. Moreover, the analysis highlights pronounced inequalities across socioeconomic groups, pointing to systemic challenges in ensuring inclusivity within the program. Women from marginalized social groups, lower-income households, and rural areas continue to face barriers in accessing the full spectrum of services. These findings underscore the urgent need for targeted interventions, context-specific strategies, and stronger monitoring mechanisms to bridge existing gaps and enhance the impact of ICDS in promoting maternal and child health outcomes across India.

Published in Social Sciences (Volume 14, Issue 5)
DOI 10.11648/j.ss.20251405.19
Page(s) 560-568
Creative Commons

This is an Open Access article, distributed under the terms of the Creative Commons Attribution 4.0 International License (http://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, distribution and reproduction in any medium or format, provided the original work is properly cited.

Copyright

Copyright © The Author(s), 2025. Published by Science Publishing Group

Keywords

ICDS Utilisation, Pregnant & Breastfeeding Women, India

1. Introduction
The Government of India has launched the Integrated Child Development Services (henceforth ICDS) program on dated 2nd October 1975. . The integrated Child Development Services programme is centrally sponsored scheme implemented by state governments and union territories and aim to address malnutrition and health problems among children and mothers, as well as promote their overall development and well-being. The ICDS includes six components that includes supplementary nutrition, health check-up, pre-school education, nutrition and health education and immunization. . The ICDS programs function through the supply chain from district to village level via a Child Development Project Officer (CDPO) located at the block level, which covers around 100000 population in urban and 50000 people in the rural area. There are around 100 ICDS centres (Anganwadi) in each rural and urban area and 50 Anganwadi centres in the tribal area. However, the actual number of Anganwadi centres (AWCs) may differ depending on the locality's geographical location and population density . The recent round of National Family Health Survey (NHFS) 2019-21 show that, every third child among 0–59-month age suffered from some type of nutrition deficiency (stunting, wasting, underweight) . Government of India launched another initiate national nutritional mission in 2017 (POSHAN Abhiyan) to reduce the child undernutrition . The ICDS struggling with some of the social norms and challenges that includes caste-based discriminations, economic inequalities, geographical terrain . Diwakar and Mamgain found that, there has been a government failure to promote SC cook in ICDS due to the strong opposition from other caste groups . Other issues in ICDS unskilled Anganwadi workers (AWW), lack of infrastructure and financial allocation indirectly restricting the performance of ICDS . Study by Kandpal shows that utilization of ICDS reduced child undernutrition . However very few studies have shown utilization of ICDS by women beneficiaries. Majority of the study focus on ICDS utilization by child but pregnant and breastfeeding women are also crucial components of ICDS programme in India. To reduced undernutrition among the children it very crucial to utilised ICDS services by pregnant and breastfeeding women. Saiyed and Seshadri (2000) argued that, full utilization of ICDS services significantly led to improvement in child nutrition status . Low-cost changes can make to existing ICDS centres more effective and significantly improve health care of Preschool children as well as mother . The utilization of ICDS is affected by mother’s education, caste and economic status of the household . The village level ICDS center increase maternity care to pregnant and breastfeeding women’s .
2. Methods and Materials
Data Sources
The study used fifth round of Indian National Family Health Survey (NFHS) conducted in 2019-21. The International Institute for Population Sciences Mumbai India, was the key agency for facilitation of the survey. The survey followed two stage sample design in most of the rural areas and three stage sampling design in most of the urban area and cover more than 99% of population. The NFHS collect data on fertility, reproductive health, family planning and other health indicators of women and Under-five children.
Sample Size
The survey used two-stage stratified sample design. Villages served as the Primary Sampling Units (PSUs) in rural regions, while Census Enumeration Blocks (CEBs) were selected for urban regions. Households in both urban and rural areas were chosen for the second phase. We used the NFHS-5, 2019–21 women's file for this study. 724,115 women between the ages of 15 and 49 provided data for the survey. Among them 200386 women who were involved with ICDS were selected for this study.
Statistical Analysis
Using ICDS service is common among the under five children in India but utilisation of ICDS service by Pregnant and Breastfeeding women’s is not usually up to the expectation level. The study's use variable was the usage of ICDS services by women beneficiaries with binary outcomes yes or no. With the dichotomous outcome of ICDS service utilisation use (yes or no), we used logistic regression model to determine the ICDS services utilisation by the women beneficiaries in India. Majority of the study shows that social background, education and wealth are the main important factor that determine ICDS utilisation by the beneficiaries like women and children. The study's primary explanatory factor is caste (SC, ST, OBC, Other), religion (Hindu, Muslim, Others), education level (illiterate, primary, secondary, Higher and above), residences (rural, urban), wealth index (poor, middle, rich).
3. Result
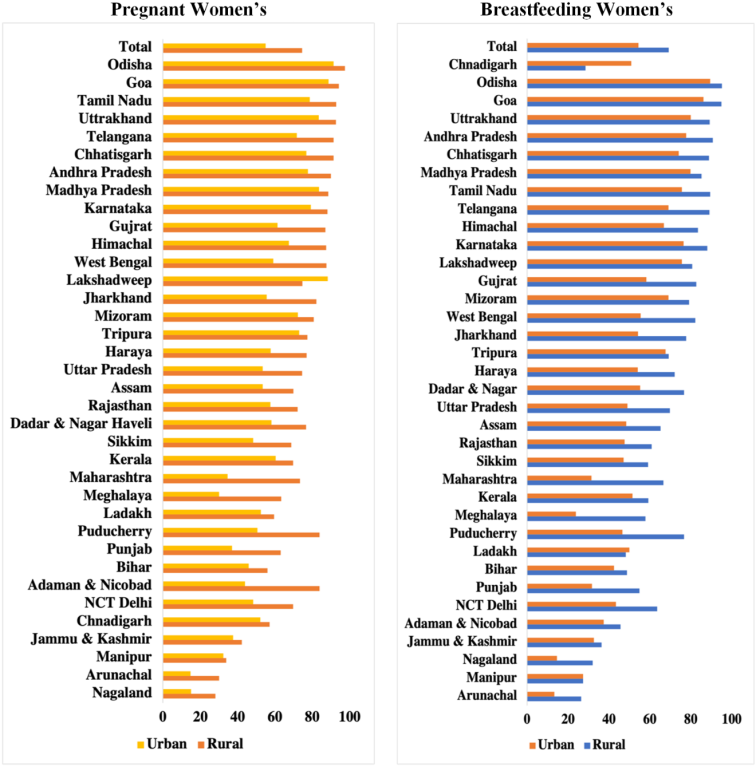
Across states Odisha had the highest percentage of ICDS services utilization among pregnant women in rural (95.21%) and urban (89.45%). The lowest utilization was in Arunachal Pradesh urban (13.28%) and rural (26.36%) respectively. The figure also shows that Manipur, Nagaland, Jammu and Kashmir and Andaman and Nicobar Island had less than 50% utilization of ICDS services in urban and rural among pregnant women’s. Across states Odisha had the highest percentage of ICDS services utilization among breastfeeding women in rural (97.41%) and urban (91.45%). The lowest utilization was in Nagaland rural (15.08%) and rural (28.32%) respectively. The figure also shows that Arunachal Pradesh, Manipur, Jammu and Kashmir had less than 50% utilization of ICDS services in urban and rural among breastfeeding women’s.
Figure 1. Percentage of State-wise utilization of ICDS service by Pregnant and Breastfeeding women in India 2019-21.
Table 1 shows services utilization (any services) by pregnant women was about more than 15 percentage higher for rural areas (74.19%) than urban areas (58.43%) of pregnant women reported to utilized during the pregnancy. Even while breastfeeding same pattern had observed between rural (69.19%) and urban (54.45%) all over India in any services utilization.
The rural urban gap in services utilization do not shows any major variation in supplementary food, health check-ups and nutrition education services among the pregnant and breastfeeding women in India. Among all services under ICDS supplementary food was higher among pregnant women in both areas rural (95.54%) and urban (93.40%) respectively).
Table 1. Percentage utilization of ICDS services by women (during pregnancy and while breastfeeding) in India, NFHS-5, 2021.

Service Utilization

Rural (N)

Urban (N)

Total (N)

Pregnant Women

Supplementary Food

95.54

131634

93.40

25760

95.18

157394

Health Checkups

88.00

24320

88.18

24320

88.03

145576

Nutrition Education

83.72

107462

86.15

22140

83.75

138497

Any Services

74.19

137784

58.43

27579

71.0

165363

Breastfeeding Women

Supplementary Food

96.8

124250

95.23

24472

96.53

148722

Health Checkups

86.40

(110901

87.71

22541

86.62

133442

Nutrition Education

83.72

107462

86.15

22140

84.12

129602

Any Services

69.12

128362

54.45

25699

66.14

154061

The similar pattern had observed among breastfeeding women in rural (96.8%) and urban (95.23%) with respect to supplementary food service. With respect to health check-ups and nutrition education services more than eight percent utilization had reported by pregnant as well as breastfeeding women in both rural and urban areas.
Women from SC household had higher utilization of ICDS among pregnant and breastfeeding women both in rural and urban area (Table 2).
Table 2. Percentage utilization of ICDS services by women based on background characteristics (during pregnancy and while breastfeeding) in India, NFHS-5, 2021.

Background Characteristics

Rural (N)

Urban (N)

Total (N)

Pregnant Woman’s

Social Group

SC

78.26

30433

64.78

5804

75.73

36237

ST

71.42

30056

54.33

2736

69.6

32792

OBC

76.35

53142

63.76

12429

73.6

65571

Other

68.71

24 153

48.21

6610

62.96

30763

Religion

Hindu

78.9

10924

60.97

19874

75.48

129115

Muslim

64.04

15 202

55.99

5576

61.98

20778

Christian

55.04

8630

47.3

1500

53.74

10130

Sikh

62.91

2078

41.14

325

58.71

2403

Buddhist

59.81

51158

46.07

164

57.68

1322

Other

56.56

1475

28.06

140

51.98

1615

Wealth Quintile

Poorest

72.41

44301

64.31

1429

72.12

45730

Poor

74.35

37165

63.33

2836

73.45

40001

Middle

77.37

28222

63.01

5423

74.63

33645

Richer

75.32

18889

62.66

8782

70.83

27671

Richest

70.83

9207

50.96

9109

59.32

30874

Education

Illiterate

70.85

32485

59.19

3171

69.63

35656

Primary

74.42

19182

63.45

2733

72.85

21915

Secondary

76.05

72306

61.81

15317

73.1

87623

Higher

72.64

13811

49.85

6358

63.49

20169

Family Type

Nuclear

71.9

52161

58.64

10913

69.19

63074

Joint

75.66

85623

58.3

16666

72.16

102289

Total

74.19

137784

58.43

27579

71.00

165363

Breastfeeding Woman’s

Social Group

SC

72.21

28080

59.58

5338

69.98

33418

ST

67.69

28485

50.48

2542

65.85

31027

OBC

71.21

49564

59.99

11694

68.76

61258

Other

63.25

22233

44.68

6125

58.04

28358

Religion

Hindu

73.69

102034

56.94

18560

70.5

120594

Muslim

58.92

13985

53.22

5208

57.25

19193

Christian

51.63

8096

43.58

1382

50.28

9478

Sikh

54.71

1807

34.81

275

50.87

2082

Buddhist

54.91

1063

41.85

149

52.87

1212

Other

52.8

1377

25.05

125

48.34

1502

Wealth Quintile

Poorest

67.41

41245

60.49

1344

67.17

42589

Poor

69.03

34504

59.36

2658

68.23

37162

Middle

72.41

26413

58.92

5071

69.84

31484

Richer

70.76

17745

58.5

8200

66.37

25945

Richest

65.05

8455

47.14

8426

54.68

16881

Education

Illiterate

65.21

29900

54.83

2937

64.12

32837

Primary

69.11

17813

57.65

2483

67.47

20296

Secondary

71.23

67725

58.02

14379

68.5

82104

Higher

67.98

12924

46.26

5900

59.26

18824

Family Type

Nuclear

67.26

48796

54.65

10170

54.45

25699

Joint

70.3

79566

54.32

15529

69.12

128362

Total

69.12

128362

54.45

25699

66.14

154061

Note: SC: Scheduled Caste, ST: Scheduled Tribe, OBC: Other backward Class
At national level also (75.7%) percent pregnant and 70 percent breastfeeding women received benefits of ICDS among the SC social group women’s. There are 12 percentage gaps between lowest and highest utilization of ICDS among pregnant women in social group at national level. Similar 10 percentage gaps had observed among breastfeeding women also. The same pattern had been observed in rural and urban residence among pregnant and breastfeeding women’s. Across the religion groups Hindu pregnant women highest rural (78.9%), urban (61%) and total (75.5%). Same pattern had observed among breastfeeding women rural (73.7%), urban (57%) and total (70.5%). Other than Hindu religion pregnant women show lower utilization of ICDS services lies in range of (51- 62%) at total and rural (54-64%). In urban area 27 percentage difference had observed from 28 percent to 56 percent. In case of breastfeeding women similar pattern observe highest utilization in rural (73.7%), urban (57%) and total (70.5%). Whereas Muslim (57%), Buddhist (52.9%), Christian and Sikh (50%), and Other (48.3%). More than 50 percent of pregnant women other than Hindu religion utilizing services of ICDS in rural areas. While only Muslim breastfeeding women shows more than 50 percent of ICDS utilization along with Hindu women. Rest of Christian (43.6%), Buddhist (41.9%), Sikh (34.8%) and Other (25%) breastfeeding women were utilizing services of ICDS. Across all wealth quintile more than 70 percent of ICDS utilization among pregnant women at national and in rural areas, while in urban area it goes down to 61 precent. More than 70 percent of breastfeeding women used ICDS services by middle and richer quintile and rest of less than 70 percent in rural areas. Lower utilization of ICDS services shown at national level and urban area among breastfeeding women as compare to rural area. In level of education similar pattern observed with respect to rural area more than 70 percent of ICDS services utilization by pregnant women, whereas in urban primary educated had highest (63.4%) and lowest higher educated (49.8%) pregnant women. Among the breastfeeding women the utilization of ICDS services increase from illiterate (65.2%) to secondary (71.2%) and it decline to (68%) am among higher educated women in rural area. Similar pattern had observed at national and urban area among the breastfeeding women. Across family in joint types family higher utilization of ICDS services had observed in both of pregnant (72.2%) and breastfeeding (69.1%) women at national, (75.6%) and (70.3%) in rural areas. Whereas in urban area nuclear family shows higher (58.6%) pregnant and (54.6%) among breastfeeding women.
Table 3. Odds Ratio of Utilisation of ICDS services by Pregnant and Breastfeeding women 2019-21.

Characteristics

Pregnant Women

Breastfeeding Women

Caste Other @

Nutrition Service (AOR)

Health Check (AOR)

Counselling (AOR)

Nutrition Service (AOR)

Health Check (AOR)

Counselling (AOR)

SC

1.49***

1.55***

1.47***

1.15***

1.26***

1.2***

ST

1.86***

1.82***

1.94***

2.14***

1.45***

1.63***

OBC

1.35***

1.49***

1.42***

1.02

1.33***

1.25***

Religion Other @

Hindu

3.17***

3.93***

3.52***

1.14

2.86***

2.22***

Muslim

2.15***

2.42***

2.29***

1.06

1.94***

1.63***

Christian

1.01

.70***

.78***

1.37

.52***

.59***

Sikh

1.66***

1.80***

1.66***

1.37

1.59***

1.31***

Buddhist

1.25***

1.42***

1.33***

1.75

1.51***

1.44***

wealth Rich@

Poor

1.09

.91***

.86***

1.15***

.74***

.69***

Middle

1.21***

1.14***

1.12***

1.31***

0.94

0.94

Residence Urban@

Rural

1.90**

1.75***

1.65***

1.33***

0.96

.92***

Education Illiterate @

Primary

1.32***

1.24***

1.25***

1.32***

1.00

1.05

Secondary

1.40**

1.25***

1.32***

1.58***

1.00

1.13***

Higher

1.02

.930***

0.99

1.20***

.91**

1.00

@Reference category, AOR Adjusted odds ratio, ***p < 0.01.
The adjusted odds ratios (AORs) from logistic regression models that look at the factors influencing pregnant and lactating women's use of ICDS services are shown in (Table 3). Supplementary nourishment, health examinations, and counselling are among the services that have been examined. Caste, religion, wealth, type of habitation, and level of education are used to display the results. Caste was found to be a significant predictor of ICDS use. Compared to the reference category (Others), women from Scheduled Castes (SC) had a much higher likelihood of utilizing services. SC mothers were 1.55 times more likely to have health checkups and 1.49 times more likely to receive supplemental nutrition during pregnancy. With 1.15 and 1.26 times higher likelihood of receiving nutrition and health check-ups, respectively, breastfeeding mothers showed a similar pattern. Scheduled Tribe (ST) women were most likely to use ICDS services. Breastfeeding ST women were more than twice as likely to receive supplemental nutrition (AOR = 2.14, p<0.001), and pregnant ST women were almost twice as likely to seek counselling services (AOR = 1.94, p<0.001). While their advantage waned for nursing nutrition, when no discernible difference was found, in (OBC) also demonstrated significantly better likelihood of obtaining services during pregnancy. In case religion Hindu women were more than three times as likely to receive nutrition (AOR = 3.17, p<0.001) and health check-ups (AOR = 3.93, p<0.001), indicating the highest likelihood of service consumption during pregnancy. During the breastfeeding phase, this benefit for health examinations (AOR = 2.86, p<0.001) and counselling (AOR = 2.22, p<0.001). Additionally, Muslim women were more likely than other women to use services during pregnancy, with 2.42 times higher odds of health checkups and 2.29 times higher odds of counselling. Breastfeeding women continued to have a usage advantage, albeit it was less noticeable. On the other hand, Christian women consistently reported lesser use. The likelihood of Christian women getting health checkups (AOR = 0.70, p<0.001) and counselling (AOR = 0.78, p<0.001) was significantly lower during pregnancy. The likelihood of receiving counselling (AOR = 0.59, p<0.001) and health examinations (AOR = 0.52, p<0.001) was approximately half for breastfeeding women. Though the impact varied by service, Sikh pregnant women nutrition, counselling services equally (AOR =1.55, p<0.001) and health check-up (AOR =1.55, p<0.001), whereas breastfeeding women health check (AOR =1.59, p<0.001), counselling (AOR =1.31, p<0.001) time higher. Buddhist women generally used more services than the Other category, especially during pregnancy. Compared to pregnant women from wealthy homes, those from middle-income households were more likely to use ICDS services. Poor women were more likely to seek counselling (AOR = 0.86, p<0.001) and health examinations (AOR = 0.91, p<0.001). Poor families were significantly less likely to get health check-ups (AOR = 0.74, p<0.001) and counselling (AOR = 0.69, p<0.001), but much more likely to receive supplemental nutrition (AOR = 1.15, p<0.001) for breastfeeding women. Pregnant women in rural areas were almost twice as likely to receive health checkups (AOR = 1.75, p<0.001) and supplemental nutrition (AOR = 1.90, p<0.01) as their urban counterparts. Among nursing moms, rural mothers remained significantly more likely to obtain supplemental nutrition (AOR = 1.33, p<0.001). Compared to illiterate women, pregnant women with elementary and secondary education had consistently greater likelihood of using all services. The likelihood of receiving nutrition was 1.40 times higher for women with a secondary education (p<0.01), and the likelihood of receiving counselling was 1.32 times higher (p<0.001). Higher education, however, displayed weaker or even adverse correlations.
Health checkup was lower among pregnant women with higher levels of education (AOR = 0.93, p<0.001). While the nutrition services primary (AOR = 1.32, p<0.001), secondary (AOR = 1.58, p<0.001) Higer education (AOR = 0.86, p<0.001) continued to improve among nursing mothers.
4. Discussion
Significant differences in the use of ICDS services by pregnant and lactating women in India are highlighted by this study. As a result of ICDS outreach's rural concentration, service acceptance was often higher in rural than in urban regions. Concerns regarding flaws in the program's conception and execution are raised by the fact that a sizable percentage of eligible women are still not receiving ICDS benefits . These results imply that although while ICDS is widely used, its real reach is still below that of universal coverage.
Additionally, differences in stage-wise consumption were noted. Utilization levels were lower than anticipated in states like Uttar Pradesh and Bihar, which have a high burden of maternal and child health issues. This suggests that local implementation is lacking. Additionally, although more people used supplemental nutrition services, much less was used for other components, such as health examinations, counselling, and nutrition instruction. This pattern suggests a significant dependence on dietary supplements and a relative disregard for the wider health and educational roles of ICDS . There were also noticeable disparities by social group. Higher use rates were observed by OBC and Scheduled Caste women, indicating that ICDS is at least partially successful in reaching these underprivileged groups. In spite of their lower maternal health indicators, Scheduled Tribe women continued to use the program at a relatively low rate. This suggests that ICDS coverage is problematic in isolated and tribally populated areas . There were notable differences in religion. Utilization was significantly lower among all other religious groups except Hindu women, which can be due to variations in cultural acceptance, accessibility, or awareness of ICDS programs. Similarly, because they might rely on private health systems, women from affluent households both in urban and rural areas were less likely to use ICDS services, especially supplemental nutrition. However, wealthier groups continued to have higher access to counselling and health examinations, highlighting the influence of socioeconomic position on service selection. The use of ICDS was similarly influenced by educational attainment. Primary and secondary school-educated women were more likely to use ICDS services, demonstrating the beneficial influence of basic education in encouraging health-seeking behaviours. Higher educated women, on the other hand, were less dependent on ICDS, most likely as a result of their choice for private healthcare. Last but not least, structural obstacles including inadequate facilities, a lack of space, subpar services, and a lack of variety in supplemental nutrition were also noted as potential causes of the decreased uptake of ICDS . The efficiency of ICDS is weakened by these programmatic issues, which also contribute to the observed discrepancies in utilization.
5. Conclusion
The usage of ICDS services by Indian women is examined in this study according to a variety of criteria, including caste, income, education, and religion. The survey suggests that Indian women in the wealthier and better-educated groups might use services more effectively. Indicators of mother and child health would improve if ICDS services were improved and approached holistically, encompassing early childcare, nutrition and health education, and nutrition supplements. Furthermore, it is imperative that area-specific services prioritize improving the skills of Anganwadi workers (AWWs) in both rural and urban areas, enhancing infrastructure, promoting community involvement, and addressing local cultural issues would provide a solid foundation for the smooth, long-term operation of ICDS services. Finally, increasing the accessibility of data on particular service-related subjects, such as AWW education and skill levels and reasons for not using ICDS benefits, may provide useful information for programming.
Abbreviations

AWS

Anganwadi Worker

CDPO

Child Development Project Officer

ICDS

Integrated Child Development Services

SC

Scheduled Caste

ST

Scheduled Tribe

OBC

Other Backward Class

Author Contributions
Sagar Dhirasrao Ingle: Conceptualization, Data curation, Formal Analysis, Methodology, Software, Visualization, Writing – original draft, Writing – review & editing
Dewaram Abhiman Nagdeve: Conceptualization, Investigation, Methodology, Resources, Supervision, Validation, Writing – review & editing
Conflicts of Interest
The authors declare no conflicts of interest.
References
[1] Aayog, N. I. T. I. (2015). A quick evaluation study of Anganwadis under ICDS. Programme Evaluation Organisation. New Delhi: Government of India.
[2] Gupta, A., Gupta, S. K., & Nongkynrih, B. (2013). Integrated child development services (ICDS) scheme: a journey of 37 years. Indian journal of community health, 25(1), 77-81.
[3] Chudasama, R. K., Kadri, A. M., Verma, P. B., Vala, M., Rangoonwala, M., & Sheth, A. (2015). Evaluation of nutritional and other activities at Anganwadi centers under integrated child development services program in different districts of Gujarat, India. J Med NutrNutraceut, 4, 101-6.
[4] International Institute for Population Sciences (IIPS) and ICF (2019-21). National Family Health Survey.
[5] Aayog, N. I. T. I. (2017). National nutrition strategy. Government of India.
[6] Thorat, S., & Sadana, N. (2009). Discrimination and children's nutritional status in India. IDS Bulletin, 40(4), 25-29.
[7] Mamgain, R. P., & Diwakar, G. D. (2012). Elimination of identity‐based discrimination in food and nutrition programmes in India. IDS Bulletin, 43, 25-31.
[8] Davey, A., Davey, S., & Datta, U. (2008). Perception regarding quality of services in urban ICDS blocks in Delhi. Indian journal of public health, 52(3), 156-158.
[9] Kandpal, E. (2011). Beyond average treatment effects: distribution of child nutrition outcomes and program placement in India’s ICDS. World Development, 39(8), 1410-1421.
[10] Saiyed, F., & Seshadri, S. (2000). Impact of the integrated package of nutrition and health services. The Indian Journal of Pediatrics, 67(5), 322-328.
[11] Kerber, K. J., de Graft-Johnson, J. E., Bhutta, Z. A., Okong, P., Starrs, A., & Lawn, J. E. (2007). Continuum of care for maternal, newborn, and child health: from slogan to service delivery. The Lancet, 370(9595), 1358-1369.
[12] Jain, M. (2015). India’s struggle against malnutrition—is the ICDS program the answer? World Development, 67, 72-89.
[13] Shariff, A., & Singh, G. (2002). Determinants of maternal health care utilisation in India: evidence from a recent household survey (No. 85). New Dehli: National Council of Applied Economic Research.
[14] Lokshin, M., Das Gupta, M., Gragnolati, M., & Ivaschenko, O. (2005). Improving child nutrition? The integrated child development services in India. Development and Change, 36(4), 613-640.
[15] Deolalikar, A. B. (2005). Attaining the millennium development goals in India: reducing infant mortality, child malnutrition, gender disparities and hunger-poverty and increasing school enrollment and completion (pp. xix+-139).
[16] Agnihotri, S. P., Pandey, D. N., & Nandan, D. (1984). The impact of rural health services in Agra sub division. Indian Journal of Public Health, 28(1), 25-29.
[17] Jain, M., Nandan, D., & Misra, S. K. (2006). Qualitative assessment of health seeking behaviour and perceptions regarding quality of health care services among rural community of district Agra. Indian Journal of community medicine, 31(3), 140.
Cite This Article
  • APA Style

    Ingle, S. D., Nagdeve, D. A. (2025). Utilisation of Integrated Child Development Services Among Women Beneficiaries in India. Social Sciences, 14(5), 560-568. https://doi.org/10.11648/j.ss.20251405.19

    Copy | Download

    ACS Style

    Ingle, S. D.; Nagdeve, D. A. Utilisation of Integrated Child Development Services Among Women Beneficiaries in India. Soc. Sci. 2025, 14(5), 560-568. doi: 10.11648/j.ss.20251405.19

    Copy | Download

    AMA Style

    Ingle SD, Nagdeve DA. Utilisation of Integrated Child Development Services Among Women Beneficiaries in India. Soc Sci. 2025;14(5):560-568. doi: 10.11648/j.ss.20251405.19

    Copy | Download

  • @article{10.11648/j.ss.20251405.19,
      author = {Sagar Dhirasrao Ingle and Dewaram Abhiman Nagdeve},
      title = {Utilisation of Integrated Child Development Services Among Women Beneficiaries in India
    },
      journal = {Social Sciences},
      volume = {14},
      number = {5},
      pages = {560-568},
      doi = {10.11648/j.ss.20251405.19},
      url = {https://doi.org/10.11648/j.ss.20251405.19},
      eprint = {https://article.sciencepublishinggroup.com/pdf/10.11648.j.ss.20251405.19},
      abstract = {Integrated Child Development Services (ICDS) program was introduced in India in 1975 and aims to improve early childhood care and development by offering a full range of early education, nutrition, and health services. Addressing the persistent issues of socioeconomic and geographic disparities in service access is essential to ICDS's success. This study focuses on understanding the extent and patterns of ICDS service use among mothers during pregnancy and lactation across different social categories and residential settings, using data from the National Family Health Survey-5 (2019–2021). The findings indicate that approximately 71% of pregnant women reported using at least one ICDS service, a figure that is only marginally higher by about 4 percentage points than that for breastfeeding mothers. However, considerable state-level variations remain evident, with the uptake of nutrition-related and health education services particularly low in several regions. Moreover, the analysis highlights pronounced inequalities across socioeconomic groups, pointing to systemic challenges in ensuring inclusivity within the program. Women from marginalized social groups, lower-income households, and rural areas continue to face barriers in accessing the full spectrum of services. These findings underscore the urgent need for targeted interventions, context-specific strategies, and stronger monitoring mechanisms to bridge existing gaps and enhance the impact of ICDS in promoting maternal and child health outcomes across India.
    },
     year = {2025}
    }
    

    Copy | Download

  • TY  - JOUR
    T1  - Utilisation of Integrated Child Development Services Among Women Beneficiaries in India
    
    AU  - Sagar Dhirasrao Ingle
    AU  - Dewaram Abhiman Nagdeve
    Y1  - 2025/10/30
    PY  - 2025
    N1  - https://doi.org/10.11648/j.ss.20251405.19
    DO  - 10.11648/j.ss.20251405.19
    T2  - Social Sciences
    JF  - Social Sciences
    JO  - Social Sciences
    SP  - 560
    EP  - 568
    PB  - Science Publishing Group
    SN  - 2326-988X
    UR  - https://doi.org/10.11648/j.ss.20251405.19
    AB  - Integrated Child Development Services (ICDS) program was introduced in India in 1975 and aims to improve early childhood care and development by offering a full range of early education, nutrition, and health services. Addressing the persistent issues of socioeconomic and geographic disparities in service access is essential to ICDS's success. This study focuses on understanding the extent and patterns of ICDS service use among mothers during pregnancy and lactation across different social categories and residential settings, using data from the National Family Health Survey-5 (2019–2021). The findings indicate that approximately 71% of pregnant women reported using at least one ICDS service, a figure that is only marginally higher by about 4 percentage points than that for breastfeeding mothers. However, considerable state-level variations remain evident, with the uptake of nutrition-related and health education services particularly low in several regions. Moreover, the analysis highlights pronounced inequalities across socioeconomic groups, pointing to systemic challenges in ensuring inclusivity within the program. Women from marginalized social groups, lower-income households, and rural areas continue to face barriers in accessing the full spectrum of services. These findings underscore the urgent need for targeted interventions, context-specific strategies, and stronger monitoring mechanisms to bridge existing gaps and enhance the impact of ICDS in promoting maternal and child health outcomes across India.
    
    VL  - 14
    IS  - 5
    ER  - 

    Copy | Download

Author Information