
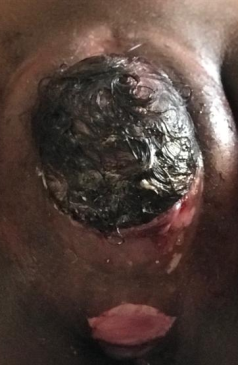
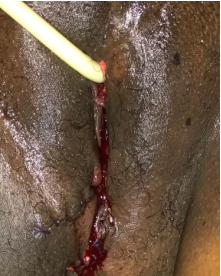
Introduction: Ghana continues to grapple with the complex issue of female genital mutilation/cutting (FGM/C), a practice marked by notable regional disparities. Driven by multifaceted motivations, including deeply ingrained cultural values, perceived benefits for the girl child, and efforts to curb sexual promiscuity, FGM/C poses significant health risks. This article presents a near-miss case of a 19-year-old woman who experienced prolonged labour and postpartum haemorrhage (PPH) due to complications arising from FGM/C. Case Presentation: A 19-year-old woman with a history of FGM/C presented with prolonged labour and PPH. Physical examination revealed Type 3 FGM/C (infibulation) complicated by multiple perineal and vaginal tears. A vaginal delivery was facilitated by bilateral episiotomy, and the episiotomies and lacerations were subsequently repaired. Due to significant blood loss from PPH, the patient received 2 units of whole blood. Fortunately, the mother recovered physically well, with normal urinary and faecal continence, and the baby pair is doing well. However, true recovery in this case will require an enabling environment and supportive care to address her psychosocial needs. Conclusion: We strongly recommend a comprehensive approach to eradicate FGM/C, including awareness creation, strengthening anti-FGM/C laws, and providing a supportive environment that promotes the physical, psychological, and social well-being of victims. Collective efforts by all stakeholders are crucial to achieving this goal and ensuring that women and girls are protected from the harmful effects of FGM/C.
| Published in | World Journal of Medical Case Reports (Volume 7, Issue 1) |
| DOI | 10.11648/j.wjmcr.20260701.13 |
| Page(s) | 9-13 |
| Creative Commons |
This is an Open Access article, distributed under the terms of the Creative Commons Attribution 4.0 International License (http://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, distribution and reproduction in any medium or format, provided the original work is properly cited. |
| Copyright |
Copyright © The Author(s), 2026. Published by Science Publishing Group |
Maternal Near-Miss, Female Genital Mutilation or Cutting, Prolonged Labour, Savannah Region, Ghana
FGM | Female Genital Mutilation |
FGM/C | Female Genital Mutilation / Cutting |
PPH | Postpartum Haemorrhage |
SFH | Symphio-Fundal Height |
WHO | World Health Organisation |
| [1] | WHO, Female genital mutilation. WHO-RHR, 2019. 19.19. © World Health Organization 2019. |
| [2] | UNICEF, United Nations Children’s Fund, Female Genital Mutilation/ Cutting: A global concern, 2016. |
| [3] | Sipsma, H. L., et al., Female genital cutting: current practices and beliefs in western Africa. Bull World Health Organ, 2012. 90(2): p. 120-127F. |
| [4] | Yoder, P. S., S. Wang, and E. Johansen, Estimates of Female Genital Mutilation/ Cutting in 27 African Countries and Yemen. Studies in Family Planning 2013. 44(2): p. 189 - 204. |
| [5] | Oduro, A. R., et al., Trends In The Prevalence Of Female Genital Mutilation And Its Effect On Delivery Outcomes In The Kassena-Nankana District Of Northern Ghana. Ghana Medical Journal, 2006. 40(3). |
| [6] | Llamas, J. Female Circumcision: The History, the Current Prevalence and the Approach to a Patient. 2017. |
| [7] | Alhassan, A. R. and J. N. Anyinzaam-Adolipore, Female Genital Mutilation in Ghana: Prevalence and Socioeconomic Predictors. BioMed Research International, 2021. 2021. |
| [8] | Thompson Reuters Foundation and TrustLaw, GHANA: THE LAW AND FGM September 2018, in 28 Too Many FGM...lets end it. 2021. |
| [9] | Dorkenoo, E., Cutting the Rose. Female Genital Mutilation: The Practice and its Prevention. The European Journal of Women’s Studies Copyright @ SAGE Publications (London, Thousand Oaks and New Delhi), 1996. 3: p. 315-328. |
| [10] | Sakeah, E., et al., Prevalence and factors associated with female genital mutilation among women of reproductive age in the Bawku municipality and Pusiga District of northern Ghana. BMC Womens Health, 2018. 18(1): p. 150. |
| [11] | Sakeah, E., et al., Persistent female genital mutilation despite its illegality: Narratives from women and men in northern Ghana. PLoS One, 2019. 14(4): p. e0214923. |
| [12] | Onah, C. K., et al., Factors associated with the practice of and intention to perform female genital mutilation on a female child among married women in Abakaliki Nigeria. BMC Womens Health, 2023. 23(1): p. 376. |
| [13] | Sheikha, M. M., J. J. Cheptum, and I. G. Magetoc, Factors Linked to Female Genital Mutilation Practice Among Women Living In Alungu Village of Mandera County, Kenya. East African Health Research Journal, 2023. 7(1). |
| [14] | Ahinkorah, B. O., Factors associated with female genital mutilation among women of reproductive age and girls aged 0-14 in Chad: a mixed-effects multilevel analysis of the 2014-2015 Chad demographic and health survey data. BMC Public Health, 2021. 21(1): p. 286. |
| [15] | El-Dirani, Z., et al., Factors associated with female genital mutilation: a systematic review and synthesis of national, regional and community- based studies. BMJ Sex Reprod Health, 2022. 48: p. 169–178. |
| [16] | Anikwe, C. C., et al., Female genital mutilation and obstetric outcome: A cross-sectional comparative study in a tertiary hospital in Abakaliki South East Nigeria. Eur J Obstet Gynecol Reprod Biol X, 2019. 1: p. 100005. |
| [17] | Berg, R. C. and V. Underland, The obstetric consequences of female genital mutilation/cutting: a systematic review and meta-analysis. Obstet Gynecol Int, 2013. 2013: p. 496564. |
| [18] | Gebremicheal, K., et al., Sequela of female genital mutilation on birth outcomes in Jijiga town, Ethiopian Somali region: a prospective cohort study. BMC Pregnancy Childbirth, 2018. 18(1): p. 305. |
| [19] | Reisel, D. and S. M. Creighton, Long term health consequences of Female Genital Mutilation (FGM). Maturitas, 2015. 80(1): p. 48-51. |
| [20] |
Sarayloo, K., R. Latifnejad Roudsari, and A. Elhadi, Health Consequences of the Female Genital Mutilation: A Systematic Review. Galen Med J, 2019. 8: p. e1336.
https://doi.org/10.22086/gmj.v8i0.1336. eCollection 2019 |
| [21] | Al-Hussaini, T. K., Female genital cutting: types, motives and perineal damage in laboring Egyptian women. Med Princ Pract, 2003. 12(2): p. 123-8. |
| [22] | Millogo-Traore, F., et al., [Maternal and foetal prognostic in excised women delivery]. J Gynecol Obstet Biol Reprod (Paris), 2007. 36(4): p. 393-8. |
| [23] | WHO, A Systematic Review of the Health Complications of Female Genital Mutilation including Sequelae in Childbirth. WHO_FCH_WMH, 2000. 00.2. |
| [24] | Kasim, Y. M., I. F. Abdul, and O. R. Balogun, Female genital mutilation and reproductive outcome. Nigeria Journal of Medicine, 2002. 11(3): p. 105-107. |
| [25] | Banks, E., et al., Female genital mutilation and obstetric outcome: WHO collaborative prospective study in six African countries. Lancet, 2006. 367(9525): p. 1835-41. |
| [26] | Balachandran, A. A., et al., Are obstetric outcomes affected by female genital mutilation? Int Urogynecol J, 2018. 29(3): p. 339-344. |
| [27] | Essen, B., et al., No association between female circumcision and prolonged labour: a case control study of immigrant women giving birth in Sweden. Eur J Obstet Gynecol Reprod Biol, 2005. 121(2): p. 182-5. |
| [28] | Say, L., et al., Global causes of maternal death: a WHO systematic analysis. Lancet Glob Health, 2014. 2(6): p. e323-33. |
| [29] | Melesse, Y., et al., One-sixth of women experienced obstructed labor among those delivered at public hospitals in Southern Ethiopia: A multicenter study. SAGE Open Med, 2023. 11: p. 20503121231164056. |
| [30] | Seidu, A. A., et al., Female genital mutilation and skilled birth attendance among women in sub-Saharan Africa. BMC Womens Health, 2022. 22(1): p. 26. |
| [31] | Ako, M. A. and P. Akweongo, The limited effectiveness of legislation against female genital mutilation and the role of community beliefs in Upper East Region, Ghana. Reprod Health Matters, 2009. 17(34): p. 47-54. |
APA Style
Abesig, J. W., Maya, E. T., Ganle, J. K. (2026). A Maternal Near-Miss: A Case Report of Prolonged Labour Due to Female Genital Mutilation at the Bole District Hospital, Ghana. World Journal of Medical Case Reports, 7(1), 9-13. https://doi.org/10.11648/j.wjmcr.20260701.13
ACS Style
Abesig, J. W.; Maya, E. T.; Ganle, J. K. A Maternal Near-Miss: A Case Report of Prolonged Labour Due to Female Genital Mutilation at the Bole District Hospital, Ghana. World J. Med. Case Rep. 2026, 7(1), 9-13. doi: 10.11648/j.wjmcr.20260701.13
AMA Style
Abesig JW, Maya ET, Ganle JK. A Maternal Near-Miss: A Case Report of Prolonged Labour Due to Female Genital Mutilation at the Bole District Hospital, Ghana. World J Med Case Rep. 2026;7(1):9-13. doi: 10.11648/j.wjmcr.20260701.13
@article{10.11648/j.wjmcr.20260701.13,
  author = {Jonathan Wadeyir Abesig and Ernest Tei Maya and John Kuumuori Ganle},
  title = {A Maternal Near-Miss: A Case Report of Prolonged Labour Due to Female Genital Mutilation at the Bole District Hospital, Ghana},
  journal = {World Journal of Medical Case Reports},
  volume = {7},
  number = {1},
  pages = {9-13},
  doi = {10.11648/j.wjmcr.20260701.13},
  url = {https://doi.org/10.11648/j.wjmcr.20260701.13},
  eprint = {https://article.sciencepublishinggroup.com/pdf/10.11648.j.wjmcr.20260701.13},
  abstract = {Introduction: Ghana continues to grapple with the complex issue of female genital mutilation/cutting (FGM/C), a practice marked by notable regional disparities. Driven by multifaceted motivations, including deeply ingrained cultural values, perceived benefits for the girl child, and efforts to curb sexual promiscuity, FGM/C poses significant health risks. This article presents a near-miss case of a 19-year-old woman who experienced prolonged labour and postpartum haemorrhage (PPH) due to complications arising from FGM/C. Case Presentation: A 19-year-old woman with a history of FGM/C presented with prolonged labour and PPH. Physical examination revealed Type 3 FGM/C (infibulation) complicated by multiple perineal and vaginal tears. A vaginal delivery was facilitated by bilateral episiotomy, and the episiotomies and lacerations were subsequently repaired. Due to significant blood loss from PPH, the patient received 2 units of whole blood. Fortunately, the mother recovered physically well, with normal urinary and faecal continence, and the baby pair is doing well. However, true recovery in this case will require an enabling environment and supportive care to address her psychosocial needs. Conclusion: We strongly recommend a comprehensive approach to eradicate FGM/C, including awareness creation, strengthening anti-FGM/C laws, and providing a supportive environment that promotes the physical, psychological, and social well-being of victims. Collective efforts by all stakeholders are crucial to achieving this goal and ensuring that women and girls are protected from the harmful effects of FGM/C.},
 year = {2026}
}
TY  - JOUR
T1  - A Maternal Near-Miss: A Case Report of Prolonged Labour Due to Female Genital Mutilation at the Bole District Hospital, Ghana
AU  - Jonathan Wadeyir Abesig
AU  - Ernest Tei Maya
AU  - John Kuumuori Ganle
Y1  - 2026/02/20
PY  - 2026
N1  - https://doi.org/10.11648/j.wjmcr.20260701.13
DO  - 10.11648/j.wjmcr.20260701.13
T2  - World Journal of Medical Case Reports
JF  - World Journal of Medical Case Reports
JO  - World Journal of Medical Case Reports
SP  - 9
EP  - 13
PB  - Science Publishing Group
SN  - 2994-726X
UR  - https://doi.org/10.11648/j.wjmcr.20260701.13
AB  - Introduction: Ghana continues to grapple with the complex issue of female genital mutilation/cutting (FGM/C), a practice marked by notable regional disparities. Driven by multifaceted motivations, including deeply ingrained cultural values, perceived benefits for the girl child, and efforts to curb sexual promiscuity, FGM/C poses significant health risks. This article presents a near-miss case of a 19-year-old woman who experienced prolonged labour and postpartum haemorrhage (PPH) due to complications arising from FGM/C. Case Presentation: A 19-year-old woman with a history of FGM/C presented with prolonged labour and PPH. Physical examination revealed Type 3 FGM/C (infibulation) complicated by multiple perineal and vaginal tears. A vaginal delivery was facilitated by bilateral episiotomy, and the episiotomies and lacerations were subsequently repaired. Due to significant blood loss from PPH, the patient received 2 units of whole blood. Fortunately, the mother recovered physically well, with normal urinary and faecal continence, and the baby pair is doing well. However, true recovery in this case will require an enabling environment and supportive care to address her psychosocial needs. Conclusion: We strongly recommend a comprehensive approach to eradicate FGM/C, including awareness creation, strengthening anti-FGM/C laws, and providing a supportive environment that promotes the physical, psychological, and social well-being of victims. Collective efforts by all stakeholders are crucial to achieving this goal and ensuring that women and girls are protected from the harmful effects of FGM/C.
VL  - 7
IS  - 1
ER  -
Ghana Health Service, Bole District Hospital, Bole, Ghana;School of Public Health, University of Ghana, Accra, Ghana
School of Public Health, University of Ghana, Accra, Ghana
School of Public Health, University of Ghana, Accra, Ghana

Information



 Share This Article
 Twitter
 Linked In
 Facebook

 Copy
 Download