
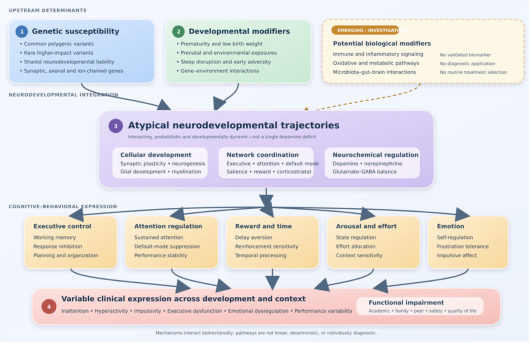
Background: Attention-deficit/hyperactivity disorder (ADHD) is one of the most common neurodevelopmental disorders of childhood and is associated with substantial academic, behavioral, social, emotional, and health-related burdens. Contemporary care extends beyond symptom identification to include developmentally informed assessment, recognition of comorbidities, shared decision-making, and measurement-based multimodal treatment. Objective: To provide an updated, clinically oriented synthesis of current evidence on the epidemiology, neurobiology, diagnosis, differential diagnosis, comorbidities, treatment, monitoring, and long-term management of ADHD in children and adolescents. Methods: This narrative clinical review used a focused PubMed/MEDLINE search covering January 1, 2018, through August 22, 2026, supplemented by foundational publications and authoritative guidance from the American Academy of Pediatrics, National Institute for Health and Care Excellence, US Food and Drug Administration, Centers for Disease Control and Prevention, and National Institute of Mental Health. The search identified 183 records for initial consideration. Evidence was selected purposively according to pediatric relevance, methodological rigor, clinical applicability, and regulatory status. Results: ADHD is a heterogeneous disorder arising from complex genetic, neurobiological, and environmental influences. Diagnosis remains clinical and requires developmentally inappropriate symptoms, functional impairment, childhood onset, and manifestations in more than one setting, while excluding alternative explanations. Rating scales support but do not replace comprehensive clinical assessment. Comorbid learning, anxiety, depressive, oppositional, autism spectrum, tic, sleep, and substance-use disorders can substantially influence presentation and management. Behavioral parent training is recommended as first-line treatment for preschool-aged children. For most school-aged children and adolescents with clinically significant impairment, stimulants provide the strongest evidence for reducing core symptoms, whereas atomoxetine, extended-release guanfacine, extended-release clonidine, and extended-release viloxazine are appropriate alternatives for selected patients. Effective management integrates medication when indicated with psychoeducation, behavioral strategies, school-based interventions, and treatment of comorbidities. Monitoring should address symptoms, functioning, adherence, appetite, growth, sleep, blood pressure, heart rate, mood, and medication misuse or diversion. Digital interventions may offer adjunctive benefits, but current evidence does not support replacing established treatments. Conclusions: Pediatric ADHD should be managed as a chronic, developmentally evolving condition. Accurate diagnosis, individualized multimodal treatment, systematic monitoring, and planned transition to adult services can improve symptoms and functioning. Objective biomarkers, pharmacogenomics, neurostimulation, microbiome-directed therapies, and most digital interventions remain adjunctive or investigational.
| Published in | Frontiers (Volume 9, Issue 3) |
| DOI | 10.11648/j.frontiers.20260903.11 |
| Page(s) | 1-11 |
| Creative Commons |
This is an Open Access article, distributed under the terms of the Creative Commons Attribution 4.0 International License (http://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, distribution and reproduction in any medium or format, provided the original work is properly cited. |
| Copyright |
Copyright © The Author(s), 2026. Published by Science Publishing Group |
Attention-deficit/Hyperactivity Disorder, Children, Adolescents, Neurodevelopment, Stimulants, Behavioral Parent Training, School Interventions, Clinical Management
Class | Typical pediatric use | Approximate coverage | Principal considerations |
|---|---|---|---|
Methylphenidate/dexmethylphenidate | Usually first stimulant trial in school-aged children; immediate- and extended-release oral or transdermal formulations | 3-12 hours, product dependent | Titrate to function and tolerability; monitor appetite, growth, sleep, pulse, blood pressure, mood, and misuse [28 -31, 36-39]. |
Amphetamine derivatives, including lisdexamfetamine | Alternative first-line stimulant; several immediate- and extended-release formulations | 4-16 hours, product dependent | Often potent; products are not milligram-for-milligram interchangeable. Apply controlled-substance safeguards [28 -31, 40-46]. |
Centanafadine extended release | An FDA approval letter was issued on July 24, 2026, for patients aged 6 years or older who weigh at least 20 kg; marketing was contingent on completion of controlled-substance scheduling, so current availability and labeling must be verified. | Once daily | Triple monoamine reuptake inhibitor and central nervous system stimulant. Labeling addresses suicidal ideation or behavior and abuse, misuse, and addiction; verify current FDA labeling and scheduling status before clinical use [47, 48]. |
Atomoxetine | Nonstimulant from age 6 years; useful with stimulant intolerance, anxiety, tics, or misuse concern | All-day after gradual onset | Dose by weight; monitor mood, blood pressure, pulse, growth, rare hepatic symptoms, and CYP2D6 interactions [33] . |
Viloxazine extended release | Nonstimulant from age 6 years | Once daily | Monitor suicidal thoughts/behavior, activation, blood pressure, pulse, sleep, and CYP1A2 interactions [35] . |
Guanfacine or clonidine extended release | Monotherapy or stimulant adjunct from age 6 years; may help hyperactivity, tics, sleep, or evening symptoms | Once daily or divided, product dependent | Sedation, hypotension, bradycardia, and rebound hypertension; taper gradually [34, 49, 50]. |
AAP | American Academy of Pediatrics |
ADHD | Attention-deficit/Hyperactivity Disorder |
CDC | Centers for Disease Control and Prevention |
CYP1A2 | Cytochrome P450 1A2 |
CYP2D6 | Cytochrome P450 2D6 |
EEG | Electroencephalography |
FDA | US Food and Drug Administration |
GABA | Gamma-aminobutyric Acid |
NICE | National Institute for Health and Care Excellence |
NIMH | National Institute of Mental Health |
| [1] | American Psychiatric Association. Diagnostic and Statistical Manual of Mental Disorders. 5th ed, text revision. Washington (DC): American Psychiatric Association Publishing; 2022. Available from: |
| [2] | Wolraich ML, Hagan JF Jr, Allan C, Chan E, Davison D, Earls M, et al. Clinical practice guideline for the diagnosis, evaluation, and treatment of attention-deficit/hyperactivity disorder in children and adolescents. Pediatrics. 2019; 144(4): e20192528. |
| [3] | National Institute for Health and Care Excellence. Attention deficit hyperactivity disorder: diagnosis and management. NICE guideline NG87 [Internet]. London: NICE; 2018 [updated 2019; cited 2026 Aug 21]. Available from: |
| [4] | Faraone SV, Banaschewski T, Coghill D, Zheng Y, Biederman J, Bellgrove MA, et al. The World Federation of ADHD International Consensus Statement: 208 evidence-based conclusions about the disorder. Neurosci Biobehav Rev. 2021; 128: 789-818. Available from: |
| [5] | Cénat JM, Blais-Rochette C, Morse C, Vandette MP, Noorishad PG, Kogan C, et al. Prevalence and risk factors associated with attention-deficit/hyperactivity disorder among US Black individuals: a systematic review and meta-analysis. JAMA Psychiatry. 2021; 78(1): 21-28. Available from: |
| [6] | Polanczyk GV, Salum GA, Sugaya LS, Caye A, Rohde LA. Annual research review: a meta-analysis of the worldwide prevalence of mental disorders in children and adolescents. J Child Psychol Psychiatry. 2015; 56(3): 345-365. Available from: |
| [7] | Bellato A, Perrott NJ, Marzulli L, Parlatini V, Coghill D, Cortese S. Systematic review and meta-analysis: effects of pharmacological treatment for attention-deficit/hyperactivity disorder on quality of life. J Am Acad Child Adolesc Psychiatry. 2025; 64(4): 433-448. Available from: |
| [8] | Demontis D, Walters GB, Athanasiadis G, Walters R, Therrien K, Nielsen TT, et al. Genome-wide analyses of ADHD identify 27 risk loci, refine the genetic architecture and implicate several cognitive domains. Nat Genet. 2023; 55(2): 198-208. Available from: |
| [9] | Faraone SV, Bellgrove MA, Brikell I, Cortese S, Hartman CA, Hollis C, et al. Attention-deficit/hyperactivity disorder. Nat Rev Dis Primers. 2024; 10(1): 11. Available from: |
| [10] | Demontis D, Duan J, Hsu YHH, Pintacuda G, Grove J, Nielsen TT, et al. Rare genetic variants confer a high risk of ADHD and implicate neuronal biology. Nature. 2026; 649(8098): 909-917. Available from: |
| [11] | McNeill RV, Schickardt Z, Radtke F, Blum R, Kittel-Schneider S. hiPSC-derived cortical neurons from ADHD individuals reveal dysregulated glutamatergic development. Mol Psychiatry. 2026; 31(2): 1041-1050. Available from: |
| [12] | Bouyssi-Kobar M, Zhang Y, Norman L, Choudhury S, Sharp W, Sudre G, et al. Developmental trajectories of glutamate and the variable clinical course of ADHD in youth. Transl Psychiatry. 2026; 16(1): 157. Available from: |
| [13] | Shastri GG, Sudre G, Ahn K, Jung B, Kolachana B, Auluck PK, et al. Cortico-striatal differences in the epigenome in attention-deficit/hyperactivity disorder. Transl Psychiatry. 2024; 14(1): 189. Available from: |
| [14] | Brown AA, Widdowson M, Brandt S, Mohammadzadeh P, Rosenberg JB, Jepsen JRM, et al. Associations of the gut microbiome and inflammatory markers with mental health symptoms: a cross-sectional study on Danish adolescents. Sci Rep. 2025; 15(1): 10378. Available from: |
| [15] | Centers for Disease Control and Prevention. Clinical care of ADHD in children [Internet]. Atlanta: CDC; [cited 2026 Aug 21]. Available from: |
| [16] | Wolraich ML, Lambert W, Doffing MA, Bickman L, Simmons T, Worley K. Psychometric properties of the Vanderbilt ADHD Diagnostic Parent Rating Scale in a referred population. J Pediatr Psychol. 2003; 28(8): 559-568. Available from: |
| [17] | Conners CK. Conners 4th Edition (Conners 4): Manual. Toronto (ON): Multi-Health Systems; 2022. |
| [18] | Ishibashi T, Takahashi N, Kawabata Y, Matsumoto T, Takei N. Psychometrics of rating scales for externalizing disorders in Japanese outpatients: the ADHD-Rating Scale-5 and the Disruptive Behavior Disorders Rating Scale. Int J Methods Psychiatr Res. 2024; 33(1): e2015. Available from: |
| [19] | Al Jaffal M, Becker D, Alhossein A, Bakhiet SF, Aldabas R, Abaoud A, et al. The psychometric properties of the ADHD rating scale-5 for children and adolescents, home version for Sudan. Front Psychiatry. 2024; 15: 1365189. Available from: |
| [20] | Arrondo G, Mulraney M, Iturmendi-Sabater I, Musullulu H, Gambra L, Niculcea T, et al. Systematic review and meta-analysis: clinical utility of continuous performance tests for the identification of attention-deficit/hyperactivity disorder. J Am Acad Child Adolesc Psychiatry. 2024; 63(2): 154-171. Available from: |
| [21] | Bellato A, Hall CL, Groom MJ, Simonoff E, Thapar A, Hollis C, et al. Practitioner review: clinical utility of the QbTest for the assessment and diagnosis of attention-deficit/hyperactivity disorder-a systematic review and meta-analysis. J Child Psychol Psychiatry. 2024; 65(6): 845-861. Available from: |
| [22] | US Food and Drug Administration. QbTest: 510(k) premarket notification K122149 [Internet]. Silver Spring (MD): FDA; 2012 [cited 2026 Aug 21]. Available from: |
| [23] | National Institute for Health and Care Excellence. Digital technologies for assessing attention deficit hyperactivity disorder: early value assessment. HealthTech guidance HTG729 [Internet]. London: NICE; 2024 [cited 2026 Aug 21]. Available from: |
| [24] | Peterson BS, Trampush J, Brown M, Maglione M, Bolshakova M, Rozelle M, et al. Tools for the diagnosis of ADHD in children and adolescents: a systematic review. Pediatrics. 2024; 153(4): e2024065854. Available from: |
| [25] | Slater J, Joober R, Koborsy BL, Mitchell S, Sahlas E, Palmer C. Can electroencephalography (EEG) identify ADHD subtypes? A systematic review. Neurosci Biobehav Rev. 2022; 139: 104752. Available from: |
| [26] | Zhou J, Jiang W, Wang J, Dou J. Network meta-analysis of the effects of long-term non-pharmacologic treatment on inhibitory control in children and adolescents with attention deficit hyperactivity disorder. J Psychiatr Res. 2025; 187: 261-276. Available from: |
| [27] | Sibley MH, Arnold LE, Swanson JM, Hechtman LT, Kennedy TM, Owens E, et al. Non-pharmacological interventions for attention-deficit hyperactivity disorder in children and adolescents. Lancet Child Adolesc Health. 2023; 7(6): 415-428. Available from: |
| [28] | Farhat LC, Cortese S, et al. Pharmacological interventions for ADHD: a systematic review and dose–effect network meta-analysis. Lancet Psychiatry. 2026; 13(6): 485-495. Available from: |
| [29] | Mechler K, Banaschewski T, Hohmann S, Häge A. Evidence-based pharmacological treatment options for ADHD in children and adolescents. Pharmacol Ther. 2022; 230: 107940. Available from: |
| [30] | US Food and Drug Administration. Prescription stimulant medications [Internet]. Silver Spring (MD): FDA; [cited 2026 Sep 3]. Available from: |
| [31] | US Food and Drug Administration. Pediatric information added to labeling for drugs and biologics in 2024 [Internet]. Silver Spring (MD): FDA; 2025 [cited 2026 Aug 21]. Available from: |
| [32] |
US Food and Drug Administration. Strattera (atomoxetine hydrochloride) capsules: prescribing information [Internet]. Silver Spring (MD): FDA; 2026 [cited 2026 Aug 21]. Available from:
https://www.accessdata.fda.gov/drugsatfda_docs/label/2026/021411s053lbl.pdf |
| [33] |
National Library of Medicine (US). Onyda XR (clonidine hydrochloride) extended-release oral suspension: prescribing information [Internet]. Bethesda (MD): DailyMed; [cited 2026 Aug 22]. Available from:
https://dailymed.nlm.nih.gov/dailymed/lookup.cfm?setid=4a15c850-9da5-4bdc-a34d-7f740a6149b7 |
| [34] |
National Library of Medicine (US). Qelbree (viloxazine hydrochloride) extended-release capsules: prescribing information [Internet]. Bethesda (MD): DailyMed; [cited 2026 Aug 22]. Available from:
https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=aedf408d-0f84-418d-9416-7c39ddb0d29a |
| [35] |
US Food and Drug Administration. Relexxii (methylphenidate hydrochloride extended-release tablets): multidisciplinary review, NDA 216117 [Internet]. Silver Spring (MD): FDA; 2023 [cited 2026 Aug 22]. Available from:
https://www.accessdata.fda.gov/drugsatfda_docs/nda/2023/216117Orig1s000MultidisciplineR.pdf |
| [36] |
US Food and Drug Administration. Jornay PM (methylphenidate hydrochloride) extended-release capsules: prescribing information [Internet]. Silver Spring (MD): FDA; 2018 [cited 2026 Aug 22]. Available from:
https://www.accessdata.fda.gov/drugsatfda_docs/nda/2018/209311Orig1s000Lbl.pdf |
| [37] |
US Food and Drug Administration. Daytrana (methylphenidate transdermal system): prescribing information [Internet]. Silver Spring (MD): FDA; 2025 [cited 2026 Aug 22]. Available from:
https://www.accessdata.fda.gov/drugsatfda_docs/label/2025/021514s043lbl.pdf |
| [38] |
US Food and Drug Administration. Azstarys (serdexmethylphenidate and dexmethylphenidate) capsules: prescribing information [Internet]. Silver Spring (MD): FDA; 2021 [cited 2026 Aug 22]. Available from:
https://www.accessdata.fda.gov/drugsatfda_docs/nda/2021/212994Orig1s000lbl.pdf |
| [39] |
National Library of Medicine (US). Adderall (mixed amphetamine salts) tablets: prescribing information [Internet]. Bethesda (MD): DailyMed; [cited 2026 Aug 22]. Available from:
https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=f22635fe-821d-4cde-aa12-419f8b53db81 |
| [40] |
National Library of Medicine (US). Mydayis (mixed amphetamine salts) extended-release capsules: prescribing information [Internet]. Bethesda (MD): DailyMed; [cited 2026 Aug 22]. Available from:
https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=141a7970-3f06-44ea-9ab7-aeece2c085fc |
| [41] |
National Library of Medicine (US). Vyvanse (lisdexamfetamine dimesylate) capsules and chewable tablets: prescribing information [Internet]. Bethesda (MD): DailyMed; [cited 2026 Aug 22]. Available from:
https://dailymed.nlm.nih.gov/dailymed/lookup.cfm?setid=704e4378-ca83-445c-8b45-3cfa51c1ecad |
| [42] |
National Library of Medicine (US). Xelstrym (dextroamphetamine) transdermal system: prescribing information [Internet]. Bethesda (MD): DailyMed; [cited 2026 Aug 22]. Available from:
https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=0862f02a-72a8-41cc-8845-57cf4974bb6f |
| [43] |
National Library of Medicine (US). Evekeo ODT (amphetamine sulfate) orally disintegrating tablets: prescribing information [Internet]. Bethesda (MD): DailyMed; [cited 2026 Aug 22]. Available from:
https://dailymed.nlm.nih.gov/dailymed/downloadpdffile.cfm?setId=1e25f905-6c0b-4b19-a3b6-b2a386afa1c3 |
| [44] |
National Library of Medicine (US). Dyanavel XR (amphetamine) extended-release oral suspension and tablets: prescribing information [Internet]. Bethesda (MD): DailyMed; [cited 2026 Aug 22]. Available from:
https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=ae304b29-0b40-40ec-ad0d-76b742d4a9b9 |
| [45] |
National Library of Medicine (US). Adzenys XR-ODT (amphetamine) extended-release orally disintegrating tablets: prescribing information [Internet]. Bethesda (MD): DailyMed; [cited 2026 Sep 3]. Available from:
https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=c1179269-00b5-48ea-972d-31e614e99b7e |
| [46] | Otsuka Pharmaceutical Development & Commercialization, Inc. Simtriyo (centanafadine) extended-release capsules: prescribing information submitted with NDA 218145 [Internet]. Princeton (NJ): Otsuka; 2026 [cited 2026 Sep 3]. Available from: |
| [47] |
US Food and Drug Administration. Simtriyo (centanafadine): approval letter, NDA 218145 [Internet]. Silver Spring (MD): FDA; 2026 [cited 2026 Sep 3]. Available from:
https://www.accessdata.fda.gov/drugsatfda_docs/appletter/2026/218145Orig1s000ltr.pdf |
| [48] |
National Library of Medicine (US). Intuniv (guanfacine) extended-release tablets: prescribing information [Internet]. Bethesda (MD): DailyMed; [cited 2026 Sep 3]. Available from:
https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=b972af81-3a37-40be-9fe1-3ddf59852528 |
| [49] |
National Library of Medicine (US). Kapvay (clonidine hydrochloride) extended-release tablets: prescribing information [Internet]. Bethesda (MD): DailyMed; [cited 2026 Aug 22].
Available from:
https://dailymed.nlm.nih.gov/dailymed/downloadpdffile.cfm?setId=aa7700e2-ae5d-44c4-a609-76de19c705a7 |
| [50] | Thorell LB, Chistiansen H, Hammar M, Berggren S, Zander E, Bölte S. Standardization and cross-cultural comparisons of the Swedish Conners 3 rating scales. Nord J Psychiatry. 2018; 72(8): 613-620. Available from: |
| [51] | Gabarron E, Denecke K, Lopez-Campos G. Evaluating the evidence: a systematic review of reviews of the effectiveness and safety of digital interventions for ADHD. BMC Psychiatry. 2025; 25(1): 414. Available from: |
| [52] |
US Food and Drug Administration. EndeavorRx: De Novo classification request DEN200026 [Internet]. Silver Spring (MD): FDA; 2020 [cited 2026 Sep 3]. Available from:
https://www.accessdata.fda.gov/scripts/cdrh/cfdocs/cfpmn/denovo.cfm?ID=DEN200026 |
| [53] | Kollins SH, DeLoss DJ, Cañadas E, Lutz J, Findling RL, Keefe RSE, et al. A novel digital intervention for actively reducing severity of paediatric ADHD (STARS-ADHD): a randomised controlled trial. Lancet Digit Health. 2020; 2(4): e168-e178. Available from: |
| [54] | Lee H, Lee S, Hwang M, Woo K. Effectiveness of game-based digital intervention for attention-deficit hyperactivity disorder in children and adolescents: a systematic review and meta-analysis using Beard and Wilson’s conceptualization of perception in experiential learning. Eur Child Adolesc Psychiatry. 2025; 34(12): 3853-3869. Available from: |
APA Style
Cardenas, V. M. M. (2026). Attention-Deficit/Hyperactivity Disorder in Children and Adolescents: Contemporary Advances in Diagnosis and Management-A Clinical Update. Frontiers, 9(3), 1-11. https://doi.org/10.11648/j.frontiers.20260903.11
ACS Style
Cardenas, V. M. M. Attention-Deficit/Hyperactivity Disorder in Children and Adolescents: Contemporary Advances in Diagnosis and Management-A Clinical Update. Frontiers. 2026, 9(3), 1-11. doi: 10.11648/j.frontiers.20260903.11
@article{10.11648/j.frontiers.20260903.11,
  author = {Vicente Manuel Martinez Cardenas},
  title = {Attention-Deficit/Hyperactivity Disorder in Children and Adolescents: Contemporary Advances in Diagnosis and Management-A Clinical Update},
  journal = {Frontiers},
  volume = {9},
  number = {3},
  pages = {1-11},
  doi = {10.11648/j.frontiers.20260903.11},
  url = {https://doi.org/10.11648/j.frontiers.20260903.11},
  eprint = {https://article.sciencepublishinggroup.com/pdf/10.11648.j.frontiers.20260903.11},
  abstract = {Background: Attention-deficit/hyperactivity disorder (ADHD) is one of the most common neurodevelopmental disorders of childhood and is associated with substantial academic, behavioral, social, emotional, and health-related burdens. Contemporary care extends beyond symptom identification to include developmentally informed assessment, recognition of comorbidities, shared decision-making, and measurement-based multimodal treatment. Objective: To provide an updated, clinically oriented synthesis of current evidence on the epidemiology, neurobiology, diagnosis, differential diagnosis, comorbidities, treatment, monitoring, and long-term management of ADHD in children and adolescents. Methods: This narrative clinical review used a focused PubMed/MEDLINE search covering January 1, 2018, through August 22, 2026, supplemented by foundational publications and authoritative guidance from the American Academy of Pediatrics, National Institute for Health and Care Excellence, US Food and Drug Administration, Centers for Disease Control and Prevention, and National Institute of Mental Health. The search identified 183 records for initial consideration. Evidence was selected purposively according to pediatric relevance, methodological rigor, clinical applicability, and regulatory status. Results: ADHD is a heterogeneous disorder arising from complex genetic, neurobiological, and environmental influences. Diagnosis remains clinical and requires developmentally inappropriate symptoms, functional impairment, childhood onset, and manifestations in more than one setting, while excluding alternative explanations. Rating scales support but do not replace comprehensive clinical assessment. Comorbid learning, anxiety, depressive, oppositional, autism spectrum, tic, sleep, and substance-use disorders can substantially influence presentation and management. Behavioral parent training is recommended as first-line treatment for preschool-aged children. For most school-aged children and adolescents with clinically significant impairment, stimulants provide the strongest evidence for reducing core symptoms, whereas atomoxetine, extended-release guanfacine, extended-release clonidine, and extended-release viloxazine are appropriate alternatives for selected patients. Effective management integrates medication when indicated with psychoeducation, behavioral strategies, school-based interventions, and treatment of comorbidities. Monitoring should address symptoms, functioning, adherence, appetite, growth, sleep, blood pressure, heart rate, mood, and medication misuse or diversion. Digital interventions may offer adjunctive benefits, but current evidence does not support replacing established treatments. Conclusions: Pediatric ADHD should be managed as a chronic, developmentally evolving condition. Accurate diagnosis, individualized multimodal treatment, systematic monitoring, and planned transition to adult services can improve symptoms and functioning. Objective biomarkers, pharmacogenomics, neurostimulation, microbiome-directed therapies, and most digital interventions remain adjunctive or investigational.},
 year = {2026}
}
TY  - JOUR
T1  - Attention-Deficit/Hyperactivity Disorder in Children and Adolescents: Contemporary Advances in Diagnosis and Management-A Clinical Update
AU  - Vicente Manuel Martinez Cardenas
Y1  - 2026/09/22
PY  - 2026
N1  - https://doi.org/10.11648/j.frontiers.20260903.11
DO  - 10.11648/j.frontiers.20260903.11
T2  - Frontiers
JF  - Frontiers
JO  - Frontiers
SP  - 1
EP  - 11
PB  - Science Publishing Group
SN  - 2994-7197
UR  - https://doi.org/10.11648/j.frontiers.20260903.11
AB  - Background: Attention-deficit/hyperactivity disorder (ADHD) is one of the most common neurodevelopmental disorders of childhood and is associated with substantial academic, behavioral, social, emotional, and health-related burdens. Contemporary care extends beyond symptom identification to include developmentally informed assessment, recognition of comorbidities, shared decision-making, and measurement-based multimodal treatment. Objective: To provide an updated, clinically oriented synthesis of current evidence on the epidemiology, neurobiology, diagnosis, differential diagnosis, comorbidities, treatment, monitoring, and long-term management of ADHD in children and adolescents. Methods: This narrative clinical review used a focused PubMed/MEDLINE search covering January 1, 2018, through August 22, 2026, supplemented by foundational publications and authoritative guidance from the American Academy of Pediatrics, National Institute for Health and Care Excellence, US Food and Drug Administration, Centers for Disease Control and Prevention, and National Institute of Mental Health. The search identified 183 records for initial consideration. Evidence was selected purposively according to pediatric relevance, methodological rigor, clinical applicability, and regulatory status. Results: ADHD is a heterogeneous disorder arising from complex genetic, neurobiological, and environmental influences. Diagnosis remains clinical and requires developmentally inappropriate symptoms, functional impairment, childhood onset, and manifestations in more than one setting, while excluding alternative explanations. Rating scales support but do not replace comprehensive clinical assessment. Comorbid learning, anxiety, depressive, oppositional, autism spectrum, tic, sleep, and substance-use disorders can substantially influence presentation and management. Behavioral parent training is recommended as first-line treatment for preschool-aged children. For most school-aged children and adolescents with clinically significant impairment, stimulants provide the strongest evidence for reducing core symptoms, whereas atomoxetine, extended-release guanfacine, extended-release clonidine, and extended-release viloxazine are appropriate alternatives for selected patients. Effective management integrates medication when indicated with psychoeducation, behavioral strategies, school-based interventions, and treatment of comorbidities. Monitoring should address symptoms, functioning, adherence, appetite, growth, sleep, blood pressure, heart rate, mood, and medication misuse or diversion. Digital interventions may offer adjunctive benefits, but current evidence does not support replacing established treatments. Conclusions: Pediatric ADHD should be managed as a chronic, developmentally evolving condition. Accurate diagnosis, individualized multimodal treatment, systematic monitoring, and planned transition to adult services can improve symptoms and functioning. Objective biomarkers, pharmacogenomics, neurostimulation, microbiome-directed therapies, and most digital interventions remain adjunctive or investigational.
VL  - 9
IS  - 3
ER  -
Department of Pediatrics, Children’s Medical Center, Lake City, United States

Information



 Share This Article
 Twitter
 Linked In
 Facebook

 Copy
 Download