Contribution of Computed Tomography to the Diagnosis of Urinary Lithiasis at the Ouahigouya Regional University Hospital Center: A Study of 128 Cases (Burkina Faso)
Department of Nephrology and Hemodialysis, Ledea Bernard Ouedraogo University and Regional University Hospital Center of Ouahigouya, Ouahigouya, Burkina Faso
Contributor Roles: Conceptualization, Data curation, Formal Analysis, Methodology, Validation
Department of Urology and Andrology, Ledea Bernard Ouedraogo University and Regional University Hospital Center of Ouahigouya, Ouahigouya, Burkina Faso
Objectives: To assess the diagnostic contribution of computed tomography (CT) in urinary stone disease at the Ouahigouya Regional University Hospital Center (CHUR-OHG), Burkina Faso, from May 2021 to December 31, 2024. Materials and Methods: We conducted a descriptive retrospective study over approximately four years, from May 1, 2021, to December 31, 2024. We reviewed the CT examinations performed for suspected urinary stone disease during the study period. Results: A total of 128 CT examinations were included. The male-to-female ratio was 1.97, and the mean age was 42.02 years. Renal colic was the most common indication for CT (42.19%). Stones were most frequently located in the ureter (36.72%). The main complications were ureterohydronephrosis (39.85%) and calyceal dilatation (20.32%), whereas no complications were observed in 37.50% of cases. CT most frequently identified calcium oxalate and uric acid stones, accounting for 29.68% and 28.13% of cases, respectively. Stone location was significantly associated with urinary tract obstruction or dilatation (p < 0.001), but not with stone composition (p = 0.746). Prostatic hypertrophy was the most common organic risk factor, identified in 11.71% of cases, whereas no organic risk factor was identified in 77.34% of cases. Conclusion: Computed tomography plays a central role in the diagnosis and therapeutic management of urinary stone disease. It provides valuable information on stone location, composition, and associated urinary tract complications.
This is an Open Access article, distributed under the terms of the Creative Commons Attribution 4.0 International License (http://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, distribution and reproduction in any medium or format, provided the original work is properly cited.
Urinary lithiasis is a common and potentially serious condition characterized by a high risk of recurrence. It may remain asymptomatic for prolonged periods or present as an acute condition requiring emergency care. Its prevalence varies substantially across regions, ranging from 7% to 13% in North America, 5% to 9% in Europe, and 1% to 5% in Asia, with an overall increasing trend worldwide
[1]
Sorokin I, Mamoulakis C, Miyazawa K, et al. Epidemiology of stone disease across the world. World J Urol 2017; 35: 1301–1320.
. In the United States, approximately one in eleven individuals develops urinary stones during their lifetime, with a notable increase in incidence among women, children, and populations historically considered to be at lower risk
[2]
Tasian GE, Ross ME, Song L, et al. Annual Incidence of Nephrolithiasis among Children and Adults in South Carolina from 1997 to 2012. Clin J Am Soc Nephrol CJASN 2016; 11: 488–496.
. Studies from Europe and Asia, particularly Italy, Japan, and Saudi Arabia, have likewise reported increasing incidence rates
[4]
Hesse A, Brandle E, Wilbert D, et al. Study on the prevalence and incidence of urolithiasis in Germany comparing the years 1979 vs. 2000. Eur Urol 2003; 44: 709–713.
. In West Africa, studies conducted in Mali and Burkina Faso have reported substantial hospital-based prevalence rates of 16.67% and 18.87%, respectively, highlighting the growing burden of urinary lithiasis in the subregion
[7]
Traore MT, Kabore M, Ouedraogo S, et al. Epidemiology of Urinary Stone Disease in Northern Burkina Faso. Ann Universite Ouaga 1 Pr Joseph KI-ZERBO Vol 021; 2021.
[8]
Traore I. Epidemiological, Clinical, and Therapeutic Aspects of Urinary Stone Disease in the Urology Department of the Pr. Bocar Sidy Sall University Hospital in Kati: A Study of 81 Cases. Doctoral Dissertation in Medicine, University of Sciences, Techniques and Technologies of Bamako; 2019.
[7, 8]
.
Computed tomography (CT) has become a key imaging modality for the diagnosis and management of urinary lithiasis. According to the recommendations of the Société Francophone de Médecine d'Urgence, first-line imaging may consist of either a combination of plain abdominal radiography and ultrasonography or non-contrast abdominopelvic CT
[9]
Francophone Society of Emergency Medicine (SFMU). 2008 Update of the 8th SFMU Consensus Conference 1999: Management of Renal Colic in Adults. Prog Urol. 2009; 19: 462–473.
[9]
.
CT offers comprehensive assessment of urinary stones, including their location, size, and associated urinary tract abnormalities, and can therefore contribute to therapeutic decision-making.
CT was recently introduced at the Ouahigouya Regional University Hospital Center (CHUR-OHG). However, no local study had yet evaluated its diagnostic contribution to urinary lithiasis. This gap in local evidence provided the rationale for the present study, which aimed to assess the contribution of CT to the diagnosis of urinary lithiasis at CHUR-OHG.
2. Materials and Methods
2.1. Study Design and Period
We conducted a descriptive cross-sectional study with retrospective data collection from May 1, 2021, to December 31, 2024, in the Department of Medical Imaging at the CHUR-OHG, Burkina Faso.
2.2. Study Population, Inclusion and Exclusion Criteria
We included all cases of urinary lithiasis diagnosed by CT during the study period. We excluded patients whose diagnosis was established by ultrasonography and/or plain radiography of the urinary tract, as well as cases for which the CT report was unavailable.
2.4. Data Collection and Sources
Data were collected using an electronic data collection form developed in KoboToolbox. The variables collected included sociodemographic characteristics (age in years, sex, and referring clinical department), clinical characteristics (indication for CT), and CT findings, including stone location, shape, number, laterality, impact on the urinary tract, composition, size, and associated organic risk factors. Data were entered, cleaned, and analyzed using STATA version 16.
2.5. Ethical Considerations
Data confidentiality was ensured by anonymizing the data collection forms. The study was conducted in accordance with applicable ethical principles and institutional requirements.
3. Results
3.1. Sociodemographic and Clinical Characteristics
A total of 128 patients were included, comprising 85 men (66.41%) and 43 women (33.59%). The mean age was 42.02 ± 17.02 years (range, 4–85 years). The most common indication for CT was renal colic, reported in 54 patients (42.19%), followed by lumbar pain in 36 patients (28.13%) and obstructive syndrome with no identifiable cause on ultrasonography in 17 patients (12.87%).
3.2. Computed Tomography Findings
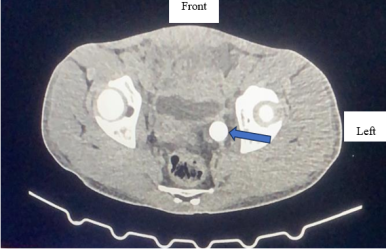
Stones were most frequently located in the ureter (43.71%), followed by the renal calyces (41.41%), renal pelvis (24.22%), and bladder (10.16%). The median number of stones was 1, and a single stone was identified in 58.59% of patients.
Right-sided involvement was the most common pattern, occurring in 53 patients (41.40%).
Stone size was reported for all analyzed stones (n = 150). Most stones, 91 (71.09%), measured 0–15 mm. Stones measuring 15–30 mm accounted for 42 cases (32.81%), whereas 9 stones (7.03%) measured 30–45 mm and 8 stones (6.30%) measured more than 45 mm.
Urinary tract abnormalities related to stone disease were identified in 80 patients (62.50%). Ureterohydronephrosis was the most frequent finding, occurring in 51 patients (39.85%), followed by calyceal dilatation in 26 patients (20.32%) and hydronephrosis in 3 patients (2.34%). No urinary tract abnormalities were identified in 48 patients (37.50%).
Stone composition was not specified in 26 cases (20.31%). Among stones with an identified composition, calcium oxalate dihydrate was the most common, accounting for 38 cases (29.68%), followed by uric acid stones in 36 cases (28.13%). Struvite (magnesium ammonium phosphate) stones accounted for 23 cases (17.97%), while calcium phosphate stones accounted for 5 cases (3.91%).
There was a statistically significant association between stone location and urinary tract impact (χ² = 23.81; p < 0.001), as shown in Table 1.
Table 1. Topography of stones according to their impact on the urinary system.
Topography (n= 128)
With impact n (%)
Without impact n (%)
P value
Pyelic
12 (48.00)
13 (52.00)
< 0.0001
Calicial
19 (43.18)
25 (56.82)
Ureteral
42 (89.36)
5 (10.64)
Bladder
7 (58.33)
5 (41.67)
No statistically significant association was observed between stone composition and stone location (p = 0.746) as Table 2.
Table 2. Nature of stone based on its location.
Topography
Nature (n=128)
P value
Uric acid
Not specified
Calcium oxalate
Calcium phosphate
Magnesium Ammonium Phosphate
Calicial n (%)
15 (34.09)
10 (22.73)
12 (27.27)
1 (2.27)
6 (13.64)
0,746
Pyelic n (%)
4 (16.00)
5 (20.00)
6 (24.00)
2 (8.00)
8 (32.00)
Ureteral n (%)
14 (29.79)
8 (17.02)
16 (34.04)
2 (4.26)
7 (14.89)
Bladder n (%)
3 (25.00)
3 (25.00)
4 (33.33)
0 0.00
2 (16.67)
Organic risk factors identified on CT were relatively uncommon. Prostatic hypertrophy was the most frequently identified organic risk factor, occurring in 15 patients (11.71%). Pyeloureteral junction syndrome, a porcelain bladder, and horseshoe kidney were each observed in 4 patients (3.12%). A bifid ureter was identified in 2 patients (1.56%). No organic risk factor was identified in 99 patients (77.34%) as Table 3.
Table 3. Organic risk factors identified on CT.
Risk factor
Number (n=128)
Percentage (%)
Pyeloureteral junction syndrome
4
3.12
Prostatic hypertrophy
15
11.71
Porcelain bladder
4
3.12
Horseshoe kidney
4
3.12
Bifid ureter
2
1.56
None
99
77.34
4. Discussion
As with any retrospective study, our study had several limitations, including missing or insufficient information for some variables, which may have introduced information bias. Nevertheless, the available data allowed us to characterize the clinical and CT features of urinary stone disease in our setting and to compare our findings with those reported in the literature.
The mean age of patients in our study was 42.02 ± 17.02 years, which was close to the 39 years reported by Some et al.
[10]
Some MJM, Tankoano AI, Ouedraogo PA, Tonde KF, Kindo B, Zanga SM, Ouedraogo NA et al. Contribution of Computed Tomography to the Diagnosis of Urinary Lithiasis in a West African University Hospital. Open J Radiol. 2024; 14: 25–32.
in Burkina Faso in 2024. However, our mean age was higher than the 18.21 ± 21.86 years reported by Traore et al.
[7]
Traore MT, Kabore M, Ouedraogo S, et al. Epidemiology of Urinary Stone Disease in Northern Burkina Faso. Ann Universite Ouaga 1 Pr Joseph KI-ZERBO Vol 021; 2021.
[7]
in Burkina Faso in 2018 and the 33.85 years reported by Traore I.
[8]
Traore I. Epidemiological, Clinical, and Therapeutic Aspects of Urinary Stone Disease in the Urology Department of the Pr. Bocar Sidy Sall University Hospital in Kati: A Study of 81 Cases. Doctoral Dissertation in Medicine, University of Sciences, Techniques and Technologies of Bamako; 2019.
[8]
in Mali in 2019. These differences may reflect variations in the demographic characteristics of the study populations, recruitment settings, and inclusion criteria.
We observed a predominance of men, who accounted for 66.41% of the study population, with a male-to-female ratio of 1.97. This finding is consistent with that reported by Daudon et al. in France in 2008
[11]
Daudon M, Traxer O, Lechevallier E, et al. Epidemiology of Urinary Stone Disease. Prog En Urol 2008; 18: 802–814.
[11]
. It was also comparable to the 65.7% reported by Kabore et al.
[12]
Kabore FA, Kambou T, Zango B, et al. Epidemiology of a Cohort of 450 Cases of Urinary Stones at the Yalgado Ouédraogo University Hospital in Ouagadougou (Burkina Faso). Prog Urol. 2013; 23: 974–979.
[12]
in Burkina Faso in 2013 and close to the 59.1% reported by Opara et al.
[13]
Opara AO, Odzebe AWS, Atipo AO, et al. Upper Urinary Tract StonesEpidemiological, Diagnostic, and Therapeutic Aspects of 240 Cases at the Brazzaville University Hospital Center. Health Sci Dis; 20. 2019.
in Congo-Brazzaville. The male predominance observed in our study is consistent with the higher incidence of urinary stone disease traditionally reported in men. Several factors may contribute to this sex difference, including differences in hormonal, metabolic, dietary, and behavioral factors. In addition, organic conditions that may promote urinary stasis, such as prostatic hypertrophy, are more common in men. However, the mechanisms underlying the observed sex disparity are multifactorial and cannot be attributed solely to anatomical differences in the urinary tract.
Renal colic was the leading indication for CT in our study, accounting for 42.19% of cases. Similarly, Some et al.
[10]
Some MJM, Tankoano AI, Ouedraogo PA, Tonde KF, Kindo B, Zanga SM, Ouedraogo NA et al. Contribution of Computed Tomography to the Diagnosis of Urinary Lithiasis in a West African University Hospital. Open J Radiol. 2024; 14: 25–32.
Opara AO, Odzebe AWS, Atipo AO, et al. Upper Urinary Tract StonesEpidemiological, Diagnostic, and Therapeutic Aspects of 240 Cases at the Brazzaville University Hospital Center. Health Sci Dis; 20. 2019.
in Congo-Brazzaville reported renal colic as the most common indication, accounting for 28.2% and 59.16% of cases, respectively. In contrast, Odzebe et al.
[14]
Mali Medical. Medical news bulletin n°32b. 2010. Available from:
in Congo-Brazzaville reported acute urinary retention as the main presenting feature. These differences may reflect variations in the clinical characteristics of patients referred for imaging and in the anatomical location of the stones. Clinical manifestations of urinary stone disease vary according to stone location, size, and degree of urinary tract obstruction, with distinct presentations depending on whether the upper or lower urinary tract is involved.
The ureter was the most common site of stone localization in our study (43.75%), followed by the renal calyces (41.41%), whereas bladder stones accounted for 10.16% of cases. These findings are consistent with previous studies reporting the upper urinary tract as the predominant site of urinary stone formation
[8]
Traore I. Epidemiological, Clinical, and Therapeutic Aspects of Urinary Stone Disease in the Urology Department of the Pr. Bocar Sidy Sall University Hospital in Kati: A Study of 81 Cases. Doctoral Dissertation in Medicine, University of Sciences, Techniques and Technologies of Bamako; 2019.
[10]
Some MJM, Tankoano AI, Ouedraogo PA, Tonde KF, Kindo B, Zanga SM, Ouedraogo NA et al. Contribution of Computed Tomography to the Diagnosis of Urinary Lithiasis in a West African University Hospital. Open J Radiol. 2024; 14: 25–32.
. The predominance of ureteral stones in our series may partly reflect the clinical context in which CT was requested, particularly the high frequency of renal colic.
Right- and left-sided involvement were relatively similar, occurring in 41.40% and 40.62% of cases, respectively, while bilateral involvement was observed in 17.98%. A similar distribution has been reported in other African studies
[10]
Some MJM, Tankoano AI, Ouedraogo PA, Tonde KF, Kindo B, Zanga SM, Ouedraogo NA et al. Contribution of Computed Tomography to the Diagnosis of Urinary Lithiasis in a West African University Hospital. Open J Radiol. 2024; 14: 25–32.
Cisse M B. The Role of Imaging in the Diagnosis of Urinary Stones at the Hangadoumbo Moulaye Touré Hospital in Gao [medical dissertation]. Bamako: University of Sciences, Techniques and Technologies of Bamako; 2019.
[16]
Moise MV. Urinary lithiasis: epidemiological, clinic and therapeutic aspects at CNHU-HKM / Cotonou, Republic of Benin. J Med Res. 2021.
. In the absence of unilateral urinary tract abnormalities, there is no established anatomical or biological mechanism that would consistently favor stone formation on one side. The relatively balanced distribution observed in our study therefore appears consistent with the bilateral nature of the underlying metabolic and environmental risk factors for urinary stone disease.
Urinary tract impact was identified in 62.50% of patients, whereas 37.50% had no associated urinary tract abnormalities. Ureterohydronephrosis was the most frequent finding (39.85%), followed by calyceal dilatation (20.32%) and hydronephrosis (2.34%). In contrast, Benchouk
[17]
Benchouk M. Imaging of urinary stones: what the urologist expects for better management [Medical Dissertation]. Marrakech: Cadi Ayyad University; 2019.
[17]
reported hydronephrosis as the most common complication, occurring in 75.9% of cases. Differences in the distribution of complications may be related to variations in stone location, size, duration of obstruction, and the characteristics of the populations studied. In our study, the significant association observed between stone location and urinary tract impact (χ²(3) = 23.81; p < 0.001) further supports the importance of anatomical location in the development of obstructive urinary tract abnormalities. However, the cross-sectional nature of our data does not allow causal relationships to be established.
No statistically significant association was observed between stone composition and stone location (p = 0.746). This finding suggests that stone composition was not significantly related to its anatomical location within the urinary tract in our study population. Thus, the location of a stone in the renal calyces, renal pelvis, ureter, or bladder did not appear to be associated with a specific chemical composition. This finding is consistent with the multifactorial nature of urinary stone formation, which is influenced by metabolic, dietary, infectious, genetic, and environmental factors rather than by anatomical location alone. Stone location primarily reflects the site of formation, migration, and potential urinary obstruction. Therefore, anatomical location alone is unlikely to reliably predict stone composition
[11]
Daudon M, Traxer O, Lechevallier E, et al. Epidemiology of Urinary Stone Disease. Prog En Urol 2008; 18: 802–814.
[11]
.
Overall, our findings highlight the value of CT in the comprehensive assessment of urinary stone disease. Beyond detecting the presence of stones, CT provides information on their anatomical location, number, size, composition, and associated urinary tract abnormalities. These features are particularly relevant for assessing the severity of obstruction and informing therapeutic management.
5. Conclusions
Computed tomography plays a central role in the diagnosis and management of urinary stone disease. In our study, patients had a mean age of 42.02 ± 17.02 years, and renal colic was the most common indication for CT. Overall, CT reports provided the key information required to diagnose urinary stones and assess their anatomical location and associated urinary tract abnormalities. However, reporting was often incomplete regarding important characteristics such as stone density, morphology, and associated urinary tract malformations. Improving the standardization and completeness of CT reporting could enhance diagnostic characterization and support more appropriate therapeutic decision-making.
Abbreviations
CHUR-OHG
Ouahigouya Regional University Hospital Center
CT
Computed Tomography
Author Contributions
Milckisedek Judicael Marouruana Some: Conceptualization, Data curation, Formal Analysis, Methodology, Validation, Writing – original draft
Siebou Hien: Conceptualization, Data curation, Formal Analysis, Methodology, Validation
Ahryno Amad Yassine Diallo: Data curation, Formal Analysis, Methodology
Wendiwoumyam Judicael Congo: Data curation
Kouka Francois Dassis Tonde: Data curation
Tieoule Mamadou Traore: Visualization
Sore Moussa Zanga: Supervision
Data Availability Statement
The data supporting the outcome of this research work has been reported in this manuscript.
Conflicts of Interest
The authors declare no conflicts of interest.
References
[1]
Sorokin I, Mamoulakis C, Miyazawa K, et al. Epidemiology of stone disease across the world. World J Urol 2017; 35: 1301–1320.
Tasian GE, Ross ME, Song L, et al. Annual Incidence of Nephrolithiasis among Children and Adults in South Carolina from 1997 to 2012. Clin J Am Soc Nephrol CJASN 2016; 11: 488–496.
Hesse A, Brandle E, Wilbert D, et al. Study on the prevalence and incidence of urolithiasis in Germany comparing the years 1979 vs. 2000. Eur Urol 2003; 44: 709–713.
Traore MT, Kabore M, Ouedraogo S, et al. Epidemiology of Urinary Stone Disease in Northern Burkina Faso. Ann Universite Ouaga 1 Pr Joseph KI-ZERBO Vol 021; 2021.
[8]
Traore I. Epidemiological, Clinical, and Therapeutic Aspects of Urinary Stone Disease in the Urology Department of the Pr. Bocar Sidy Sall University Hospital in Kati: A Study of 81 Cases. Doctoral Dissertation in Medicine, University of Sciences, Techniques and Technologies of Bamako; 2019.
[9]
Francophone Society of Emergency Medicine (SFMU). 2008 Update of the 8th SFMU Consensus Conference 1999: Management of Renal Colic in Adults. Prog Urol. 2009; 19: 462–473.
[10]
Some MJM, Tankoano AI, Ouedraogo PA, Tonde KF, Kindo B, Zanga SM, Ouedraogo NA et al. Contribution of Computed Tomography to the Diagnosis of Urinary Lithiasis in a West African University Hospital. Open J Radiol. 2024; 14: 25–32.
Daudon M, Traxer O, Lechevallier E, et al. Epidemiology of Urinary Stone Disease. Prog En Urol 2008; 18: 802–814.
[12]
Kabore FA, Kambou T, Zango B, et al. Epidemiology of a Cohort of 450 Cases of Urinary Stones at the Yalgado Ouédraogo University Hospital in Ouagadougou (Burkina Faso). Prog Urol. 2013; 23: 974–979.
[13]
Opara AO, Odzebe AWS, Atipo AO, et al. Upper Urinary Tract StonesEpidemiological, Diagnostic, and Therapeutic Aspects of 240 Cases at the Brazzaville University Hospital Center. Health Sci Dis; 20. 2019.
Cisse M B. The Role of Imaging in the Diagnosis of Urinary Stones at the Hangadoumbo Moulaye Touré Hospital in Gao [medical dissertation]. Bamako: University of Sciences, Techniques and Technologies of Bamako; 2019.
[16]
Moise MV. Urinary lithiasis: epidemiological, clinic and therapeutic aspects at CNHU-HKM / Cotonou, Republic of Benin. J Med Res. 2021.
Benchouk M. Imaging of urinary stones: what the urologist expects for better management [Medical Dissertation]. Marrakech: Cadi Ayyad University; 2019.
Some, M. J. M., Hien, S., Diallo, A. A. Y., Congo, W. J., Tonde, K. F. D., et al. (2026). Contribution of Computed Tomography to the Diagnosis of Urinary Lithiasis at the Ouahigouya Regional University Hospital Center: A Study of 128 Cases (Burkina Faso). International Journal of Medical Imaging, 14(3), 26-31. https://doi.org/10.11648/j.ijmi.20261403.11
Some, M. J. M.; Hien, S.; Diallo, A. A. Y.; Congo, W. J.; Tonde, K. F. D., et al. Contribution of Computed Tomography to the Diagnosis of Urinary Lithiasis at the Ouahigouya Regional University Hospital Center: A Study of 128 Cases (Burkina Faso). Int. J. Med. Imaging2026, 14(3), 26-31. doi: 10.11648/j.ijmi.20261403.11
Some MJM, Hien S, Diallo AAY, Congo WJ, Tonde KFD, et al. Contribution of Computed Tomography to the Diagnosis of Urinary Lithiasis at the Ouahigouya Regional University Hospital Center: A Study of 128 Cases (Burkina Faso). Int J Med Imaging. 2026;14(3):26-31. doi: 10.11648/j.ijmi.20261403.11
@article{10.11648/j.ijmi.20261403.11,
  author = {Milckisedek Judicael Marouruana Some and Siebou Hien and Ahryno Amad Yassine Diallo and Wendiwoumyam Judicael Congo and Kouka Francois Dassis Tonde and Tieoule Mamadou Traore and Sore Moussa Zanga},
  title = {Contribution of Computed Tomography to the Diagnosis of Urinary Lithiasis at the Ouahigouya Regional University Hospital Center: A Study of 128 Cases (Burkina Faso)},
  journal = {International Journal of Medical Imaging},
  volume = {14},
  number = {3},
  pages = {26-31},
  doi = {10.11648/j.ijmi.20261403.11},
  url = {https://doi.org/10.11648/j.ijmi.20261403.11},
  eprint = {https://article.sciencepublishinggroup.com/pdf/10.11648.j.ijmi.20261403.11},
  abstract = {Objectives: To assess the diagnostic contribution of computed tomography (CT) in urinary stone disease at the Ouahigouya Regional University Hospital Center (CHUR-OHG), Burkina Faso, from May 2021 to December 31, 2024. Materials and Methods: We conducted a descriptive retrospective study over approximately four years, from May 1, 2021, to December 31, 2024. We reviewed the CT examinations performed for suspected urinary stone disease during the study period. Results: A total of 128 CT examinations were included. The male-to-female ratio was 1.97, and the mean age was 42.02 years. Renal colic was the most common indication for CT (42.19%). Stones were most frequently located in the ureter (36.72%). The main complications were ureterohydronephrosis (39.85%) and calyceal dilatation (20.32%), whereas no complications were observed in 37.50% of cases. CT most frequently identified calcium oxalate and uric acid stones, accounting for 29.68% and 28.13% of cases, respectively. Stone location was significantly associated with urinary tract obstruction or dilatation (p Conclusion: Computed tomography plays a central role in the diagnosis and therapeutic management of urinary stone disease. It provides valuable information on stone location, composition, and associated urinary tract complications.},
 year = {2026}
}
TY  - JOUR
T1  - Contribution of Computed Tomography to the Diagnosis of Urinary Lithiasis at the Ouahigouya Regional University Hospital Center: A Study of 128 Cases (Burkina Faso)
AU  - Milckisedek Judicael Marouruana Some
AU  - Siebou Hien
AU  - Ahryno Amad Yassine Diallo
AU  - Wendiwoumyam Judicael Congo
AU  - Kouka Francois Dassis Tonde
AU  - Tieoule Mamadou Traore
AU  - Sore Moussa Zanga
Y1  - 2026/10/09
PY  - 2026
N1  - https://doi.org/10.11648/j.ijmi.20261403.11
DO  - 10.11648/j.ijmi.20261403.11
T2  - International Journal of Medical Imaging
JF  - International Journal of Medical Imaging
JO  - International Journal of Medical Imaging
SP  - 26
EP  - 31
PB  - Science Publishing Group
SN  - 2330-832X
UR  - https://doi.org/10.11648/j.ijmi.20261403.11
AB  - Objectives: To assess the diagnostic contribution of computed tomography (CT) in urinary stone disease at the Ouahigouya Regional University Hospital Center (CHUR-OHG), Burkina Faso, from May 2021 to December 31, 2024. Materials and Methods: We conducted a descriptive retrospective study over approximately four years, from May 1, 2021, to December 31, 2024. We reviewed the CT examinations performed for suspected urinary stone disease during the study period. Results: A total of 128 CT examinations were included. The male-to-female ratio was 1.97, and the mean age was 42.02 years. Renal colic was the most common indication for CT (42.19%). Stones were most frequently located in the ureter (36.72%). The main complications were ureterohydronephrosis (39.85%) and calyceal dilatation (20.32%), whereas no complications were observed in 37.50% of cases. CT most frequently identified calcium oxalate and uric acid stones, accounting for 29.68% and 28.13% of cases, respectively. Stone location was significantly associated with urinary tract obstruction or dilatation (p Conclusion: Computed tomography plays a central role in the diagnosis and therapeutic management of urinary stone disease. It provides valuable information on stone location, composition, and associated urinary tract complications.
VL  - 14
IS  - 3
ER  -
Department of Nephrology and Hemodialysis, Ledea Bernard Ouedraogo University and Regional University Hospital Center of Ouahigouya, Ouahigouya, Burkina Faso
Department of Urology and Andrology, Ledea Bernard Ouedraogo University and Regional University Hospital Center of Ouahigouya, Ouahigouya, Burkina Faso
Some, M. J. M., Hien, S., Diallo, A. A. Y., Congo, W. J., Tonde, K. F. D., et al. (2026). Contribution of Computed Tomography to the Diagnosis of Urinary Lithiasis at the Ouahigouya Regional University Hospital Center: A Study of 128 Cases (Burkina Faso). International Journal of Medical Imaging, 14(3), 26-31. https://doi.org/10.11648/j.ijmi.20261403.11
Some, M. J. M.; Hien, S.; Diallo, A. A. Y.; Congo, W. J.; Tonde, K. F. D., et al. Contribution of Computed Tomography to the Diagnosis of Urinary Lithiasis at the Ouahigouya Regional University Hospital Center: A Study of 128 Cases (Burkina Faso). Int. J. Med. Imaging2026, 14(3), 26-31. doi: 10.11648/j.ijmi.20261403.11
Some MJM, Hien S, Diallo AAY, Congo WJ, Tonde KFD, et al. Contribution of Computed Tomography to the Diagnosis of Urinary Lithiasis at the Ouahigouya Regional University Hospital Center: A Study of 128 Cases (Burkina Faso). Int J Med Imaging. 2026;14(3):26-31. doi: 10.11648/j.ijmi.20261403.11
@article{10.11648/j.ijmi.20261403.11,
  author = {Milckisedek Judicael Marouruana Some and Siebou Hien and Ahryno Amad Yassine Diallo and Wendiwoumyam Judicael Congo and Kouka Francois Dassis Tonde and Tieoule Mamadou Traore and Sore Moussa Zanga},
  title = {Contribution of Computed Tomography to the Diagnosis of Urinary Lithiasis at the Ouahigouya Regional University Hospital Center: A Study of 128 Cases (Burkina Faso)},
  journal = {International Journal of Medical Imaging},
  volume = {14},
  number = {3},
  pages = {26-31},
  doi = {10.11648/j.ijmi.20261403.11},
  url = {https://doi.org/10.11648/j.ijmi.20261403.11},
  eprint = {https://article.sciencepublishinggroup.com/pdf/10.11648.j.ijmi.20261403.11},
  abstract = {Objectives: To assess the diagnostic contribution of computed tomography (CT) in urinary stone disease at the Ouahigouya Regional University Hospital Center (CHUR-OHG), Burkina Faso, from May 2021 to December 31, 2024. Materials and Methods: We conducted a descriptive retrospective study over approximately four years, from May 1, 2021, to December 31, 2024. We reviewed the CT examinations performed for suspected urinary stone disease during the study period. Results: A total of 128 CT examinations were included. The male-to-female ratio was 1.97, and the mean age was 42.02 years. Renal colic was the most common indication for CT (42.19%). Stones were most frequently located in the ureter (36.72%). The main complications were ureterohydronephrosis (39.85%) and calyceal dilatation (20.32%), whereas no complications were observed in 37.50% of cases. CT most frequently identified calcium oxalate and uric acid stones, accounting for 29.68% and 28.13% of cases, respectively. Stone location was significantly associated with urinary tract obstruction or dilatation (p Conclusion: Computed tomography plays a central role in the diagnosis and therapeutic management of urinary stone disease. It provides valuable information on stone location, composition, and associated urinary tract complications.},
 year = {2026}
}
TY  - JOUR
T1  - Contribution of Computed Tomography to the Diagnosis of Urinary Lithiasis at the Ouahigouya Regional University Hospital Center: A Study of 128 Cases (Burkina Faso)
AU  - Milckisedek Judicael Marouruana Some
AU  - Siebou Hien
AU  - Ahryno Amad Yassine Diallo
AU  - Wendiwoumyam Judicael Congo
AU  - Kouka Francois Dassis Tonde
AU  - Tieoule Mamadou Traore
AU  - Sore Moussa Zanga
Y1  - 2026/10/09
PY  - 2026
N1  - https://doi.org/10.11648/j.ijmi.20261403.11
DO  - 10.11648/j.ijmi.20261403.11
T2  - International Journal of Medical Imaging
JF  - International Journal of Medical Imaging
JO  - International Journal of Medical Imaging
SP  - 26
EP  - 31
PB  - Science Publishing Group
SN  - 2330-832X
UR  - https://doi.org/10.11648/j.ijmi.20261403.11
AB  - Objectives: To assess the diagnostic contribution of computed tomography (CT) in urinary stone disease at the Ouahigouya Regional University Hospital Center (CHUR-OHG), Burkina Faso, from May 2021 to December 31, 2024. Materials and Methods: We conducted a descriptive retrospective study over approximately four years, from May 1, 2021, to December 31, 2024. We reviewed the CT examinations performed for suspected urinary stone disease during the study period. Results: A total of 128 CT examinations were included. The male-to-female ratio was 1.97, and the mean age was 42.02 years. Renal colic was the most common indication for CT (42.19%). Stones were most frequently located in the ureter (36.72%). The main complications were ureterohydronephrosis (39.85%) and calyceal dilatation (20.32%), whereas no complications were observed in 37.50% of cases. CT most frequently identified calcium oxalate and uric acid stones, accounting for 29.68% and 28.13% of cases, respectively. Stone location was significantly associated with urinary tract obstruction or dilatation (p Conclusion: Computed tomography plays a central role in the diagnosis and therapeutic management of urinary stone disease. It provides valuable information on stone location, composition, and associated urinary tract complications.
VL  - 14
IS  - 3
ER  -

 ,
Siebou Hien,
Ahryno Amad Yassine Diallo,
Wendiwoumyam Judicael Congo,
Kouka Francois Dassis Tonde,
Tieoule Mamadou Traore,
Sore Moussa Zanga



 Share This Article
 Twitter
 Linked In
 Facebook

 Copy
 Download