
 ,
Magdalene Philip Umoh,
Tenneh Millicent Conteh,
Hassan Milton Conteh,
Abdul Bangura,
Rebecca Esliker,
Peter Agyei-Baffour,
Lee Presley Gary Jr.*
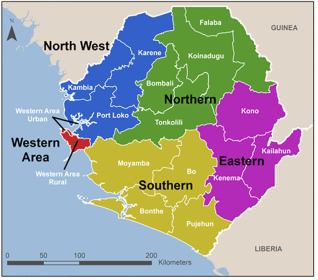
In this article, we examine the healthcare potential of the relationship between User/ Benefit Baskets (BB) and Provider/ Payment Options (PO) evolving in six (6) Regional Districts in Sierra Leone, an emerging country in West Africa, and detail how components of Benefit Baskets and Payment Options can impact the nature and scope of implementing a National Social Health Insurance Program in Sierra Leone. Identified and perceived relationships, as revealed by a cross-sectional study, are presented with contextual data from users and providers in the respective six districts. Quantitative data was collected (from August to December 2019) for this research study using a semi-structured questionnaire with a sample size of 1,503 respondents made up of 1,185 household heads and 318 healthcare providers. Data collection, which began during 2019, was analyzed into essential descriptive and inferential statistics. Statistical analysis was run at a significant 5% level using Stata vs 14.0 software. Our results reveal that factors such as marital status, religion, occupation, monthly income, and the district of residents in Sierra Leone were more likely to influence the magnitude of contributions for the content of a User/ Benefit Basket. In contrast, the selection of a Provider/ Payment Option by healthcare providers – such as Diagnostic-Related Grouping (DRG) and Fees-for-Service (FFS), were more likely to be influenced by the level of care provided by the healthcare providers and by the Regional District in which the service providers were situated and operated. Based on our findings, key contextual factors are most likely to influence the content of BBs and POs in Sierra Leone. Hence, we submit that it is appropriate for such contextual factors associated with BBs and POs to be adequately and rigorously considered upon the implementation of a National Social Health Insurance Program for the people of Sierra Leone.
| Published in | World Journal of Public Health (Volume 10, Issue 2) |
| DOI | 10.11648/j.wjph.20251002.17 |
| Page(s) | 140-154 |
| Creative Commons |
This is an Open Access article, distributed under the terms of the Creative Commons Attribution 4.0 International License (http://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, distribution and reproduction in any medium or format, provided the original work is properly cited. |
| Copyright |
Copyright © The Author(s), 2025. Published by Science Publishing Group |
National Social Health Insurance Program, Sierra Leone, Benefit Baskets, Payment Options, Capitation, Diagnostic Related-Grouping, Fees-for-Service, Healthcare Providers
District | Household Population (Hp) | Healthcare Facilities |
|---|---|---|
Kono | 505,491 | 78 |
Bombali | 605,741 | 96 |
Koinadugu | 408,687 | 53 |
Bo | 574,026 | 105 |
Western Area Rural | 443,068 | 60 |
Western Area Urban | 1,050,711 | 42 |
Total | 3,587,724 | 434 |
District | Household Population (Hp) | % Proportion By District (%Pd=Hp/Tp*100) | Sample Size for Each District (Szd=%Pd/100*1185) |
|---|---|---|---|
Kono | 505,491 | (505,491/3,587,724)100 = 14.09 | (14.09/100)1,185 = 167 |
Bombali | 605,741 | (605,741/3,587,724)100 = 16.88 | (16.88/100)1,185 = 200 |
Koinadugu | 408,687 | (408,687/3,587,724)100 = 11.39 | (11.39/100)1,185 = 135 |
Bo | 574,026 | (574,026/3,587,724)100 = 16 | (16/100)1,185 = 190 |
Western Area Rural | 443,068 | (443,068/3,587,724)100 = 12.35 | (12.35/100)1,185 = 146 |
Western Area Urban | 1,050,711 | (1,050,711/3,587,724)100 = 29.27 | (29.27/100)1,185 = 347 |
Total | 3,587,724 | 1,185 | |
Total Sample Size For Household Heads = 1,185 | |||
District | Health Services (Hs) | % Proportion Of Hs (%Phs=Hs/Ths*100) | Sample Size For Each District (Szd=%Ps/100*318) |
|---|---|---|---|
Total | Population / Proportion (2dp) | Total (to the nearest whole) | |
Kono | 78 | (78/434)100 = 17.97 | (17.97/100)318 = 57 |
Bombali | 96 | (96/434)100 = 22.12 | (22.12/100)318 = 70 |
Koinadugu | 53 | (53/434)100 = 12.21 | (12.21/100)318 = 39 |
Bo | 105 | (105/434)100 = 24.19 | (24.19/100)318 = 77 |
Western Area Urban | 60 | (60/434)100 = 13.82 | (13.82/100)318 = 44 |
Western Area Rural | 42 | (42/434)100 = 9.68 | (9.68/100)318 = 31 |
Total | 434 | 318 | |
Total Sample Size for Service Providers = 318 | |||
Variables | Frequency (n = 318) | Percentage (%) |
|---|---|---|
District | ||
Kono | 57 | 17.92 |
Bo | 77 | 24.21 |
Bombali | 70 | 22.01 |
Koinadugu | 39 | 12.26 |
W.A Urban | 44 | 13.84 |
W.A Rural | 31 | 9.75 |
Location of service providers in each district | ||
Rural Area | 200 | 62.89 |
Urban area | 118 | 37.11 |
Age category of service providers | ||
20-29 | 21 | 6.6 |
30-39 | 100 | 31.45 |
40-49 | 121 | 38.05 |
50+ | 76 | 23.9 |
Gender of healthcare providers | ||
Female | 263 | 82.7 |
Male | 55 | 17.3 |
Marital status of healthcare providers head | ||
Single | 108 | 33.96 |
Married | 177 | 55.66 |
Divorced | 17 | 5.35 |
Widow | 16 | 5.03 |
Healthcare providers partner status | ||
No Partner | 141 | 44.34 |
Has Partner | 177 | 55.66 |
The religion of healthcare providers head | ||
Islam | 190 | 59.75 |
Christianity | 128 | 40.25 |
Type of facility | ||
Public Facilities | 288 | 90.57 |
Private Facilities | 25 | 7.86 |
Mission Facilities | 5 | 1.57 |
Level Of Care Providers (multiple responses) | ||
primary care providers | ||
No | 10 | 3.14 |
Yes | 308 | 96.86 |
Secondary care providers | ||
No | 294 | 92.45 |
Yes | 24 | 7.55 |
Tertiary care providers | ||
No | 264 | 83.02 |
Yes | 54 | 16.98 |
Type of Care Provided by Facilities (multiple responses) | ||
Outpatient care providers | ||
No | 10 | 3.14 |
Yes | 308 | 96.86 |
Inpatient care providers | ||
No | 238 | 74.84 |
Yes | 80 | 25.16 |
Awareness of the SL/ NSHIP implementation | ||
No | 186 | 58.49 |
Yes | 132 | 41.51 |
Willingness for facility accreditation | ||
No | 0 | 0 |
Yes | 318 | 100 |
Level of confidence of healthcare providers in government for the sustainability of the SL/ NSHIP | ||
Not Confident | 57 | 17.92 |
Somehow Confident | 61 | 19.18 |
Confident | 96 | 30.19 |
Very Confident | 58 | 18.24 |
Highly Confident | 46 | 14.47 |
Variables | Frequency | Percentage (%) |
|---|---|---|
District of household heads | ||
Kono | 167 | 14.09 |
Bo | 190 | 16.03 |
Bombali | 200 | 16.88 |
Koinadugu | 135 | 11.39 |
Western Area Urban | 347 | 29.28 |
Western Area Rural | 146 | 12.32 |
Total | 1,185 | 100 |
Location of household heads | ||
Rural area | 364 | 30.72 |
Urban area | 821 | 69.28 |
Total | 1,185 | 100 |
Age categories of household heads | ||
20-29 | 105 | 8.86 |
30-39 | 517 | 43.63 |
40-49 | 354 | 29.87 |
50-59 | 177 | 14.94 |
60+ | 32 | 2.7 |
Total | 1,185 | 100 |
Female | 382 | 32.24 |
Male | 803 | 67.76 |
Total | 1,185 | 100 |
Marital status of household heads | ||
Single | 161 | 13.59 |
Married | 856 | 72.24 |
Divorced | 101 | 8.52 |
Widow | 67 | 5.65 |
Total | 1,185 | 100 |
The religion of household heads | ||
Islam | 561 | 47.34 |
Christianity | 624 | 52.66 |
Total | 1,185 | 100 |
Occupation of household heads | ||
Informal | 746 | 62.95 |
Formal | 439 | 37.05 |
Total | 1,185 | 100 |
Categories of household head Monthly income | ||
<Le 500,000 | 444 | 37.47 |
Le 500,000 - 1,000,000 | 418 | 35.27 |
> Le 1,000,000 | 323 | 27.26 |
Total | 1,185 | 100 |
Educational Qualification of household heads | ||
No formal education | 306 | 25.82 |
Primary school education | 158 | 13.33 |
Secondary school education | 248 | 20.93 |
Tertiary education | 473 | 39.92 |
Total | 1,185 | 100 |
Variables | Frequency (n = 318) | Percentage (%) |
|---|---|---|
Existing payment mechanism | ||
Salary | 316 | 99.37 |
Item line budget | 1 | 0.31 |
Stipend | 1 | 0.31 |
Challenges with existing payment mechanisms | ||
Delay | 127 | 39.94 |
High Administrative cost | 41 | 12.89 |
Insufficient funding | 146 | 45.91 |
Others (such as distance to assess banking facilities) | 4 | 1.26 |
Preferred Payment Mechanism by Facilities | ||
Capitation | ||
No | 249 | 78.3 |
Yes | 69 | 21.7 |
Diagnostic Related Grouping (DRG) | ||
No | 186 | 58.49 |
Yes | 132 | 41.51 |
Fees-for-Service (FFS) | ||
No | 115 | 36.16 |
Yes | 203 | 63.84 |
Preferred mode of payment by facilities | ||
After delivery of Service | 269 | 84.59 |
Before delivery of Service | 49 | 15.41 |
Healthcare providers that prefer SL/ NSHIP payment mechanism | ||
No | 27 | 8.49 |
Yes | 291 | 91.51 |
Variable | Obs | Mean | [95% Conf. Interval] | Null Hypothesis (HO) | P-value | |
|---|---|---|---|---|---|---|
Capitation | 318 | 0.21698 | (0.1716776 - 0.2622846) | p = 0.78 | 0.001 | |
DRG | 318 | 0.41509 | (0.3609378 - 0.4692509) | p = 0.58 | 0.001 | |
FFS | 318 | 0.63836 | (0.5855562 - 0.46911733) | p = 0.36 | 0.001 |
Premium Contribution | Coef. | Std. Err. | T | P-value | [95% Conf. Interval] |
|---|---|---|---|---|---|
District | -249.6119 | 360.5675 | -0.69 | 0.489 | (-957.0841 - 457.8602) |
Location | -150.6172 | 1215.777 | -0.12 | 0.901 | (-2536.103 - 2234.869) |
Age | -568.5682 | 667.6297 | -0.85 | 0.395 | (-1878.529 - 741.393) |
Gender | 619.7191 | 1248.3 | 0.5 | 0.62 | (-1829.579 - 3069.017) |
Marital status | 2354.553 | 934.2249 | 2.52 | 0.012* | (521.5038 - 4187.603) |
Religion | 2368.372 | 1172.754 | 2.02 | 0.044* | (67.30226 - 4669.441) |
Occupation | 4254.608 | 1800.822 | 2.36 | 0.018* | (721.2017 - 7788.014) |
Monthly Income | 2626.013 | 994.5848 | 2.64 | 0.008* | (674.5312 - 4577.496) |
Educational Qualification | -86.70056 | 683.6302 | -0.13 | 0.899 | (-1428.056 - 1254.655) |
Constant | 1256.98 | 3587.421 | 0.35 | 0.726 | (-5781.925 - 8295.884) |
Source | SS | Df | MS | Number of obs | =1,118 |
F (9, 1108) | =6.9 | ||||
Model | 2.07E+10 | 9 | 2.30E+09 | Prob > F | =0 |
Residual | 3.69E+11 | 1,108 | 333467296 | R-squared | =0.0531 |
Adj R-squared | =0.0454 | ||||
Total | 3.90E+11 | 1,117 | 349331294 | Root MSE | =18261 |
Variables | Logistic Regression | ||
|---|---|---|---|
Odds Ratio | P-value | [95% Conf. Interval] | |
District of service providers | [0.921] | ||
Kono | Ref | ||
Bo | 1.285656 | 0.606 | (0.4944886 - 3.342671) |
Bombali | 1.222022 | 0.656 | (0.5051425 - 2.956269) |
Koinadugu | 0.9942836 | 0.991 | (0.3587998 - 2.755297) |
W.A Urban | 1.943079 | 0.254 | (0.6208253 - 6.081509) |
W.A Rural | 0.7368918 | 0.599 | (0.2359417 - 2.301456) |
Location of service provider | [0.331] | ||
Rural Areas | Ref | ||
Urban Areas | 0.5518605 | 0.123 | (0.2592145 - 1.174896) |
Type of facility | [0.709] | ||
Public facility | Ref | ||
Private facility | 0.7639772 | 0.663 | (0.2279296 - 2.560708) |
Mission Facility | 3.134143 | 0.251 | (0.4453277 - 22.05758) |
Primary level of care providers | [0.94] | ||
No | Ref | ||
Yes | 1.147204 | 0.886 | (0.1757816 - 7.486998) |
Secondary level of care providers | [0.444] | ||
No | Ref | ||
Yes | 1.570583 | 0.445 | (0.4936168 - 4.997258) |
Tertiary level of care providers | [0.867] | ||
No | Ref | ||
Yes | 1.013994 | 0.975 | (0.4214988 - 2.439351) |
In-patient type of care providers | [0.072] | ||
No | Ref | ||
Yes | 0.4857326 | 0.061 | (0.2282467 - 1.033689) |
Out-patient type of care providers | [0.682] | ||
No | Ref | ||
Yes | 0.5491588 | 0.544 | (0.0790455 - 3.815211) |
Constant | 0.5044432 | 0.466 | (0.0800705 - 3.177988) |
Number of obs | = | 318 | |
LR chi2(13) | = | 9.09 | |
Prob > chi2 | = | 0.7662 | |
Log likelihood = -161.78906 | Pseudo R2 | = | 0.0273 |
Variables | Logistic Regression | ||
|---|---|---|---|
Odds Ratio | P-value | [95% Conf. Interval] | |
District of service providers | [0.568] | ||
Kono | Ref | ||
Bo | 0.9788765 | 0.958 | (0.4444398 - 2.15597) |
Bombali | 0.5026861 | 0.078 | (0.233989 - 1.079937) |
Koinadugu | 1.185926 | 0.686 | (0.5193771 - 2.707898) |
W.A Urban | 1.026891 | 0.955 | (0.4077885 - 2.58591) |
W.A Rural | 0.6626224 | 0.386 | (0.2611609 - 1.681218) |
Location of service provider | [0.252] | ||
Rural Areas | Ref | ||
Urban Areas | 1.151408 | 0.64 | (0.6375149 - 2.079545) |
Type of facility | [0.209] | ||
Public facility | Ref | ||
Private facility | 2.145768 | 0.109 | (0.8430757 - 5.461338) |
Mission Facility | 1.232203 | 0.834 | (0.1748335 - 8.684398) |
Primary level of care providers | [0.163] | ||
No | Ref | ||
Yes | 0.2191485 | 0.12 | (0.0323012 - 1.48682) |
Secondary level of care providers | [0.806] | ||
No | Ref | ||
Yes | 0.8215168 | 0.712 | (0.2897068 - 2.329562) |
Tertiary level of care providers | [0.009*] | ||
No | |||
Yes | 0.3627429 | 0.017* | (0.1580283 - 0.8326511) |
In-patient type of care providers | [0.54] | ||
No | Ref | ||
Yes | 0.889099 | 0.694 | (0.4949125 - 1.597246) |
Out-patient type of care providers | [0.296] | ||
No | Ref | ||
Yes | 3.730863 | 0.253 | (0.3897574 - 35.71284) |
Constant | 1.090435 | [0.93] | (0.1587249 - 7.491259) |
Number of obs | = | 318 | |
LR chi2(13) | = | 20.98 | |
Prob > chi2 | = | 0.0733 | |
Log likelihood = -205.32362 | Pseudo R2 | = | 0.0486 |
Variables | Logistic Regression | ||
|---|---|---|---|
Odds Ratio | P-value | [95% Conf. Interval] | |
District of service providers | [0.005*] | ||
Kono | Ref | ||
Bo | 0.7458587 | 0.506 | (0.3143512 - 1.769693) |
Bombali | 0.5235876 | 0.113 | (0.2352934 - 1.165115) |
Koinadugu | 0.5656218 | 0.214 | (0.2303578 - 1.388831) |
W.A Urban | 0.3682854 | 0.045* | (0.1386548 - 0.9782146) |
W.A Rural | 0.3100091 | 0.018* | (0.1178516 - 0.8154802) |
Location of service provider | [0.787] | ||
Rural Areas | Ref | ||
Urban Areas | 0.957369 | 0.888 | (0.523425 - 1.751073) |
Type of Facility | [0.404] | ||
Public facility | Ref | ||
Private facility | 1.080329 | 0.873 | (0.4183841 - 2.78957) |
Mission Facility | 3.344099 | 0.300 | (0.3415977 - 32.73734) |
Primary level of care providers | [0.701] | ||
No | Ref | ||
Yes | 0.6871094 | 0.671 | (0.1215856 - 3.883021) |
Secondary level of care providers | [0.811] | ||
No | Ref | ||
Yes | 1.121938 | 0.828 | (0.3977756 - 3.164457) |
Tertiary level of care providers | [0.160] | ||
No | Ref | ||
Yes | 0.6386174 | 0.240 | (0.3023336 - 1.348947) |
In-patient type of care providers | [0.560] | ||
No | Ref | ||
Yes | 1.226655 | 0.503 | (0.6744722 - 2.230903) |
Out-patient type of care providers | [0.457] | ||
No | Ref | ||
Yes | 1.920201 | 0.459 | (0.3416064 - 10.79363) |
Constant | 2.382632 | 0.309 | (0.446648 - 12.71009) |
Number of obs | =318 | ||
LR chi2(13) | =12.77 | ||
Prob > chi2 | =0.4657 | ||
Log likelihood = -201.69926 | Pseudo R2 | =0.0307 | |
BB | Benefit Basket |
DRG | Diagnostic-Related Grouping |
DHMT | District Health Management Team |
FFS | Fee-for-Service |
NHIS | National Health Insurance Scheme |
OOP | Out-of-Pocket |
PO | Payment Options |
SHI | Social Health Insurance |
UNIMAK | University of Makeni |
VPHI | Voluntary Private Health Insurance |
WHO | World Health Organization |
SL/ NSHIP | Sierra Leone / National Social Health Insurance Program |
| [1] | M. Yeboah-mensah, “The Socio-economic factors that effect utilization of health care services by the exempt groups under the National Health Insurance Scheme in Ghana (Doctoral Dissertation, University of Ghana).,” 2015. |
| [2] | J. Macha et al., “Factors influencing the burden of health care financing and the distribution of health care benefits in Ghana, Tanzania and South Africa,” Health Policy Plan, vol. 27, no. SUPPL.1, Mar. 2012, |
| [3] | E. Mossialos, A. Dixon, J. Figueras, and J. Kutzin, “Funding health care: options for Europe,” 2002. |
| [4] | R. B. Dixon and A. J. Hertelendy, “Interrelation of preventive care benefits and shared costs under the Affordable Care Act (ACA),” Int J Health Policy Manag, vol. 3, no. 3, pp. 145–148, 2014, |
| [5] | World Health Organization and World Health Organization, “Strategic Purchasing for Universal Health Coverage: Unlocking the Potential: Global Meeting Summary and Key Messages,” no. April 2017, 2017. |
| [6] | E. Etiaba, O. Onwujekwe, A. Honda, O. Ibe, B. Uzochukwu, and K. Hanson, “Strategic purchasing for universal health coverage: Examining the purchaser–provider relationship within a social health insurance scheme in Nigeria,” BMJ Glob Health, vol. 3, no. 5, Nov. 2018, |
| [7] | S. Mohammed, A. Souares, J. L. Bermejo, R. Sauerborn, and H. Dong, “Performance evaluation of a health insurance in Nigeria using optimal resource use: Health care providers perspectives,” BMC Health Serv Res, vol. 14, no. 1, 2014, |
| [8] | G. Carrin and C. James, “Social health insurance : Key factors affecting the transition towards universal coverage,” vol. 58, 2005. |
| [9] | P. J. Robyn et al., “Health worker preferences for community-based health insurance payment mechanisms: A discrete choice experiment,” BMC Health Serv Res, vol. 12, no. 1, 2012, |
| [10] | P. J. Robyn et al., “Provider payment methods and health worker motivation in community-based health insurance: A mixed-methods study,” Soc Sci Med, vol. 108, pp. 223–236, May 2014, |
| [11] | R. P. Ellis and M. M. Miller, “Provider Payment Methods and Incentives BT - Encyclopedia of Public Health,” Encyclopedia of Public Health, pp. 395–403, 2007, [Online]. Available: |
| [12] | R. P. Ellis, B. Martins, M. M. Miller, and M. Mckinnon Miller, “Provider Payment Methods and Incentives,” 2015. |
| [13] | K. Quinn, “The 8 basic payment methods in health care,” Ann Intern Med, vol. 163, no. 4, pp. 300–306, Aug. 2015, |
| [14] | J. S. Kazungu, J. Chuma, and M. Obadha, “What characteristics of provider payment mechanisms influence health care providers’ behaviour? A literature review,” no. June, pp. 892–905, 2018, |
| [15] | P. J. Robyn et al., “Health worker preferences for community-based health insurance payment mechanisms : a discrete choice experiment,” 2012. |
| [16] | O. Onwujekwe, E. Okereke, C. Onoka, B. Uzochukwu, J. Kirigia, and A. Petu, “Willingness to pay for community-based health insurance in Nigeria : do economic status and place of residence matter ?,” no. October 2009, pp. 155–161, 2010, |
| [17] | T. Bärnighausen, Y. Liu, X. Zhang, and R. Sauerborn, “Willingness to pay for social health insurance among informal sector workers in Wuhan, China: A contingent valuation study,” BMC Health Serv Res, vol. 7, pp. 1–16, 2007, |
| [18] | M. T. Gidey, G. B. Gebretekle, M. E. Hogan, and T. G. Fenta, “Willingness to pay for social health insurance and its determinants among public servants in Mekelle City, Northern Ethiopia: A mixed methods study,” Cost Effectiveness and Resource Allocation, vol. 17, no. 1, pp. 1–11, 2019, |
APA Style
Jimmy, A. I., Umoh, M. P., Conteh, T. M., Conteh, H. M., Bangura, A., et al. (2025). Contrasting User Benefit Baskets and Provider Payment Options Seeking National Social Health Insurance Choices in Selected Districts for Sierra Leone. World Journal of Public Health, 10(2), 140-154. https://doi.org/10.11648/j.wjph.20251002.17
ACS Style
Jimmy, A. I.; Umoh, M. P.; Conteh, T. M.; Conteh, H. M.; Bangura, A., et al. Contrasting User Benefit Baskets and Provider Payment Options Seeking National Social Health Insurance Choices in Selected Districts for Sierra Leone. World J. Public Health 2025, 10(2), 140-154. doi: 10.11648/j.wjph.20251002.17
AMA Style
Jimmy AI, Umoh MP, Conteh TM, Conteh HM, Bangura A, et al. Contrasting User Benefit Baskets and Provider Payment Options Seeking National Social Health Insurance Choices in Selected Districts for Sierra Leone. World J Public Health. 2025;10(2):140-154. doi: 10.11648/j.wjph.20251002.17
@article{10.11648/j.wjph.20251002.17,
  author = {Abraham Isiaka Jimmy and Magdalene Philip Umoh and Tenneh Millicent Conteh and Hassan Milton Conteh and Abdul Bangura and Rebecca Esliker and Peter Agyei-Baffour and Lee Presley Gary Jr.},
  title = {Contrasting User Benefit Baskets and Provider Payment Options Seeking National Social Health Insurance Choices in Selected Districts for Sierra Leone
},
  journal = {World Journal of Public Health},
  volume = {10},
  number = {2},
  pages = {140-154},
  doi = {10.11648/j.wjph.20251002.17},
  url = {https://doi.org/10.11648/j.wjph.20251002.17},
  eprint = {https://article.sciencepublishinggroup.com/pdf/10.11648.j.wjph.20251002.17},
  abstract = {In this article, we examine the healthcare potential of the relationship between User/ Benefit Baskets (BB) and Provider/ Payment Options (PO) evolving in six (6) Regional Districts in Sierra Leone, an emerging country in West Africa, and detail how components of Benefit Baskets and Payment Options can impact the nature and scope of implementing a National Social Health Insurance Program in Sierra Leone. Identified and perceived relationships, as revealed by a cross-sectional study, are presented with contextual data from users and providers in the respective six districts. Quantitative data was collected (from August to December 2019) for this research study using a semi-structured questionnaire with a sample size of 1,503 respondents made up of 1,185 household heads and 318 healthcare providers. Data collection, which began during 2019, was analyzed into essential descriptive and inferential statistics. Statistical analysis was run at a significant 5% level using Stata vs 14.0 software. Our results reveal that factors such as marital status, religion, occupation, monthly income, and the district of residents in Sierra Leone were more likely to influence the magnitude of contributions for the content of a User/ Benefit Basket. In contrast, the selection of a Provider/ Payment Option by healthcare providers – such as Diagnostic-Related Grouping (DRG) and Fees-for-Service (FFS), were more likely to be influenced by the level of care provided by the healthcare providers and by the Regional District in which the service providers were situated and operated. Based on our findings, key contextual factors are most likely to influence the content of BBs and POs in Sierra Leone. Hence, we submit that it is appropriate for such contextual factors associated with BBs and POs to be adequately and rigorously considered upon the implementation of a National Social Health Insurance Program for the people of Sierra Leone.
},
 year = {2025}
}
TY  - JOUR
T1  - Contrasting User Benefit Baskets and Provider Payment Options Seeking National Social Health Insurance Choices in Selected Districts for Sierra Leone

AU  - Abraham Isiaka Jimmy
AU  - Magdalene Philip Umoh
AU  - Tenneh Millicent Conteh
AU  - Hassan Milton Conteh
AU  - Abdul Bangura
AU  - Rebecca Esliker
AU  - Peter Agyei-Baffour
AU  - Lee Presley Gary Jr.
Y1  - 2025/06/18
PY  - 2025
N1  - https://doi.org/10.11648/j.wjph.20251002.17
DO  - 10.11648/j.wjph.20251002.17
T2  - World Journal of Public Health
JF  - World Journal of Public Health
JO  - World Journal of Public Health
SP  - 140
EP  - 154
PB  - Science Publishing Group
SN  - 2637-6059
UR  - https://doi.org/10.11648/j.wjph.20251002.17
AB  - In this article, we examine the healthcare potential of the relationship between User/ Benefit Baskets (BB) and Provider/ Payment Options (PO) evolving in six (6) Regional Districts in Sierra Leone, an emerging country in West Africa, and detail how components of Benefit Baskets and Payment Options can impact the nature and scope of implementing a National Social Health Insurance Program in Sierra Leone. Identified and perceived relationships, as revealed by a cross-sectional study, are presented with contextual data from users and providers in the respective six districts. Quantitative data was collected (from August to December 2019) for this research study using a semi-structured questionnaire with a sample size of 1,503 respondents made up of 1,185 household heads and 318 healthcare providers. Data collection, which began during 2019, was analyzed into essential descriptive and inferential statistics. Statistical analysis was run at a significant 5% level using Stata vs 14.0 software. Our results reveal that factors such as marital status, religion, occupation, monthly income, and the district of residents in Sierra Leone were more likely to influence the magnitude of contributions for the content of a User/ Benefit Basket. In contrast, the selection of a Provider/ Payment Option by healthcare providers – such as Diagnostic-Related Grouping (DRG) and Fees-for-Service (FFS), were more likely to be influenced by the level of care provided by the healthcare providers and by the Regional District in which the service providers were situated and operated. Based on our findings, key contextual factors are most likely to influence the content of BBs and POs in Sierra Leone. Hence, we submit that it is appropriate for such contextual factors associated with BBs and POs to be adequately and rigorously considered upon the implementation of a National Social Health Insurance Program for the people of Sierra Leone.

VL  - 10
IS  - 2
ER  -
Department of Public Health, University of Makeni, Makeni, Sierra Leone; College of Heath Sciences, University of Moi, Eldoret, Kenya
Biography: Abraham Isiaka Jimmy is a Public Health Specialist and Re-searcher. He has more than six years of experience working in emergency and development contexts in Sierra Leone and has de-veloped strong competencies in health program management. He teaches public health and mental health courses at the University of Makeni, located in the City of Makeni in Sierra Leone. He advises on the operationalisation of One Health Programs, including devel-oping policies, strategies, and governance for mitigating public health challenges.
Research Fields: Public Health Policy, Health System Financing, Healthcare Econom-ics, Public Mental Health Policy, Maternal Child Health, Occupa-tional Health Safety & Regulations, and Environmental Health Risks & Assessments.
Department of Public Health, University of Makeni, Makeni, Sierra Leone
Biography: Magdalene Philip Umoh is a Public Health Scholar with expertise in Occupational/Environmental Health and Safety. She is a faculty lecturer for the Department of Public Health at the University of Makeni, located in Makeni, Sierra Leone, and serves as Director of the Center of Excellence in Maternal and Child Health Education and Research. Her vast experience with public and community health issues covers over ten years. including lecturing, researching, and consulting with the Food and Agricultural Organization (FAO), Ministry of Agriculture, and various Human Capital Development Plans (HCD Plus). She is passionate about transforming public health outcomes with a keen focus on women and children.
Research Fields: Maternal Healthcare, Occupational Health Safety & Regulations, Environmental Health Risk & Assessments, Public Health Policy, Infectious Diseases, and Nursing Profession Education & Career Development.
Medicine San Frontières (MSF) Holland, Magburaka, Sierra Leone
Research Fields: Public Health Management, Health Policy Issues Development & Strategy, Occupational Health Safety & Regulations, Environmental Health Challenges & Training, and Infectious Diseases Surveillance & Monitoring.
Medicine San Frontières (MSF) Holland, Magburaka, Sierra Leone
Research Fields: Public Health Management, Healthcare Psychology Issues & Treat-ment, Environmental Health Challenges & Training, Communicable Diseases, and Health Policy Issue Development & Strategy.
Ministry of Health and Sanitation, Freetown, Sierra Leone
Research Fields: Community Health Administration & Promotion, Infectious Disease Surveillance & Treatment, Maternal Health Care & Services, Envi-ronmental Health Safety & Regulations, and Public Health Policy & Programs.
Department of Public Health, University of Makeni, Makeni, Sierra Leone
Research Fields: Higher Education Leadership & Administration, Public Health Cur-riculum & Training, Communicable and Non-communicable Diseas-es, Population Health Awareness & Surveillance, and Disaster man-agement.
Department of Health Policy and Management, Kwame Nkrumah University of Science and Technology, Kumasi, Ghana
Research Fields: Public Health Equity & Stewardship, Healthcare System Financing & Administration, Healthcare Economics, Population Health, Occupa-tional/ Environmental Health and Safety Policy, Mitigating Com-municable and Non-Communicable Diseases.
Department of Public Health, University of Makeni, Makeni, Sierra Leone; University of Makeni, Makeni, Sierra Leone; Strategic Management Services - USA, New Orleans, USA
Biography: Lee Presley Gary Jr. is a Visiting Research Scholar at the Univer-sity of Makeni, located in the City of Makeni in Sierra Leone, and he is Owner/CEO of Strategic Management Services – USA, a global consultancy specializing in mitigating public health threats and hazards associated with dirty water and human waste, and served as a Fulbright Specialist at the University of Makeni teach-ing public health courses during 2024. He is an active member of the Water Environment Federation and is an adjunct instructor for the National Disaster & Emergency Management University (Em-mitsburg, MD). He was named a Fulbright Scholar at the Univer-sity of Malta for 2025-2026.
Research Fields: Disaster Management, Emergency Management, and Mitigation of Dirty Water and Human Waste.

Information


 Share This Article
 Twitter
 Linked In
 Facebook

 Copy
 Download