
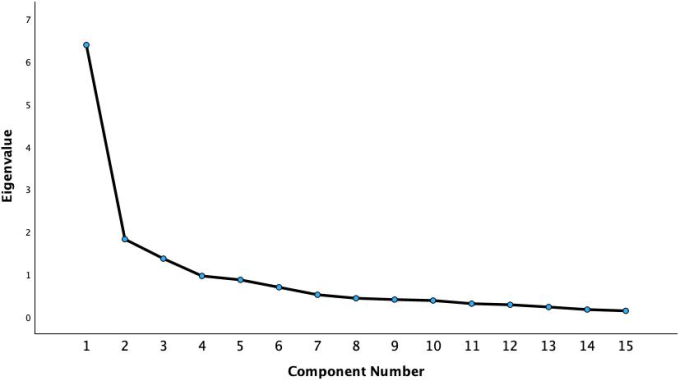
Objective: To develop and validate an assessment scale for primary trigeminal neuralgia (PTN) that is suitable for Chinese patients’ clinical requirements and cultural background. Methods: Descriptive study. (1) Construction of pre-scales: A pool of scale entries was prepared based on the common clinical features of PTN, the consensus of domestic experts, clinical diagnosis and treatment guidelines, and the reference of the international scale production process. Based on the Delphi method, 21 experts were invited to participate in two rounds of correspondence and pre-test revisions to develop the pre-scales. (2) Formation and validation of the preliminary version of the scale: A clinical investigation was conducted on 157 patients with PTN in the Pain Department of Shandong Provincial Hospital from March 20, 2024 to January 1, 2025. The entries were screened to form a preliminary version of the scale using the critical ratio method, correlation coefficient method, and discrete trend method. The scientific validity and feasibility of the scale were then assessed through reliability and validity tests, satisfaction measurements, and reflective tests. Results: 147 patients with PTN completed the study. The positive coefficient of two rounds of expert correspondence was 100.0%, the authoritative coefficient was 0.927 and 0.957 (>0.900), the Kendall's W coefficient was 0.227 and 0.421, respectively (all P<0.001). The validity and reliability of the scale were positive, with Cronbach's α 0.870 (>0.700), the content validity index 0.935 (>0.900) for S-CVI and 0.810-1.000 (all≥0.780) for I-CVI respectively, the Kaiser-Meyer-Olkin (KMO) value 0.858 (>0.600), and χ2=1 220.060 (P<0.001) of Bartlett spherical test. The exploratory factor analysis extracted 3 common factors, with a cumulative variance contribution rate of 63.880% (>50.000%) and factor loadings ranging between 0.533 and 0.905 for each entry. The correlation coefficient (r) between satisfaction and change before and after the treatment was 0.903. The scale demonstrated excellent responsiveness, as evidenced by a standardized response median (SRMed) of 2.71 and an effect size (ES) of 3.17 (both substantially exceeding the established benchmark of >0.80). The final scale consisted of 4 parts: the first part with 6 non-quantitative entries, the second part contained 4 dimensions and 20 quantitative entries, the third part contained 5 entries related to post-treatment evaluation, the fourth part was the overall satisfaction evaluation with 5 entries, and the third and fourth parts were for post-treatment only. Conclusion: The primary trigeminal neuralgia assessment scale has good reliability, validity, and applicability.
| Published in | International Journal of Pain Research (Volume 1, Issue 4) |
| DOI | 10.11648/j.ijpr.20250104.13 |
| Page(s) | 87-106 |
| Creative Commons |
This is an Open Access article, distributed under the terms of the Creative Commons Attribution 4.0 International License (http://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, distribution and reproduction in any medium or format, provided the original work is properly cited. |
| Copyright |
Copyright © The Author(s), 2025. Published by Science Publishing Group |
Primary Trigeminal Neuralgia, Pain Measurement, Scale, Chinese Version, Development, Reliability and Validity
Round | Ca | Cs | Cr | Cv | Kendall’s W |
|---|---|---|---|---|---|
1 | 0.967 | 0.886 | 0.927 | 0~0.257 | 0.227 |
2 | 0.962 | 0.952 | 0.957 | 0~0.223 | 0.421 |
Item- Number | Item Content | Cronbach’s α | McDonald’s ω |
|---|---|---|---|
Q1 | How severe was your most intense facial pain? recently? | 0.870 | 0.871 |
Q2 | How would you rate your mildest facial pain recently? | ||
Q3 | How would you rate your average facial pain recently? | ||
Q4 | Does your pain worsen with weather/environmental changes? | ||
Q5 | Does your pain worsen with fatigue/emotional stress? | ||
Q6 | Does voluntary facial movement (speaking, chewing, expressions) trigger your pain? | ||
Q7 | Does light touch/stretching of facial areas (gums, lips, ala nasi, cheeks, periorbital regions) trigger pain? | ||
Q8 | (Physician's examination) When comparing light touch on affected vs. unaffected facial skin, do you experience reduced sensation in the pain area? If yes, select the degree | ||
Q9 | Do you feel anxious, tense, or restless due to facial pain recently? | ||
Q10 | Do you feel depressed, discouraged, or helpless due to facial pain recently? | ||
Q11 | Do you feel fatigued or lacking energy due to facial pain recently? | ||
Q12 | Does facial pain cause difficulty concentrating (e.g., when using phones/watching TV)? | ||
Q13 | Does facial pain make you feel worthless, like a failure, or that you've let down yourself/family? | ||
Q14 | Have you ever felt unable to cope, had thoughts of dying, or self-harm due to facial pain? | ||
Q15 | Does facial pain affect your sleep quality? | ||
Q16 | Do you wake up from sleep due to facial pain? | ||
Q17 | Does pain affect daily activities (washing, eating, speaking, smiling)? | ||
Q18 | Do negative emotions from pain (depression, helplessness, anxiety) affect your work/life (job, socializing, chores)? | ||
Q19 | Does pain affect your social interactions with family/friends/colleagues? | ||
Q20 | Is facial pain accompanied by facial/masticatory muscle spasms/twitching? | ||
Q21 | Is facial pain accompanied by conjunctival congestion and/or tearing? | ||
Q22 | Is facial pain accompanied by salivation? | ||
Q23 | What is your recent pain attack frequency? | ||
Q24 | What is your recent pain attack duration? |
Item | Factor | ||
|---|---|---|---|
1 | 2 | 3 | |
Q12 | 0.805 | ||
Q13 | 0.759 | ||
Q11 | 0.674 | ||
Q15 | 0.673 | ||
Q14 | 0.649 | ||
Q16 | 0.642 | ||
Q9 | 0.533 | 0.501 | |
Q10 | 0.542 | 0.653 | |
Q17 | 0.850 | ||
Q7 | 0.762 | ||
Q6 | 0.656 | ||
Q19 | 0.595 | ||
Q18 | 0.585 | ||
Q1 | 0.905 | ||
Q3 | 0.890 | ||
Scale | Pre-Treatment (Points) | Pre-Post Change (Points) | Z-value | P-value | CR | ES | SRMed |
|---|---|---|---|---|---|---|---|
Preliminary Version Scale | 81.67 (66.49, 90.16) | 76.84 (59.33, 87.67) | 10.518 | <0.001 | 0.94 | 3.17 | 2.71 |
PTN | Primary Trigeminal Neuralgia |
STN | Secondary Trigeminal Neuralgia |
ICHD-3 | The International Classification of Headache Disorders, 3rd edition |
VAS | Visual Analogue Scale |
NRS | Numerical Rating Scale |
DN-4 | Douleur Neuropathique 4 |
LANSS | Leeds Assessment of Neuropathic Pain Symptoms and Signs Scale |
SF-36 | Medical Outcomes Study 36-item Short form Health Survey |
HADS | Hospital Anxiety and Depression Scale |
PSQI | Pittsburgh Sleep Quality Index |
IQR | Interquartile Range |
CR | Critical Ratio |
CV | Coefficient of Variation |
Ca | Certainty Assessment |
Cs | Certainty of Source |
Cr | Credibility Coefficient |
CR | Change Rate |
SD | Standard Deviation |
CITC | Corrected Item-Total Correlation |
I-CVI | Item-level Content Validity Index |
S-CVI | Scale-level Content Validity Index |
KMO | Kaiser-Meyer-Olkin |
SRMed | Standardized Response Median |
ES | Effect Size |
PRO | Patient-Reported Outcomes |
ADRs | Adverse Drug Reactions |
ADL | Activities of Daily Living |
CNS | Central Nervous System |
GI | Gastrointestinal |
Name: Gender: Age: Hospital ID: Contact: | |
To accurately evaluate and effectively treat your condition, please provide truthful responses to the following questions. Mark "√" in the box that best reflects your actual situation. | |
I. Patient Demographic Data 1. Affected Side: □Left □Right 2. Branch Involvement: □V1 □V2 □V3 □V1+V2 □V2+V3 □V1+V2+V3 3. Pain Characteristics: □Electric shock-like □Tearing-like □Stabbing-like □Needle-prick-like □Burning-like 4. Attack Frequency: □< 10 times/day □10-50 times/day □≥ 50 times/day 5. Attack Duration: □< 1 min □1-10 min □≥ 10 min 6. Disease Course: □<6 months □ ≥6 months, <1 year □≥1 year, <3 years □ ≥3 years, <5 years □≥5 years, <10 years □ ≥10 years, <20 years □≥20 years 7. Remission Period: □< 1 week □ ≥1 week, <1 month □≥1 months, <6 months □ ≥6 months, <1 year □ 1-5 years □ 5-10 years □ > 10 years | 8. Current Analgesic Use (Check pain relief rate and specify medications): (No relief) 0 10% 20% 30% 40% 50% 60% 70% 80% 90% 100% (Complete relief) (1) First-line: □Carbamazepine □Oxcarbazepine (2) Second-line: □ Pregabalin □ Gabapentin □ Baclofen □ Lamotrigine (3) Others: □ Ibuprofen □ Tramadol □ Diclofenac sodium □ Paracetamol/Dihydrocodeine □ Duloxetine □ Venlafaxine □ Oxycodone □ Other (_________) 9. Prior Non-pharmacological Interventions (Check pain relief rate and specify procedure): (No relief) 0 10% 20% 30% 40% 50% 60% 70% 80% 90% 100% (Complete relief) □ Percutaneous Radiofrequency Thermocoagulation of Trigeminal Ganglion □ Meckel's Cave Balloon Compression □ Meckel's Cave Glycerol Rhizotomy □ Nerve Block Therapy □ Microvascular Decompression □ Gamma Knife Radiosurgery □ Other (__________________________) |
To ensure accurate assessment and effective treatment of your condition, please answer the following questions truthfully based on your experiences over the past week. Mark "√" next to the option that best reflects your actual situation. 0 = No pain; 1-3 = Mild pain; 4-6 = Moderate pain; 7-9 = Severe pain; 10 = Excruciating pain | |
II. Pain Assessment (Total 22 items, 220 points) (I) Symptoms and Signs 1. How severe was your most intense facial pain? (No pain) 0 1 2 3 4 5 6 7 8 9 10 (Unbearable pain) 2. How would you rate your mildest facial pain recently? (No pain) 0 1 2 3 4 5 6 7 8 9 10 (Unbearable pain) 3. How would you rate your average facial pain recently? (No pain) 0 1 2 3 4 5 6 7 8 9 10 (Unbearable pain) 4. Does your pain worsen with weather/environmental changes? 0- No (0 pt) 1- Yes (10 pt) 5. Does your pain worsen with fatigue/emotional stress? 0- No (0 pt) 1- Yes (10 pt) 6. Does voluntary facial movement (speaking, chewing, expressions) trigger your pain? 0-Never (0 pt) 1-Occasionally mild (2.5 pt) 2-Moderately in 50% cases (5 pt) 3-Severely in most cases (7.5 pt) 4-Very severe in nearly all attacks (10 pt) 7. Does light touch/stretching of facial areas (gums, lips, ala nasi, cheeks, periorbital regions) trigger pain? 0-Never (0 pt) 1-Occasionally mild (2.5 pt) 2-Moderately in 50% cases (5 pt) 3-Severely in most cases (7.5 pt) 4-Very severe in nearly all attacks (10 pt) 8. (Physician's examination) When comparing light touch on affected vs. unaffected facial skin, do you experience reduced sensation in the pain area? If yes, select the degree. 0 1 2 3 4 5 6 7 8 9 10 (II) Accompanying symptoms 9. Is facial pain accompanied by facial/masticatory muscle spasms/twitching? 0- No (0 pt) 1- Yes (10 pt) 10. Is facial pain accompanied by conjunctival congestion and/or tearing? 0- No (0 pt) 1- Yes (10 pt) 11. Is facial pain accompanied by salivation? 0- No (0 pt) 1- Yes (10 pt) 12. Have you ever felt unable to cope, had thoughts of dying, or self-harm due to facial pain? 0-Never (0 pt) 1-Sometimes (2.5 pt) 2-Half the time (5 pt) 3-Mostly (7.5 pt) 4-Nearly daily (10 pt) 13. Does facial pain make you feel worthless, like a failure, or that you've let down yourself/family? 0-Never (0 pt) 1-Sometimes (2.5 pt) 2-Half the time (5 pt) 3-Mostly (7.5 pt) 4-Nearly daily (10 pt) 14. Do you feel fatigued or lacking energy due to facial pain recently? 0-Never (0 pt) 1-Sometimes (2.5 pt) 2-Half the time (5 pt) 3-Mostly (7.5 pt) 4-Nearly daily (10 pt) | 15. Does facial pain cause difficulty concentrating (e.g., when using phones/watching TV)? 0-Never (0 pt) 1-Sometimes (2.5 pt) 2-Half the time (5 pt) 3-Mostly (7.5 pt) 4-Nearly daily (10 pt) 16. Do you feel anxious, tense, or restless due to facial pain recently? 0-Never (0 pt) 1-Sometimes (2.5 pt) 2-Half the time (5 pt) 3-Mostly (7.5 pt) 4-Nearly daily (10 pt) 17. Do you feel depressed, discouraged, or helpless due to facial pain recently? 0-Never (0 pt) 1-Sometimes (2.5 pt) 2-Half the time (5 pt) 3-Mostly (7.5 pt) 4-Nearly daily (10 pt) 18. Does facial pain affect your sleep quality? 0-No effect (0 pt) 1-Occasional disturbance (2.5 pt) 2-< 6 hrs sleep/night (5 pt) 3-< 4 hrs sleep/night (7.5 pt) 4-< 2 hrs sleep/night (10 pt) 19. Do you wake up from sleep due to facial pain? 0-Never (0 pt) 1-Rarely (2.5 pt) 2-≥1 time/month (5 pt) 3-≥1 time/week (7.5 pt) 4-Almost nightly (10 pt) 20. Does pain affect daily activities (washing, eating, speaking, smiling)? 0- No impact (0 pt) 1- Minimal impact (manageable without intervention) (2.5 pt) 2- Moderate impact (disruptive but daily activities sustainable) (5 pt) 3- Severe impact (requires cessation of activities) (7.5 pt) 4- Complete disability (unable to perform any routine tasks) (10 pt) 21. Do negative emotions from pain (depression, helplessness, anxiety) affect your work/life (job, socializing, chores)? 0- No impact (0 pt) 1- Minimal impact (manageable without intervention) (2.5 pt) 2- Moderate impact (disruptive but daily activities sustainable) (5 pt) 3- Severe impact (requires cessation of activities) (7.5 pt) 4- Complete disability (unable to perform any routine tasks) (10 pt) 22. Does pain affect your social interactions with family/friends/colleagues? 0- No impairment (0 pt) 1- Minimal impact (noticeable but ignorable) (2.5 pt) 2- Moderate impact (disruptive yet sustainable with effort) (5 pt) 3- Severe impact (requires social withdrawal) (7.5 pt) 4- Complete social disability (functionally isolated) (10 pt) |
To ensure precise evaluation and effective treatment of your condition, please provide truthful and accurate responses to the following questions. Mark "✓" next to the option that best corresponds to your actual situation. | |
III. Post-treatment Evaluation (Total 5 items, 50 points) 1. Adverse drug reactions (ADRs) from first-line therapy? (Cumulative scoring) 0- No ADRs or resolved spontaneously (0 pt) 1- CNS reactions (dizziness, headache, ataxia, somnolence, fatigue, diplopia) (3.33 pt) 2- GI disturbances (nausea, vomiting) (3.33 pt) 3- Cutaneous hypersensitivity (3.33 pt) 2. Surgical complications? (Cumulative scoring) 0- No complications or transient (0 pt) 1- Hypoesthesia (2 pt) 2- Non-specific complaints (2 pt) 3- Dysesthesia (2 pt) 4- Keratitis (2 pt) 5- Anesthesia dolorosa (2 pt) 3. Impact of ADRs/complications on daily living? 0- No impact (0 pt) 1- Minimal impact (2.5 pt) 2- Mild impact (5 pt) 3- Severe impact (7.5 pt) 4- Complete disability (10 pt) 4. Does sleep disturbance occur due to treatment-related adverse effects or complications? 0-No effect (0 pt) 1-Occasional disturbance (2.5 pt) 2-< 6 hrs sleep/night (5 pt) 3-< 4 hrs sleep/night (7.5 pt) 4-< 2 hrs sleep/night (10 pt) 5. Has your emotional state been altered due to treatment-related adverse effects or complications? 0- None (0 pt) 1- Sometimes (2.5 pt) 2- Half the time (5 pt) 3- Mostly (7.5 pt) 4- Nearly daily (10 pt) | IV. Overall Satisfaction Assessment (Total 5 items, 50 points) 1. Overall treatment satisfaction? 0- Very satisfied (0 pt) 1- Somewhat satisfied (2.5 pt) 2- Neutral (5 pt) 3- Somewhat dissatisfied (7.5 pt) 4- Very dissatisfied (10 pt) 2. Pain intensity improvement? 0- Very satisfied (0 pt) 1- Somewhat satisfied (2.5 pt) 2- Neutral (5 pt) 3- Somewhat dissatisfied (7.5 pt) 4- Very dissatisfied (10 pt) 3. Sleep improvement? 0- Very satisfied (0 pt) 1- Somewhat satisfied (2.5 pt) 2- Neutral (5 pt) 3- Somewhat dissatisfied (7.5 pt) 4- Very dissatisfied (10 pt) 4. Activities of daily living (ADL) improvement? 0- Very satisfied (0 pt) 1- Somewhat satisfied (2.5 pt) 2- Neutral (5 pt) 3- Somewhat dissatisfied (7.5 pt) 4- Very dissatisfied (10 pt) 5. Emotional status improvement? 0- Very satisfied (0 pt) 1- Somewhat satisfied (2.5 pt) 2- Neutral (5 pt) 3- Somewhat dissatisfied (7.5 pt) 4- Very dissatisfied (10 pt) |
Signature: __________ Date: __________ | |
Name: Gender: Age: Hospital ID: Contact: | |
To accurately evaluate and effectively treat your condition, please provide truthful responses to the following questions. Mark "√" in the box that best reflects your actual situation. | |
I. Patient Demographic Data 1. Affected Side: □Left □Right 2. Branch Involvement: □V1 □V2 □V3 □V1+V2 □V2+V3 □V1+V2+V3 3. Pain Characteristics: □Electric shock-like □Tearing-like □Stabbing-like □Needle-prick-like □Burning-like 4. Attack Frequency: □< 10 times/day □10-50 times/day □≥ 50 times/day 5. Attack Duration: □< 1 min □1-10 min □≥ 10 min 6. Disease Course: □<6 months □ ≥6 months, <1 year □≥1 year, <3 years □ ≥3 years, <5 years □≥5 years, <10 years □ ≥10 years, <20 years □≥20 years 7. Remission Period: □< 1 week □ ≥1 week, <1 month □≥1 months, <6 months □ ≥6 months, <1 year □ 1-5 years □ 5-10 years □ > 10 years | 8. Current Analgesic Use (Check pain relief rate and specify medications): (No relief) 0 10% 20% 30% 40% 50% 60% 70% 80% 90% 100% (Complete relief) (1) First-line: □Carbamazepine □Oxcarbazepine (2) Second-line: □ Pregabalin □ Gabapentin □ Baclofen □ Lamotrigine (3) Others: □ Ibuprofen □ Tramadol □ Diclofenac sodium □ Paracetamol/Dihydrocodeine □ Duloxetine □ Venlafaxine □ Oxycodone □ Other (_________) 9. Prior Non-pharmacological Interventions (Check pain relief rate and specify procedure): (No relief) 0 10% 20% 30% 40% 50% 60% 70% 80% 90% 100% (Complete relief) □ Percutaneous Radiofrequency Thermocoagulation of Trigeminal Ganglion □ Meckel's Cave Balloon Compression □ Meckel's Cave Glycerol Rhizotomy □ Nerve Block Therapy □ Microvascular Decompression □ Gamma Knife Radiosurgery □ Other (__________________________) |
To ensure accurate assessment and effective treatment of your condition, please answer the following questions truthfully based on your experiences over the past week. Mark "√" next to the option that best reflects your actual situation. 0 = No pain; 1-3 = Mild pain; 4-6 = Moderate pain; 7-9 = Severe pain; 10 = Excruciating pain | |
II. Pain Assessment (Total 17 items, 170 points) (I). Pain intensity 1. How severe was your most intense facial pain? (No pain) 0 1 2 3 4 5 6 7 8 9 10 (Unbearable pain) 2. How would you rate your average facial pain recently? (No pain) 0 1 2 3 4 5 6 7 8 9 10 (Unbearable pain) (II). Accompanying symptoms 3. (Physician's examination) When comparing light touch on affected vs. unaffected facial skin, do you experience reduced sensation in the pain area? If yes, select the degree. 0 1 2 3 4 5 6 7 8 9 10 4. Is facial pain accompanied by facial/masticatory muscle spasms/twitching? 0- No (0 pt) 1- Yes (10 pt) 5. Is facial pain accompanied by conjunctival congestion and/or tearing? 0- No (0 pt) 1- Yes (10 pt) 6. Is facial pain accompanied by salivation? 0- No (0 pt) 1- Yes (10 pt) (III). Mood and Sleep 7. Do you feel fatigued or lacking energy due to facial pain recently? 0-Never (0 pt) 1-Sometimes (2.5 pt) 2-Half the time (5 pt) 3-Mostly (7.5 pt) 4-Nearly daily (10 pt) 8. Does facial pain cause difficulty concentrating (e.g., when using phones/watching TV)? 0-Never (0 pt) 1-Sometimes (2.5 pt) 2-Half the time (5 pt) 3-Mostly (7.5 pt) 4-Nearly daily (10 pt) 9. Do you feel anxious, tense, or restless due to facial pain recently? 0-Never (0 pt) 1-Sometimes (2.5 pt) 2-Half the time (5 pt) 3-Mostly (7.5 pt) 4-Nearly daily (10 pt) 10. Do you feel depressed, discouraged, or helpless due to facial pain recently? 0-Never (0 pt) 1-Sometimes (2.5 pt) 2-Half the time (5 pt) 3-Mostly (7.5 pt) 4-Nearly daily (10 pt) | 11. Does facial pain affect your sleep quality? 0-No effect (0 pt) 1-Occasional disturbance (2.5 pt) 2-< 6 hrs sleep/night (5 pt) 3-< 4 hrs sleep/night (7.5 pt) 4-< 2 hrs sleep/night (10 pt) 12. Do you wake up from sleep due to facial pain? 0-Never (0 pt) 1-Rarely (2.5 pt) 2-≥1 time/month (5 pt) 3-≥1 time/week (7.5 pt) 4-Almost nightly (10 pt) (IV). Quality of Life 13. Does voluntary facial movement (speaking, chewing, expressions) trigger your pain? 0-Never (0 pt) 1-Occasionally mild (2.5 pt) 2-Moderately in 50% cases (5 pt) 3-Severely in most cases (7.5 pt) 4-Very severe in nearly all attacks (10 pt) 14. Does light touch/stretching of facial areas (gums, lips, ala nasi, cheeks, periorbital regions) trigger pain? 0-Never (0 pt) 1-Occasionally mild (2.5 pt) 2-Moderately in 50% cases (5 pt) 3-Severely in most cases (7.5 pt) 4-Very severe in nearly all attacks (10 pt) 15. Does pain affect daily activities (washing, eating, speaking, smiling)? 0 - No impact (0 pt) 1- Minimal impact (manageable without intervention) (2.5 pt) 2- Moderate impact (disruptive but daily activities sustainable) (5 pt) 3- Severe impact (requires cessation of activities) (7.5 pt) 4- Complete disability (unable to perform any routine tasks) (10 pt) 16. Do negative emotions from pain (depression, helplessness, anxiety) affect your work/life (job, socializing, chores)? 0- No impact (0 pt) 1- Minimal impact (manageable without intervention) (2.5 pt) 2- Moderate impact (disruptive but daily activities sustainable) (5 pt) 3- Severe impact (requires cessation of activities) (7.5 pt) 4- Complete disability (unable to perform any routine tasks) (10 pt) 17. Does pain affect your social interactions with family/friends/colleagues? 0- No impairment (0 pt) 1- Minimal impact (noticeable but ignorable) (2.5 pt) 2- Moderate impact (disruptive yet sustainable with effort) (5 pt) 3- Severe impact (requires social withdrawal) (7.5 pt) 4- Complete social disability (functionally isolated) (10 pt) |
To ensure precise evaluation and effective treatment of your condition, please provide truthful and accurate responses to the following questions. Mark "✓" next to the option that best corresponds to your actual situation. | |
III. Post-treatment Evaluation (Total 5 items, 50 points) 1. Adverse drug reactions (ADRs) from first-line therapy? (Cumulative scoring) 0- No ADRs or resolved spontaneously (0 pt) 1- CNS reactions (dizziness, headache, ataxia, somnolence, fatigue, diplopia) (3.33 pt) 2- GI disturbances (nausea, vomiting) (3.33 pt) 3- Cutaneous hypersensitivity (3.33 pt) 2. Surgical complications? (Cumulative scoring) 0- No complications or transient (0 pt) 1- Hypoesthesia (2 pt) 2- Non-specific complaints (2 pt) 3- Dysesthesia (2 pt) 4- Keratitis (2 pt) 5- Anesthesia dolorosa (2 pt) 3. Impact of ADRs/complications on daily living? 0- No impact (0 pt) 1- Minimal impact (2.5 pt) 2- Mild impact (5 pt) 3- Severe impact (7.5 pt) 4- Complete disability (10 pt) 4. Does sleep disturbance occur due to treatment-related adverse effects or complications? 0-No effect (0 pt) 1-Occasional disturbance (2.5 pt) 2-< 6 hrs sleep/night (5 pt) 3-< 4 hrs sleep/night (7.5 pt) 4-< 2 hrs sleep/night (10 pt) 5. Has your emotional state been altered due to treatment-related adverse effects or complications? 0- None (0 pt) 1- Sometimes (2.5 pt) 2- Half the time (5 pt) 3- Mostly (7.5 pt) 4- Nearly daily (10 pt) | IV. Overall Satisfaction Assessment (Total 5 items, 50 points) 1. Overall treatment satisfaction? 0- Very satisfied (0 pt) 1- Somewhat satisfied (2.5 pt) 2- Neutral (5 pt) 3- Somewhat dissatisfied (7.5 pt) 4- Very dissatisfied (10 pt) 2. Pain intensity improvement? 0- Very satisfied (0 pt) 1- Somewhat satisfied (2.5 pt) 2- Neutral (5 pt) 3- Somewhat dissatisfied (7.5 pt) 4- Very dissatisfied (10 pt) 3. Sleep improvement? 0- Very satisfied (0 pt) 1- Somewhat satisfied (2.5 pt) 2- Neutral (5 pt) 3- Somewhat dissatisfied (7.5 pt) 4- Very dissatisfied (10 pt) 4. Activities of daily living (ADL) improvement? 0- Very satisfied (0 pt) 1- Somewhat satisfied (2.5 pt) 2- Neutral (5 pt) 3- Somewhat dissatisfied (7.5 pt) 4- Very dissatisfied (10 pt) 5. Emotional status improvement? 0- Very satisfied (0 pt) 1- Somewhat satisfied (2.5 pt) 2- Neutral (5 pt) 3- Somewhat dissatisfied (7.5 pt) 4- Very dissatisfied (10 pt) |
Signature: __________ Date: __________ | |
Frequency | Percentage (%) | |
|---|---|---|
Gender | ||
Male | 67 | 45.6% |
Female | 80 | 54.4% |
Age | ||
≦50 | 13 | 8.8% |
51-65 | 64 | 43.5% |
66-80 | 65 | 44.2% |
>80 | 5 | 3.4% |
Side | ||
Left | 52 | 35.4% |
Right | 95 | 64.6% |
Course | ||
<6 months | 22 | 15.0% |
≥6 months, <1 year | 15 | 10.2% |
≥1 year, <3 years | 30 | 20.4% |
≥3 years, <5 years | 27 | 18.4% |
≥5 years, <10 years | 27 | 18.4% |
≥10 years, <20 years | 21 | 14.3% |
≥20 years | 5 | 3.4% |
Branch Involvement | ||
V1 | 2 | 1.4% |
V2 | 48 | 32.7% |
V3 | 42 | 28.6% |
V1+V2 | 14 | 9.5% |
V2+V3 | 33 | 22.4% |
V1+V2+V3 | 8 | 5.4% |
Attack Frequency | ||
<10 times/day | 128 | 87.1% |
10~49 times/day | 18 | 12.2% |
≥50 times/day | 1 | 0.7% |
Attack Duration | ||
<1 minute | 99 | 67.3% |
1~10 minutes | 25 | 17.0% |
≥10 minutes | 23 | 15.6% |
Pain Characteristics | ||
Electric-shock-like | 122 | 83.0% |
Knife-stabbing-like | 35 | 23.8% |
Tearing-like | 14 | 9.5% |
Pricking-like | 57 | 38.8% |
Burning-like | 10 | 6.8% |
Associated Symptoms | ||
Hemifacial spasm/twitching | 12 | 8.2% |
Conjunctival injection/lacrimation | 20 | 13.6% |
Salivation | 21 | 14.3% |
Prior Treatments | ||
First-line medications | 116 | 78.9% |
Other medications | 16 | 10.9% |
Surgical interventions | 45 | 30.6% |
Symptom Relief after First-line Medications | ||
Major relief | 11 | 7.5% |
Moderate relief | 39 | 26.5% |
Mild relief | 66 | 44.9 |
No relief / Not used | 31 | 21.1% |
Symptom Relief after Other Medications | ||
Major relief | 1 | 0.7% |
Moderate relief | 1 | 0.7% |
Mild relief | 14 | 9.5% |
No relief / Not used | 131 | 89.1% |
Symptom Relief after Surgical Interventions | ||
Complete relief | 11 | 7.5% |
Major relief | 17 | 11.6% |
Moderate relief | 8 | 5.4% |
Mild relief | 9 | 6.1% |
No relief / Not used | 102 | 69.4% |
Treatment Modality | n | Pain-free with medication discontinued [n, (%)] | Sustained analgesia requires decreased dose [n, (%)] | Sustained analgesia maintained at current dose [n, (%)] | Sustained analgesia requires increased dose [n, (%)] |
|---|---|---|---|---|---|
Meckel's balloon compression | 44 | 43 (97.7) | 1 (2.3) | 0 | 0 |
Percutaneous trigeminal ganglion radiofrequency thermocoagulation | 95 | 80 (84.2) | 10 (10.5) | 3 (3.2) | 2 (2.1) |
Maxillary/infraorbital nerve radiofrequency thermocoagulation | 4 | 4 (100.0) | 0 | 0 | 0 |
Pharmacological treatment | 4 | 0 | 2 (50.0) | 1 (25.0) | 1 (25.0) |
Item- Number | Item Content | Critical Ratio (t) | Item-Total Correlation (r) | SD |
|---|---|---|---|---|
Q1 | How severe was your most intense facial pain? recently? | 5.219a | 0.492a | 1.520 |
Q2 | How would you rate your mildest facial pain recently? | 0.100 | 0.181a | 3.266 |
Q3 | How would you rate your average facial pain recently? | 5.424a | 0.513a | 1.585 |
Q4 | Does your pain worsen with weather/environmental changes? | 6.676a | 0.414a | 5.016 |
Q5 | Does your pain worsen with fatigue/emotional stress? | 2.802a | 0.371a | 2.945 |
Q6 | Does voluntary facial movement (speaking, chewing, expressions) trigger your pain? | 7.123a | 0.547a | 1.856 |
Q7 | Does light touch/stretching of facial areas (gums, lips, ala nasi, cheeks, periorbital regions) trigger pain? | 6.334a | 0.516a | 2.347 |
Q8 | (Physician's examination) When comparing light touch on affected vs. unaffected facial skin, do you experience reduced sensation in the pain area? If yes, select the degree | 0.583 | 0.087 | 1.408 |
Q9 | Do you feel anxious, tense, or restless due to facial pain recently? | 7.265a | 0.647a | 2.268 |
Q10 | Do you feel depressed, discouraged, or helpless due to facial pain recently? | 10.642a | 0.713a | 2.534 |
Q11 | Do you feel fatigued or lacking energy due to facial pain recently? | 10.266a | 0.729a | 2.324 |
Q12 | Does facial pain cause difficulty concentrating (e.g., when using phones/watching TV)? | 8.081a | 0.705a | 2.409 |
Q13 | Does facial pain make you feel worthless, like a failure, or that you've let down yourself/family? | 6.407a | 0.639a | 1.348 |
Q14 | Have you ever felt unable to cope, had thoughts of dying, or self-harm due to facial pain? | 4.122a | 0.497a | 1.159 |
Q15 | Does facial pain affect your sleep quality? | 9.331a | 0.695a | 2.137 |
Q16 | Do you wake up from sleep due to facial pain? | 9.287a | 0.724a | 3.184 |
Q17 | Does pain affect daily activities (washing, eating, speaking, smiling)? | 9.188a | 0.558a | 2.390 |
Q18 | Do negative emotions from pain (depression, helplessness, anxiety) affect your work/life (job, socializing, chores)? | 7.879a | 0.660a | 2.048 |
Q19 | Does pain affect your social interactions with family/friends/colleagues? | 8.886a | 0.604a | 1.764 |
Q20 | Is facial pain accompanied by facial/masticatory muscle spasms/twitching? | 2.267a | 0.203a | 1.502 |
Q21 | Is facial pain accompanied by conjunctival congestion and/or tearing? | 3.665a | 0.285a | 1.847 |
Q22 | Is facial pain accompanied by salivation? | 2.855a | 0.282a | 1.650 |
Q23 | What is your recent pain attack frequency? | 1.050 | 0.144 | 2.511 |
Q24 | What is your recent pain attack duration? | 1.359 | 0.133 | 3.413 |
Factor | Initial Eigenvalues | Extraction Sums of Squared Loadings | Rotation Sums of Squared Loadings | ||||||
|---|---|---|---|---|---|---|---|---|---|
Total | Variance (%) | Cumulative (%) | Total | Variance (%) | Cumulative (%) | Total | Variance (%) | Cumulative (%) | |
1 | 6.388 | 42.588 | 42.588 | 6.388 | 42.588 | 42.588 | 3.877 | 25.849 | 25.849 |
2 | 1.825 | 12.167 | 54.755 | 1.825 | 12.167 | 54.755 | 3.701 | 24.674 | 50.524 |
3 | 1.369 | 9.125 | 63.880 | 1.369 | 9.125 | 63.880 | 2.003 | 13.356 | 63.880 |
| [1] | (IHS) H C C O T I H S. The International Classification of Headache Disorders, 3rd edition [J]. Cephalalgia, 2018, 38(1): 1-211. |
| [2] | BENDTSEN L, ZAKRZEWSKA J M, HEINSKOU T B, et al. Advances in diagnosis, classification, pathophysiology, and management of trigeminal neuralgia [J]. Lancet Neurol, 2020, 19(9): 784-796. |
| [3] | JILEI Y, XIAOXIA W, WENLI W, et al. Recent Advances in the Diagnosis and Treatment of Trigeminal Neuralgia [J]. Chinese Journal Of Pain Medicine 2023, 29(3): 201-206. |
| [4] | ZAKRZEWSKA J M, WU J, MON-WILLIAMS M, et al. Evaluating the impact of trigeminal neuralgia [J]. Pain, 2017, 158(6): 1166-1174. |
| [5] | GROUP C M A N B F N, FUNCTIONAL NEUROSURGERY EXPERT COMMITTEE OF NEUROSURGERY BRANCH C M D A, CENTER S J T U C N D D A T. Expert consensus on the diagnosis and treatment of trigeminal neuralgia [J]. Chinese Journal Of Surgery, 2015, 53(09). |
| [6] | DASHENG W, WEI T, QIAN Z. Chinese Guideline for Neuropathic Pain Assessment and Management (2024) [J]. Chinese Journal Of Pain Medicine 2024, 30(01): 5-14. |
| [7] | LI W, QING Z, JUN C, et al. Expert Consensus on the Application of Pain Evaluation Questionnaires in China (2020) [J]. Chinese Journal Of Painology, 2020, 16(03): 177-187. |
| [8] | AO X, YAO D, WEI W, et al. A preliminary investigation into the quality of life of academic journal editors based on SF-36 and the influencing factors [J]. Chinese journal of scientific and technical periodicals, 2022, 33(04): 450-457. |
| [9] | LEVETT D Z H, GRIMMETT C. Psychological factors, prehabilitation and surgical outcomes: evidence and future directions [J]. Anaesthesia, 2019, 74 Suppl 1: 36-42. |
| [10] | ZHIXI L, QIANPING S, HONGXIA Y, et al. Reliability and validity evaluation of Pittsburgh sleep quality index in nursing population [J]. JOURNAL OF SHANTOU UNIVERSITY MEDICAL COLLEGE, 2020, 33(03): 173-176. |
| [11] | XIAOHAN J, TAO S, SHIYAO L, et al. The development and validation of Chinese scales for the efficacy evaluation of lumbar spinal stenosis [J]. Chinese Journal Of Painology, 2023, 19(03): 408-419. |
| [12] | NEURORESTORATOLOGY PROFESSIONAL COMMITTEE C M D A, PERIPHERAL NEUROSURGERY PROFESSIONAL COMMITTEE C M D A, NEURORESTORATOLOGY I A O. Expert consensus on the diagnosis and treatment of idiopathic and secondary trigeminal neuralgia (2025 edition) [J]. National Medical Journal Of China, 2025, 105(25): 2058-2071. |
| [13] | PAIN E T F F T D O C C P G F N, ELDERLY P M B O C H C A F T, ZHIXIANG C, et al. A Chinese guideline for the diagnosis and treatment of neuropathic pain (2024 edition) [J]. Chinese Journal Of Painology, 2024, 20(04). |
| [14] | YUE H, XINLI Z, JIANQIAO F, et al. Expert consensus on non-surgical diagnosis and treatment methods of traditional chinese and western medicine for primary trigeminal neuralgia [J]. JOURNAL OF PRACTICAL STOMATOLOGY, 2022, 38(02): 149-161. |
| [15] | TING T, KOUYING L, BEI D, et al. Development of a self-care scale for patients with chronic obstructive pulmonary disease and the test of its reliability and validity [J]. Chinese Journal Of Nursing, 2021, 56(02): 233-238. |
| [16] | JONCKHEERE M D, VAUGHN L M, XINYUE Z, et al. Semistructured Interviewing in Primary Care Research: a Balance of Relationship and Rigour [J]. CHINESE GENERAL PRACTICE, 2019, 22(23): 2786-2792. |
| [17] | XIAOHAN J, TAO S, SHIYAO L, et al. The development and validation of Chinese scale for the efficacy evaluation of lumbar disc herniation [J]. Chinese Journal Of Painology, 2023, 19(03): 396-407. |
| [18] | DIANSHUN H, ZHANLIN Z. The Reliability and Validity Test of the Questionnaire Based on SPSS and AMOS——A Case Study on the Relationship Among Mathematical Anxiety, Mathematical Attitude and Mathematical Self-Efficiency [J]. EDUCATIONAL MEASUREMENT AND EVALUATION, 2020, (11): 3-7, 28. |
| [19] | JINGZHENG S, XIANKUN M, ZHENQIU S. Content validity index in scale development [J]. Journal of Central South University (Medical Science) 2012, 37(02): 49-52. |
| [20] | YU Z, LI W. The progress in clinical treatment of trigeminal neuralgia [J]. Chinese Journal Of Painology, 2024, 20(03): 469-474. |
| [21] | JINGLOU Q, YAXIN Z, BO Q. The Delphi method and its application in medical education research [J]. CHINESE JOURNAL OF MEDICAL EDUCATION, 2019, 39(03): 227-230. |
| [22] | TINGTING S, ZHIYAN J, ZHEN X. Expert Consensus of TCM Clinical Diagnosis and Treatment for Pediatric Adenoid Hypertrophy with Shanghai Characteristics Based on Delphi Method [J]. Guiding Journal of Traditional Chinese Medicine and Pharmacology, 2024, 30(12): 73-77. |
| [23] | CHUANMENG Z, ZHIWEN H, CHONGHUA W, et al. Development and responsiveness of the coronary heart disease scale in the patient reported outcomes instruments system for chronic diseases [J]. Chinese Journal of Modern Nursing, 2018, 24(17). |
| [24] | ASHINA S, ROBERTSON C E, SRIKIATKHACHORN A, et al. Trigeminal neuralgia [J]. Nat Rev Dis Primers, 2024, 10(1): 39. |
APA Style
Jinfeng, Z., Yuxuan, W., Tao, S. (2025). Development and Validation of a Chinese Assessment Scale for the Primary Trigeminal Neuralgia Based on the Delphi Method. International Journal of Pain Research, 1(4), 87-106. https://doi.org/10.11648/j.ijpr.20250104.13
ACS Style
Jinfeng, Z.; Yuxuan, W.; Tao, S. Development and Validation of a Chinese Assessment Scale for the Primary Trigeminal Neuralgia Based on the Delphi Method. . 2025, 1(4), 87-106. doi: 10.11648/j.ijpr.20250104.13
AMA Style
Jinfeng Z, Yuxuan W, Tao S. Development and Validation of a Chinese Assessment Scale for the Primary Trigeminal Neuralgia Based on the Delphi Method. . 2025;1(4):87-106. doi: 10.11648/j.ijpr.20250104.13
@article{10.11648/j.ijpr.20250104.13,
  author = {Zhao Jinfeng and Wang Yuxuan and Sun Tao},
  title = {Development and Validation of a Chinese Assessment Scale for the Primary Trigeminal Neuralgia Based on the Delphi Method
},
  journal = {International Journal of Pain Research},
  volume = {1},
  number = {4},
  pages = {87-106},
  doi = {10.11648/j.ijpr.20250104.13},
  url = {https://doi.org/10.11648/j.ijpr.20250104.13},
  eprint = {https://article.sciencepublishinggroup.com/pdf/10.11648.j.ijpr.20250104.13},
  abstract = {Objective: To develop and validate an assessment scale for primary trigeminal neuralgia (PTN) that is suitable for Chinese patients’ clinical requirements and cultural background. Methods: Descriptive study. (1) Construction of pre-scales: A pool of scale entries was prepared based on the common clinical features of PTN, the consensus of domestic experts, clinical diagnosis and treatment guidelines, and the reference of the international scale production process. Based on the Delphi method, 21 experts were invited to participate in two rounds of correspondence and pre-test revisions to develop the pre-scales. (2) Formation and validation of the preliminary version of the scale: A clinical investigation was conducted on 157 patients with PTN in the Pain Department of Shandong Provincial Hospital from March 20, 2024 to January 1, 2025. The entries were screened to form a preliminary version of the scale using the critical ratio method, correlation coefficient method, and discrete trend method. The scientific validity and feasibility of the scale were then assessed through reliability and validity tests, satisfaction measurements, and reflective tests. Results: 147 patients with PTN completed the study. The positive coefficient of two rounds of expert correspondence was 100.0%, the authoritative coefficient was 0.927 and 0.957 (>0.900), the Kendall's W coefficient was 0.227 and 0.421, respectively (all P0.700), the content validity index 0.935 (>0.900) for S-CVI and 0.810-1.000 (all≥0.780) for I-CVI respectively, the Kaiser-Meyer-Olkin (KMO) value 0.858 (>0.600), and χ2=1 220.060 (P0.80). The final scale consisted of 4 parts: the first part with 6 non-quantitative entries, the second part contained 4 dimensions and 20 quantitative entries, the third part contained 5 entries related to post-treatment evaluation, the fourth part was the overall satisfaction evaluation with 5 entries, and the third and fourth parts were for post-treatment only. Conclusion: The primary trigeminal neuralgia assessment scale has good reliability, validity, and applicability.
},
 year = {2025}
}
TY  - JOUR
T1  - Development and Validation of a Chinese Assessment Scale for the Primary Trigeminal Neuralgia Based on the Delphi Method

AU  - Zhao Jinfeng
AU  - Wang Yuxuan
AU  - Sun Tao
Y1  - 2025/10/29
PY  - 2025
N1  - https://doi.org/10.11648/j.ijpr.20250104.13
DO  - 10.11648/j.ijpr.20250104.13
T2  - International Journal of Pain Research
JF  - International Journal of Pain Research
JO  - International Journal of Pain Research
SP  - 87
EP  - 106
PB  - Science Publishing Group
SN  - 3070-1562
UR  - https://doi.org/10.11648/j.ijpr.20250104.13
AB  - Objective: To develop and validate an assessment scale for primary trigeminal neuralgia (PTN) that is suitable for Chinese patients’ clinical requirements and cultural background. Methods: Descriptive study. (1) Construction of pre-scales: A pool of scale entries was prepared based on the common clinical features of PTN, the consensus of domestic experts, clinical diagnosis and treatment guidelines, and the reference of the international scale production process. Based on the Delphi method, 21 experts were invited to participate in two rounds of correspondence and pre-test revisions to develop the pre-scales. (2) Formation and validation of the preliminary version of the scale: A clinical investigation was conducted on 157 patients with PTN in the Pain Department of Shandong Provincial Hospital from March 20, 2024 to January 1, 2025. The entries were screened to form a preliminary version of the scale using the critical ratio method, correlation coefficient method, and discrete trend method. The scientific validity and feasibility of the scale were then assessed through reliability and validity tests, satisfaction measurements, and reflective tests. Results: 147 patients with PTN completed the study. The positive coefficient of two rounds of expert correspondence was 100.0%, the authoritative coefficient was 0.927 and 0.957 (>0.900), the Kendall's W coefficient was 0.227 and 0.421, respectively (all P0.700), the content validity index 0.935 (>0.900) for S-CVI and 0.810-1.000 (all≥0.780) for I-CVI respectively, the Kaiser-Meyer-Olkin (KMO) value 0.858 (>0.600), and χ2=1 220.060 (P0.80). The final scale consisted of 4 parts: the first part with 6 non-quantitative entries, the second part contained 4 dimensions and 20 quantitative entries, the third part contained 5 entries related to post-treatment evaluation, the fourth part was the overall satisfaction evaluation with 5 entries, and the third and fourth parts were for post-treatment only. Conclusion: The primary trigeminal neuralgia assessment scale has good reliability, validity, and applicability.

VL  - 1
IS  - 4
ER  -
Cheeloo College of Medicine, Shandong University, Jinan City, China; Department of Pain Management, Shandong Provincial Hospital, Jinan City, China
Cheeloo College of Medicine, Shandong University, Jinan City, China; Department of Pain Management, Shandong Provincial Hospital, Jinan City, China
Cheeloo College of Medicine, Shandong University, Jinan City, China; Department of Pain Management, Shandong Provincial Hospital, Jinan City, China

Information



 Share This Article
 Twitter
 Linked In
 Facebook

 Copy
 Download