
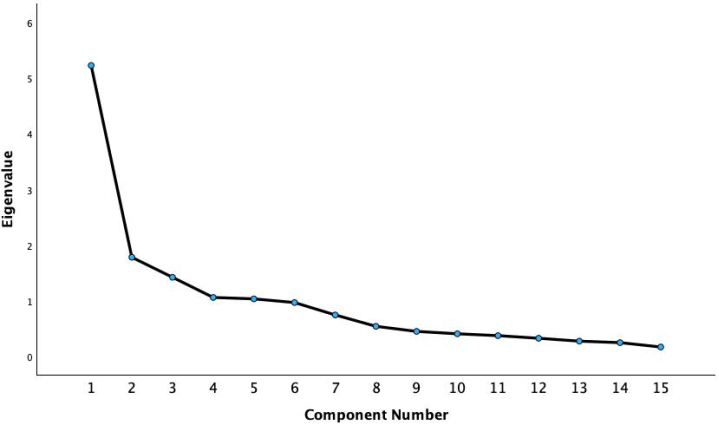
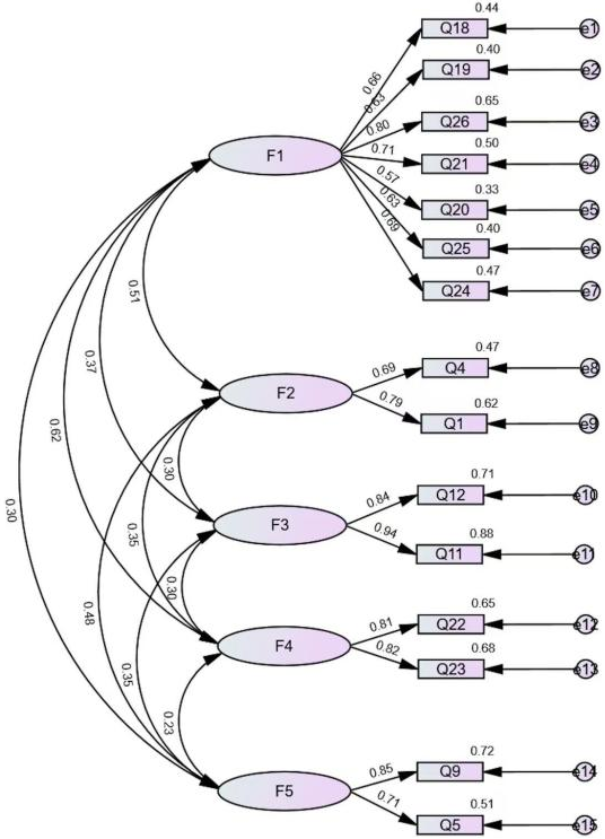
Objective: To develop and validate a Chinese assessment scale for patients with zoster-associated pain (ZAP) that is tailored to China's national conditions. Methods: A descriptive study was conducted to formulate the preliminary scale items based on the common clinical features of ZAP, incorporating consensus from domestic herpes zoster experts, clinical guidelines, and international scale development procedures. The pre-scale was refined through review by pain specialists and pre-testing. From March 20 to November 21, 2024, a clinical investigation involving 145 ZAP patients from the Pain Department of Shandong Provincial Hospital was carried out. The pre-scale questionnaire was administered and item analysis—including the critical ratio method, correlation coefficients, and discrete trend analysis—was performed to screen items and form a preliminary version. Reliability and validity were further assessed. Results: The scale demonstrated strong validity and reliability, with a standardized Cronbach’s α of 0.857 (>0.7), a KMO value of 0.781 (>0.6), and a Bartlett’s sphericity test result of χ2 = 914.521 (p < 0.001). Exploratory factor analysis extracted five common factors with a cumulative variance contribution of 70.169% (>50%) and factor loadings between 0.529 and 0.920. Confirmatory factor analysis indicated good model fit: χ2/df = 1.902, RMSEA = 0.079 (<0.08), CFI = 0.915 (>0.90), and IFI = 0.917 (>0.90). The final ZAP assessment scale comprises three sections: 15 non-quantitative items, 17 quantitative items across 5 dimensions, and 3 additional quantitative items specific to acute-phase patients. Conclusion: The developed Chinese assessment scale for ZAP exhibits good reliability, validity, and applicability, making it a suitable tool for clinical use in China.
| Published in | International Journal of Pain Research (Volume 1, Issue 4) |
| DOI | 10.11648/j.ijpr.20250104.15 |
| Page(s) | 132-149 |
| Creative Commons |
This is an Open Access article, distributed under the terms of the Creative Commons Attribution 4.0 International License (http://creativecommons.org/licenses/by/4.0/), which permits unrestricted use, distribution and reproduction in any medium or format, provided the original work is properly cited. |
| Copyright |
Copyright © The Author(s), 2025. Published by Science Publishing Group |
Pain Measurement, Questionnaires, Herpes Zoster, Zoster-associated Pain, Scale, Chinese Version, Reliability and Validity
Item number | Item content | Critical Ratio (t value) | Pearson Correlation Coefficients between the Item and Total Score | SD |
|---|---|---|---|---|
Q1 | What was the intensity of the most severe pain you experienced in the past week? | 4.434* | 0.476* | 1.241 |
Q2 | What was the intensity of the mildest pain you experienced in the past week? | 3.625* | 0.337* | 2.170 |
Q3 | How severe was your pain during the acute phase of herpes zoster? | 2.192* | 0.279* | 2.463 |
Q4 | How would you rate your pain intensity for most of the past week? | 4.201* | 0.387* | 1.772 |
Q5 | How severe are the numbness, itching, crawling sensations, or constrictive feelings associated with your pain? | 4.746* | 0.390* | 2.911 |
Q6 | Does cold weather or exposure to cold temperatures worsen your pain? | 0.788 | 0.200* | 3.911 |
Q7 | Does hot weather or exposure to heat worsen your pain? | 3.497* | 0.292* | 3.317 |
Q8 | Do changes in the weather or environment worsen your pain? | -3.592* | -0.271* | 2.785 |
Q9 | Is your pain worsened by light touch or contact (e.g., from clothing)? | 6.592* | 0.526* | 3.527 |
Q10 | Does applying pressure with your hand to the painful area relieve your pain during an episode? | 1.156* | 0.160 | 3.336 |
Q11 | Does lightly stroking the painful area with a cotton swab trigger or worsen your pain? (To be assessed by a clinician) | 7.285* | 0.574* | 3.117 |
Q12 | Does pressure applied with a finger to the painful area trigger or worsen your pain? (To be assessed by a clinician) | 6.421* | 0.523* | 3.074 |
Q13 | Is your pain persistent, either constantly or with occasional flare-ups? | 4.307* | 0.364* | 3.381 |
Q14 | Do you experience breakthrough pain? | 0.322 | 0.025 | 2.523 |
Q15 | How effective are your pain medications (e.g., ibuprofen, acetaminophen) in relieving your pain? | 0.422 | 0.076 | 2.577 |
Q16 | How effective are your neuropathic pain medications (e.g., pregabalin, duloxetine) in relieving your pain? | -0.669 | -0.078 | 2.942 |
Q17 | Have you ever undergone treatments such as nerve radiofrequency ablation or electrical nerve stimulation? If yes, how effective was the pain relief? | 0.601 | 0.096 | 3.280 |
Q18 | Over the past week, has your pain made you feel anxious, tense, irritable, or restless? | 7.982* | 0.587* | 2.978 |
Q19 | Over the past week, has your pain caused you to feel depressed, helpless, or frustrated? | 10.948* | 0.622* | 3.274 |
Q20 | Over the past week, have you felt that your pain has been getting worse? | 7.051* | 0.560* | 2.889 |
Q21 | Has your pain reduced your interest in activities you previously enjoyed? | 9.121* | 0.622* | 3.186 |
Q22 | Over the past week, has your pain disturbed your sleep? | 8.423* | 0.557* | 3.036 |
Q23 | Over the past week, have you been awakened by pain during sleep? | 10.651* | 0.610* | 3.304 |
Q24 | How much has your pain interfered with your activities of daily living (e.g., eating, bathing, housework) in the past week? | 8.513* | 0.610* | 3.118 |
Q25 | How much has your pain limited your physical mobility (e.g., standing, walking, squatting, climbing stairs) in the past week? | 7.471* | 0.538* | 3.255 |
Q26 | How much has your pain impacted your social interactions with family, friends, or colleagues in the past week? | 9.390* | 0.618* | 3.156 |
Factor | Initial Eigenvalue | Extracted Load Squared Sum | Rotated Load Squared Sum | ||||||
|---|---|---|---|---|---|---|---|---|---|
Total | Variance Contribution Rate (%) | Cumulative Variance Contribution Rate (%) | Total | Variance Percentage | Cumulative % | Total | Variance Percentage | Cumulative % | |
1 | 5.234 | 34.891 | 34.891 | 5.234 | 34.891 | 34.891 | 3.398 | 22.655 | 22.655 |
2 | 1.781 | 11.871 | 46.762 | 1.781 | 11.871 | 46.762 | 1.895 | 12.634 | 35.289 |
3 | 1.421 | 9.471 | 56.233 | 1.421 | 9.471 | 56.233 | 1.884 | 12.558 | 47.847 |
4 | 1.058 | 7.052 | 63.285 | 1.058 | 7.052 | 63.285 | 1.694 | 11.293 | 59.139 |
5 | 1.033 | 6.884 | 70.169 | 1.033 | 6.884 | 70.169 | 1.654 | 11.030 | 70.169 |
Item | Factor | ||||
|---|---|---|---|---|---|
1 | 2 | 3 | 4 | 5 | |
Q18 | 0.797 | ||||
Q19 | 0.737 | ||||
Q26 | 0.723 | ||||
Q21 | 0.666 | ||||
Q20 | 0.640 | ||||
Q25 | 0.576 | ||||
Q24 | 0.529 | ||||
Q4 | 0.799 | ||||
Q1 | 0.705 | ||||
Q12 | 0.920 | ||||
Q11 | 0.882 | ||||
Q22 | 0.852 | ||||
Q23 | 0.852 | ||||
Q9 | 0.863 | ||||
Q5 | 0.755 | ||||
Project | χ2/df | RMSEA | CFI | IFI |
|---|---|---|---|---|
Reference Standard | 1~3 | <0.08 | >0.90 | >0.90 |
Fact | 1.902 | 0.079 | 0.915 | 0.917 |
Item | Dimension | Estimate | AVE | CR |
|---|---|---|---|---|
Q18 | F1 | 0.662 | 0.456 | 0.853 |
Q19 | F1 | 0.634 | ||
Q26 | F1 | 0.803 | ||
Q21 | F1 | 0.710 | ||
Q20 | F1 | 0.572 | ||
Q25 | F1 | 0.634 | ||
Q24 | F1 | 0.687 | ||
Q4 | F2 | 0.685 | 0.544 | 0.703 |
Q1 | F2 | 0.786 | ||
Q12 | F3 | 0.841 | 0.795 | 0.886 |
Q11 | F3 | 0.940 | ||
Q22 | F4 | 0.805 | 0.664 | 0.798 |
Q23 | F4 | 0.824 | ||
Q9 | F5 | 0.847 | 0.614 | 0.760 |
Q5 | F5 | 0.715 |
Dimension | F1 | F2 | F3 | F4 | F5 |
|---|---|---|---|---|---|
F1 | 0.456 | ||||
F2 | 0.505 | 0.544 | |||
F3 | 0.369 | 0.302 | 0.795 | ||
F4 | 0.620 | 0.346 | 0.305 | 0.664 | |
F5 | 0.304 | 0.476 | 0.348 | 0.232 | 0.614 |
The Square Roots of AVE | 0.675 | 0.738 | 0.892 | 0.815 | 0.784 |
ZAP | Zoster-Associated Pain |
HZ | Herpes Zoster |
VZV | Varicella-Zoster Virus |
PHN | Postherpetic Neuralgia |
ICHD-3 | The International Classification of Headache Disorders, 3rd edition |
VAS | Visual Analogue Scale |
NRS | Numerical Rating Scale |
DN-4 | Douleur Neuropathique 4 |
LANSS | Leeds Assessment of Neuropathic Pain Symptoms and Signs Scale |
SF-MPQ | Short-Form McGill Pain Questionnaire |
SF-36 | Medical Outcomes Study 36-item short form health survey |
HADS | Hospital Anxiety and Depression Scale |
PSQI | Pittsburgh Sleep Quality Index |
NHP | Nottingham Health Profile |
QoL | Quality of Life |
SD | Standard Deviation |
CITC | Corrected Item-Total Correlation |
KMO | Kaiser-Meyer-Olkin |
RMSEA | Root Mean Square Error of Approximation |
CR | Composite Reliability |
EFA | Exploratory Factor Analysis |
CFA | Confirmatory Factor Analysis |
CFI | Comparative Fit Index |
IFI | Incremental Fit Index |
AVE | Average Variance Extracted |
NSAIDs | Nonsteroidal Anti-inflammatory Drugs |
PCA | Principal Component Analysis |
TCM | Traditional Chinese Medicine |
Name: Gender: Age: Hospital ID: Contact: | |
To accurately evaluate and effectively treat your condition, please provide truthful responses to the following questions. Mark "√" in the box that best reflects your actual situation. | |
I. Patient General Information 1. Underlying diseases: □ Diabetes □ Hypertension □ Coronary heart disease □ History of malignancy (_____________) □ History of infectious disease (e.g., hepatitis B, tuberculosis, etc.) □ Smoking/alcohol history (Smoking: _____ years, _____ cigarettes or _____ packs/day; or quit smoking, abstinence duration: _____ Alcohol: _____ years, _____ bottles of beer or _____ liang of liquor/day; or quit alcohol, abstinence duration: _____) □ Others: _____________ 2. Predisposing factors before onset: □ Fatigue, staying up late, emotional changes, high mental stress □ Cold exposure, upper respiratory tract infection □ Trauma, surgery, radiotherapy/chemotherapy, immunosuppressant use □ None of the above 3. History of herpes zoster in close relatives: □Yes □No 4. Disease duration: □ <1 month □ 1-3 months □ 3-6 months □ 6-12 months □ 1-3 years □ 3-5 years □ 5-10 years □ >10 years 5. Side of pain: □ Left □ Right 6. Involved nerve segments in the painful area: □ Trigeminal nerve □ Cervical nerve □ Thoracic nerve □ Lumbar nerve 7. Number of involved nerves: □ 1 □ 2 □ 3 □ 4 □ ≥5 8. Relationship between pain and rash onset: □ Pain before rash (prodromal pain) □ Pain concurrent with rash □ Pain after rash onset □ Pain after rash healing 9.Type of rash during the acute phase: □ No rash □ Erythema/papules only □ Clustered vesicles □ Necrosis □ Bullae/hemorrhagic/pustular blisters 10.Area of skin lesions (evaluated by palm method; patient’s palm area ≈1%): □ Mild (<3%) □ Moderate (3-5%) □ Severe (>5%) | 11. Relationship between painful area and rash area: □ Pain area smaller than rash area □ Pain area consistent with rash area □ Pain area larger than rash area 12. Time to complete rash healing: □ <1 week □ 1-2 weeks □ 2-3 weeks □ 3-4 weeks □ ≥1 month 13. Type of pain: □ Burning or stabbing □ Throbbing or distending □ Electric-shock-like or radiating □ Tearing or cutting 14. Recent use of analgesic medications: (1) Ion channel blockers: Pregabalin: _______________ Gabapentin: _______________ (2) Antiepileptics: Carbamazepine: __________Oxcarbazepine: _______________ (3) Tricyclic antidepressants: Amitriptyline: ____________Doxepin: _______________ (4) Selective norepinephrine reuptake inhibitors: Duloxetine: _____________ Venlafaxine: _______________ (5) Nonsteroidal anti-inflammatory drugs (NSAIDs): Diclofenac sodium: ____________Ibuprofen: _______________ Paracetamol/dihydrocodeine: _____Tramadol: _______________ Etoricoxib: _______________Celecoxib: _______________ (6) Opioids: Oxycodone (acetaminophen/hydrochloride): _______________ Morphine (sulfate/hydrochloride): _______________ (7) Neurotrophic agents: Mecobalamin: ________Vitamin B complex: ___________ (8) Corticosteroids: _______________ (9) Topical agents: Buprenorphine transdermal patch: _______________ Lidocaine gel patch: _______________ (10) Others: _______________ 15. Non-pharmacological treatments received: □ Shockwave therapy, electrotherapy, laser therapy, ultrasound therapy, etc. □ Traditional Chinese medicine (TCM) treatments: oral herbs/patent drugs, moxibustion, acupuncture, bloodletting cupping, acupoint embedding/injection, auricular acupuncture, etc. □ Nerve block □ Neuromodulation: radiofrequency ablation, electrical stimulation therapy, intrathecal drug delivery |
To ensure accurate assessment and effective treatment of your condition, please answer the following questions truthfully based on your experiences over the past week. Mark "√" next to the option that best reflects your actual situation. 0 = No pain; 1-3 = Mild pain; 4-6 = Moderate pain; 7-9 = Severe pain; 10 = Excruciating pain | |
1. What was the intensity of the most severe pain you experienced in the past week? (No Pain) 0 1 2 3 4 5 6 7 8 9 10 (Excruciating Pain) 2. What was the intensity of the mildest pain you experienced in the past week? (No Pain) 0 1 2 3 4 5 6 7 8 9 10 (Excruciating Pain) 3. How severe was your pain during the acute phase of herpes zoster? (No Pain) 0 1 2 3 4 5 6 7 8 9 10 (Excruciating Pain) 4. How would you rate your pain intensity for most of the past week? (No Pain) 0 1 2 3 4 5 6 7 8 9 10 (Excruciating Pain) 5. How severe are the numbness, itching, crawling sensations, or constrictive feelings associated with your pain? (No Numbness) 0 1 2 3 4 5 6 7 8 9 10 (Excruciating Numbness) 6. Does cold weather or exposure to cold temperatures worsen your pain? 0- No (0 point) 1- Lighter (2.5 points) 2- Moderate (5 points) 3- Severe (7.5 points) 4- Extremely severe (10 points) 7. Does hot weather or exposure to heat worsen your pain? 0- No (0 point) 1- Lighter (2.5 points) 2- Moderate (5 points) 3- Severe (7.5 points) 4- Extremely severe (10 points) 8. Do changes in the weather or environment worsen your pain? 0- No (0 point) 1- Lighter (2.5 points) 2- Moderate (5 points) 3- Severe (7.5 points) 4- Extremely severe (10 points) 9. Is your pain worsened by light touch or contact (e.g., from clothing)? 0- No (0 point) 1- Mild and negligible (2.5 points) 2- Moderate but tolerable (5 points) 3- Severe, requiring interruption of activity (7.5 points) 4- Extremely severe, intolerable to any contact (10 points) 10. Does applying pressure with your hand to the painful area relieve your pain during an episode? 0- No (0 point) 1- Lighter (2.5 points) 2- Moderate (5 points) 3- Severe (7.5 points) 4- Extremely severe (10 points) 11. Does lightly stroking the painful area with a cotton swab trigger or worsen your pain? (To be assessed by a clinician) 0- No (0 point) 1- Lighter (2.5 points) 2- Moderate (5 points) 3- Severe (7.5 points) 4- Extremely severe (10 points) 12. Does pressure applied with a finger to the painful area trigger or worsen your pain? (To be assessed by a clinician) 0- No (0 point) 1- Lighter (2.5 points) 2- Moderate (5 points) 3- Severe (7.5 points) 4- Extremely severe (10 points) 13. Is your pain persistent, either constantly or with occasional flare- ups? 0- No pain at all (0 point) 1- Intermittent with long pain-free intervals (2.5 points) 2- Intermittent with brief pain-free intervals (5 points) 3- Constant without episodic exacerbation (7.5 points) 4- Constant with episodic exacerbation (10 points) 14. Do you experience breakthrough pain? 0- No (0 point) 1- Occasionally, lasting up to 10 minutes per episode (2.5 points) 2- Occasionally, but lasting at least 30 minutes per episode (5 points) 3- Frequently, yet lasting up to 10 minutes per episode (7.5 points) 4- Frequently, and lasting at least 30 minutes per episode (10 points) | 15. How effective are your pain medications (e.g., ibuprofen, acetaminophen) in relieving your pain? 0- No relief / Not applicable (0 points) 1- Slight relief (2.5 points) 2- Moderate relief (5 points) 3- Substantial relief (7.5 points) 4- Complete relief (10 points) 16. How effective are your neuropathic pain medications (e.g., pregabalin, duloxetine) in relieving your pain? 0- No relief / Not applicable (0 points) 1- Slight relief (2.5 points) 2- Moderate relief (5 points) 3- Substantial relief (7.5 points) 4- Complete relief (10 points) 17. Have you ever undergone treatments such as nerve radiofrequency ablation or electrical nerve stimulation? If yes, how effective was the pain relief? 0- No relief / Not applicable (0 points) 1- Slight relief (2.5 points) 2- Moderate relief (5 points) 3- Substantial relief (7.5 points) 4- Complete relief (10 points) 18. Over the past week, has your pain made you feel anxious, tense, irritable, or restless? 0- Never (0 point) 1- Sometimes (2.5 points) 2- Halftime (5 points) 3- Usually (7.5 points) 4- Always (10 points) 19. Over the past week, has your pain caused you to feel depressed, helpless, or frustrated? 0- Never (0 point) 1- Sometimes (2.5 points) 2- Halftime (5 points) 3- Usually (7.5 points) 4- Always (10 points) 20. Over the past week, have you felt that your pain has been getting worse? 0- Never (0 point) 1- Sometimes (2.5 points) 2- Halftime (5 points) 3- Usually (7.5 points) 4- Always (10 points) 21. Has your pain reduced your interest in activities you previously enjoyed? 0- Exactly the same (0 point) 1- Slightly reduced (2.5 points) 2- Moderately reduced (5 points) 3- Minimal (7.5 points) 4- Virtually none (10 points) 22. Over the past week, has your pain disturbed your sleep? 0- Never (0 point) 1- Sometimes (2.5 points) 2- Halftime (5 points) 3- Usually (7.5 points) 4- Always (10 points) 23. Over the past week, have you been awakened by pain during sleep? 0- 0 time (0 point) 1- 1~2 times (2.5 points) 2- 3~5 times (5 points) 3- >5 times (7.5 points) 4- Unable to sleep (10 points) 24. How much has your pain interfered with your activities of daily living (e.g., eating, bathing, housework) in the past week? 0- No (0 point) 1- Has impact but is negligible (2.5 points) 2- Has noticeable impact but can persist with daily routines (5 points) 3- Has significant impact requiring interruption of activity (7.5 points) 4- Unable to perform any daily activities (10 points) 25. How much has your pain limited your physical mobility (e.g., standing, walking, squatting, climbing stairs) in the past week? 0- No (0 point) 1- Has impact but is negligible (2.5 points) 2- Has noticeable impact but can persist with the activity (5 points) 3- Has significant impact requiring interruption of activity (7.5 points) 4- Unable to perform any activity (10 points) 26. How much has your pain impacted your social interactions with family, friends, or colleagues in the past week? 0- No (0 point) 1- Has impact but is negligible (2.5 points) 2- Has noticeable impact but can be endured (5 points) 3- Has significant impact requiring interruption of activity (7.5 points) 4- Unable to engage in any social interaction (10 points) |
To ensure an accurate assessment and effective treatment of your condition, please answer the following questions objectively and accurately. Mark "√" in the box that best reflects your actual situation. | |
III. Complications (To be completed by patients in the acute phase) 1. Is there a skin infection in your painful area? 0- No (0 point) 1- Yes (10 points) 2. Are there any other acute complications in your painful area? (e.g., keratitis/conjunctivitis, hearing impairment/facial paralysis, abdominal distension/diarrhea/constipation, etc.) 0- No (0 point) 1- Yes (10 points) | 3. Is there any change in muscle strength in your painful area? 0- Complete paralysis, no detectable muscle contraction (10 points) 1- Detectable muscle contraction, but no movement generated (8 points) 2- Limb can move on the bed, but cannot overcome gravity (cannot lift off the bed) (6 points) 3- Limb can overcome gravity and lift off the bed, but cannot resist external resistance (4 points) 4- Limb can perform movements against resistance, but with reduced strength (2 points) 5- Normal muscle strength (0 points) |
Signature: __________ Date: __________ | |
Name: Gender: Age: Hospital ID: Contact: | |
To accurately evaluate and effectively treat your condition, please provide truthful responses to the following questions. Mark "√" in the box that best reflects your actual situation. | |
I. Patient General Information 1. Underlying diseases: □ Diabetes □ Hypertension □ Coronary heart disease □ History of malignancy (_____________) □ History of infectious disease (e.g., hepatitis B, tuberculosis, etc.) □ Smoking/alcohol history (Smoking: _____ years, _____ cigarettes or _____ packs/day; or quit smoking, abstinence duration: _____ Alcohol: _____ years, _____ bottles of beer or _____ liang of liquor/day; or quit alcohol, abstinence duration: _____) □ Others: _____________ 2. Predisposing factors before onset: □ Fatigue, staying up late, emotional changes, high mental stress □ Cold exposure, upper respiratory tract infection □ Trauma, surgery, radiotherapy/chemotherapy, immunosuppressant use □ None of the above 3. History of herpes zoster in close relatives: □Yes □No 4. Disease duration: □ <1 month □ 1-3 months □ 3-6 months □ 6-12 months □ 1-3 years □ 3-5 years □ 5-10 years □ >10 years 5. Side of pain: □ Left □ Right 6. Involved nerve segments in the painful area: □ Trigeminal nerve □ Cervical nerve □ Thoracic nerve □ Lumbar nerve 7. Number of involved nerves: □ 1 □ 2 □ 3 □ 4 □ ≥5 8. Relationship between pain and rash onset: □ Pain before rash (prodromal pain) □ Pain concurrent with rash □ Pain after rash onset □ Pain after rash healing 9.Type of rash during the acute phase: □ No rash □ Erythema/papules only □ Clustered vesicles □ Necrosis □ Bullae/hemorrhagic/pustular blisters 10.Area of skin lesions (evaluated by palm method; patient’s palm area ≈1%): □ Mild (<3%) □ Moderate (3-5%) □ Severe (>5%) | 11. Relationship between painful area and rash area: □ Pain area smaller than rash area □ Pain area consistent with rash area □ Pain area larger than rash area 12. Time to complete rash healing: □ <1 week □ 1-2 weeks □ 2-3 weeks □ 3-4 weeks □ ≥1 month 13. Type of pain: □ Burning or stabbing □ Throbbing or distending □ Electric-shock-like or radiating □ Tearing or cutting 14. Recent use of analgesic medications: (1) Ion channel blockers: Pregabalin: _______________ Gabapentin: _______________ (2) Antiepileptics: Carbamazepine: __________Oxcarbazepine: _______________ (3) Tricyclic antidepressants: Amitriptyline: ____________Doxepin: _______________ (4) Selective norepinephrine reuptake inhibitors: Duloxetine: _____________ Venlafaxine: _______________ (5) Nonsteroidal anti-inflammatory drugs (NSAIDs): Diclofenac sodium: ____________Ibuprofen: _______________ Paracetamol/dihydrocodeine: _____Tramadol: _______________ Etoricoxib: _______________Celecoxib: _______________ (6) Opioids: Oxycodone (acetaminophen/hydrochloride): _______________ Morphine (sulfate/hydrochloride): _______________ (7) Neurotrophic agents: Mecobalamin: ________Vitamin B complex: ___________ (8) Corticosteroids: _______________ (9) Topical agents: Buprenorphine transdermal patch: _______________ Lidocaine gel patch: _______________ (10) Others: _______________ 15. Non-pharmacological treatments received: □ Shockwave therapy, electrotherapy, laser therapy, ultrasound therapy, etc. □ Traditional Chinese medicine (TCM) treatments: oral herbs/patent drugs, moxibustion, acupuncture, bloodletting cupping, acupoint embedding/injection, auricular acupuncture, etc. □ Nerve block □ Neuromodulation: radiofrequency ablation, electrical stimulation therapy, intrathecal drug delivery |
To ensure accurate assessment and effective treatment of your condition, please answer the following questions truthfully based on your experiences over the past week. Mark "√" next to the option that best reflects your actual situation. 0 = No pain; 1-3 = Mild pain; 4-6 = Moderate pain; 7-9 = Severe pain; 10 = Excruciating pain | |
II. Pain Assessment i. Pain Intensity (2 questions, 20 points) 1. How would you rate your pain intensity for most of the past week? (No Pain) 0 1 2 3 4 5 6 7 8 9 10 (Excruciating Pain) 2. What was the intensity of the most severe pain you experienced in the past week? (No Pain) 0 1 2 3 4 5 6 7 8 9 10 (Excruciating Pain) ii. Pain Characteristics (4 questions, 40 points) 3. Is your pain worsened by light touch or contact (e.g., from clothing)? 0- No (0 point) 1- Mild and negligible (2.5 points) 2- Moderate but tolerable (5 points) 3- Severe, requiring interruption of activity (7.5 points) 4- Extremely severe, intolerable to any contact (10 points) 4. How severe are the numbness, itching, crawling sensations, or constrictive feelings associated with your pain? (No Numbness) 0 1 2 3 4 5 6 7 8 9 10 (Excruciating Numbness) 5. Is your pain persistent, either constantly or with occasional flare- ups? 0- No pain at all (0 point) 1- Intermittent with long pain-free intervals (2.5 points) 2- Intermittent with brief pain-free intervals (5 points) 3- Constant without episodic exacerbation (7.5 points) 4- Constant with episodic exacerbation (10 points) 6. Do you experience breakthrough pain? 0- No (0 point) 1- Occasionally, lasting up to 10 minutes per episode (2.5 points) 2- Occasionally, but lasting at least 30 minutes per episode (5 points) 3- Frequently, yet lasting up to 10 minutes per episode (7.5 points) 4- Frequently, and lasting at least 30 minutes per episode (10 points) iii. Clinical Signs (2 questions, 20 points) 7. Does pressure applied with a finger to the painful area trigger or worsen your pain? (To be assessed by a clinician) 0- No (0 point) 1- Lighter (2.5 points) 2- Moderate (5 points) 3- Severe (7.5 points) 4- Extremely severe (10 points) 8. Does lightly stroking the painful area with a cotton swab trigger or worsen your pain? (To be assessed by a clinician) 0- No (0 point) 1- Lighter (2.5 points) 2- Moderate (5 points) 3- Severe (7.5 points) 4- Extremely severe (10 points) iv. Sleep Quality (2 questions, 20 points) 9. Over the past week, has your pain disturbed your sleep? 0- Never (0 point) 1- Sometimes (2.5 points) 2- Halftime (5 points) 3- Usually (7.5 points) 4- Always (10 points) | 10. Over the past week, have you been awakened by pain during sleep? 0- 0 time (0 point) 1- 1~2 times (2.5 points) 2- 3~5 times (5 points) 3- >5 times (7.5 points) 4- Unable to sleep (10 points) v. Emotional State and Daily Life (7 questions, 70 points) 11. Over the past week, has your pain made you feel anxious, tense, irritable, or restless? 0- Never (0 point) 1- Sometimes (2.5 points) 2- Halftime (5 points) 3- Usually (7.5 points) 4- Always (10 points) 12. Over the past week, has your pain caused you to feel depressed, helpless, or frustrated? 0- Never (0 point) 1- Sometimes (2.5 points) 2- Halftime (5 points) 3- Usually (7.5 points) 4- Always (10 points) 13. How much has your pain impacted your social interactions with family, friends, or colleagues in the past week? 0- No (0 point) 1- Has impact but is negligible (2.5 points) 2- Has noticeable impact but can be endured (5 points) 3- Has significant impact requiring interruption of activity (7.5 points) 4- Unable to engage in any social interaction (10 points) 14. Has your pain reduced your interest in activities you previously enjoyed? 0- Exactly the same (0 point) 1- Slightly reduced (2.5 points) 2- Moderately reduced (5 points) 3- Minimal (7.5 points) 4- Virtually none (10 points) 15. Over the past week, have you felt that your pain has been getting worse? 0- Never (0 point) 1- Sometimes (2.5 points) 2- Halftime (5 points) 3- Usually (7.5 points) 4- Always (10 points) 16. How much has your pain limited your physical mobility (e.g., standing, walking, squatting, climbing stairs) in the past week? 0- No (0 point) 1- Has impact but is negligible (2.5 points) 2- Has noticeable impact but can persist with the activity (5 points) 3- Has significant impact requiring interruption of activity (7.5 points) 4- Unable to perform any activity (10 points) 17. How much has your pain interfered with your activities of daily living (e.g., eating, bathing, housework) in the past week? 0- No (0 point) 1- Has impact but is negligible (2.5 points) 2- Has noticeable impact but can persist with daily routines (5 points) 3- Has significant impact requiring interruption of activity (7.5 points) 4- Unable to perform any daily activities (10 points) |
To ensure an accurate assessment and effective treatment of your condition, please answer the following questions objectively and accurately. Mark "√" in the box that best reflects your actual situation. | |
III. Complications (To be completed by patients in the acute phase) 1. Is there a skin infection in your painful area? 0- No (0 point) 1- Yes (10 points) 2. Are there any other acute complications in your painful area? (e.g., keratitis/conjunctivitis, hearing impairment/facial paralysis, abdominal distension/diarrhea/constipation, etc.) 0- No (0 point) 1- Yes (10 points) | 3. Is there any change in muscle strength in your painful area? 0- Complete paralysis, no detectable muscle contraction (10 points) 1- Detectable muscle contraction, but no movement generated (8 points) 2- Limb can move on the bed, but cannot overcome gravity (cannot lift off the bed) (6 points) 3- Limb can overcome gravity and lift off the bed, but cannot resist external resistance (4 points) 4- Limb can perform movements against resistance, but with reduced strength (2 points) 5- Normal muscle strength (0 points) |
Signature: __________ Date: __________ | |
| [1] | Johnson R W, Alvarez-Pasquin M-J, Bijl M, et al. Herpes zoster epidemiology, management, and disease and economic burden in Europe: a multidisciplinary perspective [J]. Ther Adv Vaccines, 2015, 3(4): 109-120. |
| [2] | Expert Group on Ability Improvement Project for Chronic Dermatological Diseases, Chinese Medical Association Publishing House; Pain Physician Branch of Chinese Medical Doctor Association; Dermatology Committee, National Telemedicine and Connected Health Center. Expert consensus on the whole-process management of herpes zoster-associated pain [J]. Chin J Dermatol, 2021, 54(10): 841-846. |
| [3] | Hélène, Bricout, Margaret, et al. Herpes zoster-associated mortality in Europe: a systematic review [J]. BMC Public Health, 2015. |
| [4] | Warner B E, Goins W F, Kramer P R, et al. A Guide to Preclinical Models of Zoster-Associated Pain and Postherpetic Neuralgia [J]. Curr Top Microbiol Immunol, 2021, 438: 189-221. |
| [5] | The expert group responsible for compiling the consensus on the diagnosis and treatment of post-herpetic neuralgia. Chinese Expert Consensus on the Diagnosis and Treatment of Postherpetic Neuralgia [J]. Chinese Journal of Pain Medicine, 2016, 22(03): 161-167. |
| [6] | Wan Li, Zhao Qing, Chen Jun, et al. Expert consensus on the application of pain evaluation questionnaires in China (2020) [J]. Chin J Painol, 2020, 16(03): 177-187. |
| [7] | Guo Zheng, Wang Guonian. Pain Medicine [M]. Beijing: People's Medical Publishing House (PMPH): 2016. |
| [8] | Zhang Yang, Jin Yi. Clinical Progress of Early Intervention in Preventing Postherpetic Neuralgia [J]. Chinese Journal of Pain Medicine, 2023, 29(05): 376-380. |
| [9] | Levett D Z H, Grimmett C. Psychological factors, prehabilitation and surgical outcomes: evidence and future directions [J]. Anaesthesia, 2019, 74 Suppl 1: 36-42. |
| [10] | Liu Zhixi, Shi Qianping, Yang Hongxia, et al. Reliability and validity evaluation of Pittsburgh sleep quality index in nursingpopulation [J]. Journal of Shantou University Medical College, 2020, 33(03): 173-176. |
| [11] | Consensus Workgroup on Herpes Zoster, China Dermatologist Association; National Clinical Research Center for Skin and Immune Diseases. Chinese consensus on the diagnosis and management of herpes zoster (2022) [J]. Chin J Dermatol, 2022, 55(12): 1033-1040. |
| [12] | Jonckheere M D, Vaughn L M. Semistructured Interviewing in Primary Care Research:a Balance of Relationship and Rigour [J]. Fam Med Community Health, 2019, 7(2): e000057. |
| [13] | Jiang Xiaohan, Sun Tao, Li Shiyao, et al. The development and validation of Chinese scale for the efficacy evaluation of lumbar disc herniation [J]. Chin J Painol, 2023, 19(3): 396-407. |
| [14] | Jiang Xiaohan, Sun Tao, Li Shiyao, et al. The development and validation of Chinese scales for the efficacy evaluation of lumbar spinal stenosis [J]. Chin J Painol, 2023, 19(3): 408-419. |
| [15] | Jiang Zongbin, Zhao Peng, Lyu Jing, et al. The design and practice of Chinese scale for the diagnosis and assessment of neuropathic pain [J]. Chin J Painol, 2022, 18(04): 466-475. |
| [16] | Ahmed I, Ishtiaq S. Reliability and Validity: Importance in medical research [J]. J Pak Med Assoc, 2021, 71(10): 2401-2406. |
| [17] | Jiang Xiaohua, Shen Zhuozhi, Zhang Nannan, et al. Analysis of the reliability and validity of the questionnaire [J]. Modern Preventive Medicine, 2010, 3(3): 429-431. |
| [18] | Hu Dianshun, Zhu Zhanlin. Reliability and Validity Testing of Questionnaires Based on SPSS and AMOS: A Case Study of the Relationship between Math Anxiety, Math Attitude and Math Efficacy [J]. Educational Measurement and Evaluation, 2020, (11): 3-7+28. |
| [19] | Li Can, Xin Ling. Research on the Evaluation Methods of the Reliability and Validity of Questionnaires [J]. Chinese Journal of Health Statistics, 2008, (05): 541-544. |
| [20] | Zhang Wenfang, Hao Yanhua, Tian Tian. The reliability and validity of the Chinese version of Thirst Distress Scale with Heart Failure [J]. Chin J Nurs, 2019, 54(06): 957-960. |
| [21] | Oster G, Harding G, Dukes E, et al. Pain, medication use, and health-related quality of life in older persons with postherpetic neuralgia: results from a population-based survey [J]. J Pain, 2005, 6(6): 356-363. |
| [22] | Deng Huijie, Liu Fangxun. Epidemiological Characteristics of Herpes Zosterand Research Progress of Vaccine ImmunizationProgram in China [J]. China Continuing Medical Education, 2021, 13(19): 135-138. |
| [23] | Werner R, Nikkels A, Marinović B, et al. European consensus‐based (S2k) Guideline on the Management of Herpes Zoster-guided by the European Dermatology Forum (EDF) in cooperation with the European Academy of Dermatology and Venereology (EADV), Part 1: Diagnosis [J]. J Eur Acad Dermatol Venereol, 2017, 31(1): 9-19. |
| [24] | Yin D, Van Oorschot D, Jiang N, et al. A systematic literature review to assess the burden of herpes zoster disease in China [J]. Expert Rev Anti Infect Ther, 2021, 19(2): 165-179. |
| [25] | Yang Y, Chen T, Lin H, et al. Incidence and economic burden of herpes zoster and its complications in immunocompromised adults: a retrospective cohort study in an eastern county, China [J]. J Infect, 2022, 85(5): e155-e157. |
| [26] | Suo L, Lu L, Li J, et al. A case control study on family history as a risk factor for herpes zoster and associated outcomes, Beijing, China [J]. BMC Infect Dis, 2017, 17(1): 334. |
| [27] | Harpaz R, Dahl R M. Administrative data to explore the role of family history as a risk factor for herpes zoster: Mayo Clin Proc [C]. Elsevier. |
| [28] | Tseng HungFu T H, Chi M, Hung P, et al. Family history of zoster and risk of developing herpes zoster [J]. Int J Infect Dis, 2018, 66: 99-106. |
| [29] | Expert Group for the Development of Chinese Neuropathic Pain Diagnosis and Treatment Guidelines, Society of Painology of Chinese Aging Well Association. A Chinese guideline for the diagnosis and treatment of neuropathic pain (2024 edition) [J]. Chin J Painol, 2024, 4(20): e484-e508. |
| [30] | Wang L, Lan X, Lan Z, et al. The relationship between pain duration characteristics and pain intensity in herpes zoster-related pain: a single-center retrospective study [J]. Front Med (Lausanne), 2024, (11): 1466214. |
| [31] | Marahatta S, Jha SK, Ghimire A. Predictors of Postherpetic Neuralgia: A Prospective Study From Eastern Nepal [J]. J Cosmet Dermatol, 2025, 24(4): e70136. |
| [32] | Davies AN, Dickman A, Reid C, et al. The management of cancer-re lated breakthrough pain: recommendations of a task group of the science committee of the association for palliative medicine of great Britain and Ireland [J]. Eur J Pain, 2009, 13(4): 331-338. |
| [33] | Cleeland CS, Ryan KM. Pain assessment: global use of the Brief Pain Inventory [J]. Ann Acad Med Singap, 1994, 23(2): 129-38. |
| [34] | Freynhagen R, Baron R, Gockel U, et al. painDETECT: a new screening questionnaire to identify neuropathic components in patients with back pain [J]. Curr Med Res Opin, 2006, 22(10): 1911-20. |
APA Style
Yuxuan, W., Jinfeng, Z., Tao, S. (2025). Development and Validation of Chinese Assessment Scale for Zoster-Associated Pain. International Journal of Pain Research, 1(4), 132-149. https://doi.org/10.11648/j.ijpr.20250104.15
ACS Style
Yuxuan, W.; Jinfeng, Z.; Tao, S. Development and Validation of Chinese Assessment Scale for Zoster-Associated Pain. . 2025, 1(4), 132-149. doi: 10.11648/j.ijpr.20250104.15
AMA Style
Yuxuan W, Jinfeng Z, Tao S. Development and Validation of Chinese Assessment Scale for Zoster-Associated Pain. . 2025;1(4):132-149. doi: 10.11648/j.ijpr.20250104.15
@article{10.11648/j.ijpr.20250104.15,
  author = {Wang Yuxuan and Zhao Jinfeng and Sun Tao},
  title = {Development and Validation of Chinese Assessment Scale for Zoster-Associated Pain
},
  journal = {International Journal of Pain Research},
  volume = {1},
  number = {4},
  pages = {132-149},
  doi = {10.11648/j.ijpr.20250104.15},
  url = {https://doi.org/10.11648/j.ijpr.20250104.15},
  eprint = {https://article.sciencepublishinggroup.com/pdf/10.11648.j.ijpr.20250104.15},
  abstract = {Objective: To develop and validate a Chinese assessment scale for patients with zoster-associated pain (ZAP) that is tailored to China's national conditions. Methods: A descriptive study was conducted to formulate the preliminary scale items based on the common clinical features of ZAP, incorporating consensus from domestic herpes zoster experts, clinical guidelines, and international scale development procedures. The pre-scale was refined through review by pain specialists and pre-testing. From March 20 to November 21, 2024, a clinical investigation involving 145 ZAP patients from the Pain Department of Shandong Provincial Hospital was carried out. The pre-scale questionnaire was administered and item analysis—including the critical ratio method, correlation coefficients, and discrete trend analysis—was performed to screen items and form a preliminary version. Reliability and validity were further assessed. Results: The scale demonstrated strong validity and reliability, with a standardized Cronbach’s α of 0.857 (>0.7), a KMO value of 0.781 (>0.6), and a Bartlett’s sphericity test result of χ2 = 914.521 (p 50%) and factor loadings between 0.529 and 0.920. Confirmatory factor analysis indicated good model fit: χ2/df = 1.902, RMSEA = 0.079 (0.90), and IFI = 0.917 (>0.90). The final ZAP assessment scale comprises three sections: 15 non-quantitative items, 17 quantitative items across 5 dimensions, and 3 additional quantitative items specific to acute-phase patients. Conclusion: The developed Chinese assessment scale for ZAP exhibits good reliability, validity, and applicability, making it a suitable tool for clinical use in China.
},
 year = {2025}
}
TY  - JOUR
T1  - Development and Validation of Chinese Assessment Scale for Zoster-Associated Pain

AU  - Wang Yuxuan
AU  - Zhao Jinfeng
AU  - Sun Tao
Y1  - 2025/10/29
PY  - 2025
N1  - https://doi.org/10.11648/j.ijpr.20250104.15
DO  - 10.11648/j.ijpr.20250104.15
T2  - International Journal of Pain Research
JF  - International Journal of Pain Research
JO  - International Journal of Pain Research
SP  - 132
EP  - 149
PB  - Science Publishing Group
SN  - 3070-1562
UR  - https://doi.org/10.11648/j.ijpr.20250104.15
AB  - Objective: To develop and validate a Chinese assessment scale for patients with zoster-associated pain (ZAP) that is tailored to China's national conditions. Methods: A descriptive study was conducted to formulate the preliminary scale items based on the common clinical features of ZAP, incorporating consensus from domestic herpes zoster experts, clinical guidelines, and international scale development procedures. The pre-scale was refined through review by pain specialists and pre-testing. From March 20 to November 21, 2024, a clinical investigation involving 145 ZAP patients from the Pain Department of Shandong Provincial Hospital was carried out. The pre-scale questionnaire was administered and item analysis—including the critical ratio method, correlation coefficients, and discrete trend analysis—was performed to screen items and form a preliminary version. Reliability and validity were further assessed. Results: The scale demonstrated strong validity and reliability, with a standardized Cronbach’s α of 0.857 (>0.7), a KMO value of 0.781 (>0.6), and a Bartlett’s sphericity test result of χ2 = 914.521 (p 50%) and factor loadings between 0.529 and 0.920. Confirmatory factor analysis indicated good model fit: χ2/df = 1.902, RMSEA = 0.079 (0.90), and IFI = 0.917 (>0.90). The final ZAP assessment scale comprises three sections: 15 non-quantitative items, 17 quantitative items across 5 dimensions, and 3 additional quantitative items specific to acute-phase patients. Conclusion: The developed Chinese assessment scale for ZAP exhibits good reliability, validity, and applicability, making it a suitable tool for clinical use in China.

VL  - 1
IS  - 4
ER  -
Cheeloo College of Medicine, Shandong University, Jinan City, China; Department of Pain Management, Shandong Provincial Hospital, Jinan City, China
Cheeloo College of Medicine, Shandong University, Jinan City, China; Department of Pain Management, Shandong Provincial Hospital, Jinan City, China
Cheeloo College of Medicine, Shandong University, Jinan City, China; Department of Pain Management, Shandong Provincial Hospital, Jinan City, China

Information



 Share This Article
 Twitter
 Linked In
 Facebook

 Copy
 Download